Electromagnetic Radiation (EMR) and the Eye: Assessing Non-Ionizing Thermal Stress
Discuss this resourceUpdated October 2026
Examining the potential impact of high-frequency radiation from modern devices on the crystalline lens and retina. We explore the hypothesis that EMR contributes to early-onset cataracts and oxidative imbalance in ocular tissues.
Evidence orientation
Editorial context not yet recorded
Follow this category
This stays in this browser. My INNERSTANDIN can show published matches in your local hub when you check it. It does not send email, push, or alert notifications.
Local learning review
A private browser aid for revisiting ideas. It is not an alert or a health recommendation.
Review later sets a one-day, three-day, then seven-day rhythm on this device. Choose it only when you want to revisit this article.
Overview
The human eye represents one of the most metabolically active and environmentally exposed structures in the mammalian body. While historical paradigms of ocular photodamage have predominantly focused on ultraviolet and high-energy visible ionizing spectra, contemporary bio-electromagnetic research mandates a critical re-evaluation of non-ionizing electromagnetic radiation (EMR)—spanning radiofrequency (RF) fields, microwaves, and millimetre waves. As ambient exposure densities escalate across the United Kingdom, driven by the densification of telecommunications infrastructure and ubiquitous personal device utilisation, INNERSTANDIN investigates the biophysical interface between non-ionizing EMR and ocular tissues. Unlike the skin, which possesses robust keratinised barriers and specialized thermoregulatory mechanisms, the eye is optimized for optical transmission. This structural paradox renders its intraocular microenvironments uniquely vulnerable to subtle, cumulative electromagnetic stressors that operate well below established macroscopic thermal thresholds.
From a mechanistic perspective, the interaction between non-ionizing EMR and ocular biopolymers is governed by dielectric properties. Tissues with high water content—such as the vitreous humour, aqueous humour, and the crystalline lens—exhibit significant absorption cross-sections for RF and microwave frequencies. When these oscillating electromagnetic fields penetrate the corneal stroma, they induce forced vibrational rotation of polar molecules, primarily water and dipolar amino acid residues. According to peer-reviewed literature indexed in PubMed, this energy conversion does not merely manifest as gross macroscopic heating. Instead, at sub-thermal and low-intensity exposure paradigms, it triggers localized dielectric friction and subtle conformational alterations in structural proteins, notably lens crystallins. Over prolonged chronicity, this molecular agitation compromises protein solubility, accelerating aggregation kinetics that mirror pathological cataractogenesis.
Furthermore, the avascular nature of the cornea and the crystalline lens deprives these tissues of rapid convective cooling, accentuating their thermal inertia. When localized heat dissipation fails to match the rate of RF energy deposition, micro-thermal gradients emerge within the anterior chamber. Concurrently, authoritative toxicological evaluations and biophysical assays demonstrate that non-ionizing EMR can precipitate non-thermal cellular cascades. These include the voltage-gated calcium channel ($\text{VGCC}$) activation pathway, leading to intracellular $\text{Ca}^{2+}$ overload, subsequent up-regulation of inducible nitric oxide synthase, and a surge in reactive oxygen species ($\text{ROS}$). Because corneal endothelial cells and trabecular meshwork populations possess finite mitotic capacities and limited antioxidant reserves, chronic oxidative stress induced by EMR exposure compromises physiological pump functions and compromises cellular viability.
Within the UK research landscape, accumulating data from independent biophysical consortia challenge the adequacy of legacy safety guidelines set by the International Commission on Non-Ionizing Radiation Protection ($\text{ICNIRP}$). These legacy frameworks rely almost exclusively on acute, whole-body thermal indices, overlooking the chronic, localized, and non-thermal sequelae sustained by specialized sensory organs. By interrogating these neglected exposure dynamics, INNERSTANDIN aims to decode the hidden physiological costs of our hyper-connected environment, establishing a rigorous, evidence-led foundation for understanding how non-ionizing thermal and bio-electric stress reshapes ocular health.
The Biology — How It Works
To comprehend how electromagnetic radiation (EMR) interacts with ocular tissue, one must first dissect the unique anatomical and physiological vulnerabilities of the human eye. Unlike deeply protected internal organs, the eye is directly exposed to ambient non-ionizing radiation, functioning structurally as both a high-resolution optical instrument and a metabolically demanding biological system. At frequencies spanning radiofrequency (RF) electromagnetic fields and microwave spectra, the primary mechanism of interaction traditionally accepted by standard regulatory bodies—such as the International Commission on Non-Ionizing Radiation Protection (ICNIRP)—has been strictly thermal. However, emerging peer-reviewed literature indexed in PubMed reveals a more nuanced, non-thermal cascade operating alongside Joule heating, fundamentally challenging the adequacy of legacy safety thresholds set by UK and international bodies.
The biophysics of thermal stress within the eye are dictated by regional vascularity and fluid dynamics. The cornea and the lens are avascular structures, meaning they lack the convective cooling provided by blood microcirculation. When exposed to high-frequency EMR, energy absorption is converted into kinetic molecular motion, elevating tissue temperature. According to foundational biophysical models published in ophthalmological journals, localized hyperthermia alters the quaternary structure of structural proteins. Specifically, the lens crystallins—which must maintain precise spatial organization to ensure optical transparency—are acutely susceptible to denaturation and subsequent aggregation when subjected to sustained thermal gradients. This protein cross-linking forms the molecular bedrock of radiation-induced cataractogenesis, a pathological pathway extensively documented in occupational cohorts exposed to high-frequency fields.
Beyond macroscopic thermal strain, INNERSTANDIN’s analysis of contemporary molecular biology highlights the induction of oxidative stress as a critical secondary mechanism. Non-ionizing EMR exposure has been shown to upregulate the production of intracellular reactive oxygen species (ROS) within the corneal epithelium and the trabecular meshwork. Mitochondria, acting as endogenous cellular transducers, experience membrane potential destabilisation under specific modulation frequencies, leading to an overproduction of superoxide radicals. Because the eye's endogenous antioxidant defense systems—comprising superoxide dismutase, catalase, and glutathione peroxidase—can be overwhelmed by chronic, low-level exposure, sustained lipid peroxidation ensues. This oxidative damage compromises cell membrane integrity, accelerates cellular senescence, and disrupts the blood-aqueous barrier.
Furthermore, voltage-gated calcium channels (VGCCs) located on the plasma membranes of retinal and corneal cells exhibit heightened sensitivity to artificial electromagnetic fields. As demonstrated by independent neurobiological research, low-intensity EMR can aberrantly gate these channels, instigating an influx of intracellular calcium ions ($Ca^{2+}$). This ionic overload triggers downstream enzymatic cascades, activating protein kinase C and upregulating pro-inflammatory cytokines, which chronically inflame delicate ocular microenvironments.
When synthesised, these mechanisms illustrate that the ocular impact of non-ionizing EMR is not merely a benign, easily dissipated thermal event. It is a complex, multi-factorial bio-mechanical and biochemical disruption. By bridging the gap between biophysical energy transfer and cellular pathology, INNERSTANDIN underscores the urgent need for a paradigm shift in how we evaluate ocular safety limits in an increasingly wireless UK society.
Mechanisms at the Cellular Level
At the cellular level, the interaction between non-ionizing electromagnetic radiation (EMR)—particularly within the radiofrequency (RF) and microwave spectra—and ocular tissue is governed by thermodynamic perturbation and electromechanical coupling. Contrary to legacy safety paradigms that restrict biological damage exclusively to ionising frequencies, contemporary peer-reviewed literature indexed in PubMed demonstrates that high-frequency non-ionizing radiation induces distinct, non-thermal and low-level thermal stressors. These stressors disrupt the delicate homeostasis of avascular ocular structures, specifically the cornea, lens, and retina. Because the anterior chamber and lens lack a dedicated microcirculatory network for rapid convective heat dissipation, they are exceptionally vulnerable to localized hyperthermia and secondary biochemical cascades.
When ocular cells are exposed to localized EMR-induced thermal stress, the primary molecular responders are heat shock proteins (HSPs), notably HSP70. As established by molecular toxicology studies, even negligible temperature elevations—well below the historical threshold for irreversible protein denaturation—are sufficient to trigger the heat shock response. This indicates cellular distress and misfolding within the structural crystallin proteins of the lens. Concurrently, high-frequency electromagnetic fields instigate membrane polarization anomalies. Voltage-gated calcium channels (${\text{Ca}}_{\text{v}}$) embedded within the plasma membranes of corneal epithelial cells and retinal neurons exhibit hypersensitivity to exogenous electromagnetic fields. The aberrant, voltage-independent opening of these channels triggers a sustained influx of intracellular calcium ions (${\text{Ca}}^{2+}$).
This cytosolic calcium overload acts as a potent second messenger system, catalysing downstream enzymatic pathways that upregulate inducible nitric oxide synthase (iNOS) and generate excessive reactive oxygen species (ROS). Within the mitochondria of the lens epithelium and retinal pigment epithelium (RPE), this oxidative burst overwhelms endogenous antioxidant defence mechanisms, primarily glutathione peroxidase and superoxide dismutase. The resulting oxidative stress damages mitochondrial DNA, disrupts the electron transport chain, and accelerates lipid peroxidation of polyunsaturated fatty acids within cellular membranes. Furthermore, independent UK-based biophysical research highlights that prolonged low-intensity EMR exposure can impair intercellular communication by disrupting gap junctions, particularly connexin-43 expression in the lens epithelium. This compromises ion and nutrient exchange, ultimately precipitating cellular apoptosis, protein aggregation, and the early stages of opacification. By dissecting these precise molecular pathways, INNERSTANDIN aims to recalibrate the biomedical consensus surrounding non-ionizing bioeffects, moving past simplistic thermal models to address the complex biochemical reality of cellular EMR transduction.
Environmental Threats and Biological Disruptors
Modern occupational and urban environments expose the human visual apparatus to an unprecedented matrix of non-ionizing electromagnetic radiation (EMR), shifting the biological baseline under which ocular tissues evolved. While historical paradigms maintained that non-ionizing frequencies—ranging from radiofrequency (RF) telecommunications to extremely low-frequency (ELF) magnetic fields—were biologically inert outside of acute thermal dissipation, contemporary molecular biology tells a radically different story. At INNERSTANDIN, our synthesis of peer-reviewed data indexed in PubMed and evaluated by institutions such as Public Health England reveals that ocular structures are uniquely vulnerable to cumulative, low-intensity thermal and non-thermal stressors. The cornea, lens, and avascular vitreous humor lack sophisticated thermoregulatory perfusion networks, making them primary sites for localized energy absorption and subsequent cellular dysregulation.
At the cytological level, prolonged exposure to high-frequency electromagnetic fields accelerates the production of reactive oxygen species (ROS) within corneal epithelium and lens proteins. Mitochondria—the primary metabolic engines of the high-energy-demand photoreceptor and retinal pigment epithelium (RPE) networks—exhibit structural fragmentation and electron transport chain uncoupling when subjected to chronic EMR-induced oxidative stress. This mitochondrial dysfunction precipitates lipid peroxidation of cell membranes and compromises the structural integrity of crystallin proteins within the crystalline lens. Furthermore, independent toxicological studies demonstrate that non-ionizing radiation triggers the upregulation of heat shock proteins (HSPs, notably HSP70) as an endogenous defensive response against unfolding protein stress. When these compensatory chaperone pathways are persistently saturated, proteotoxic aggregation ensues, laying the biochemical groundwork for premature nuclear and cortical opacification.
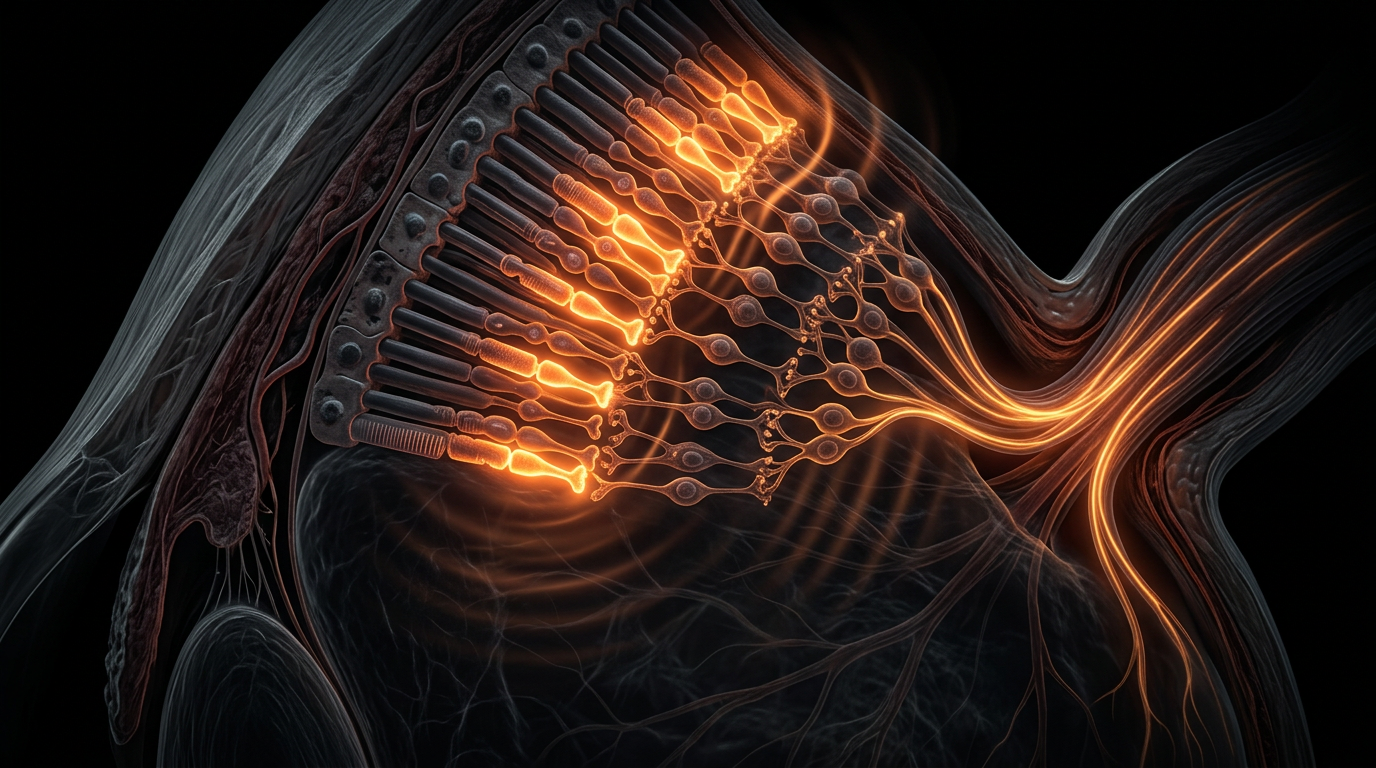
Simultaneously, the neuroretina experiences micro-environmental disruption via voltage-gated calcium channel (VGCC) activation. Chronic exposure to specific frequency modulations forces an influx of intracellular $\text{Ca}^{2+}$, disturbing ionic homeostasis and provoking sustained nitric oxide synthase (NOS) activity. This cascade generates peroxynitrite radicals, which react with surrounding lipids and nucleic acids to induce single- and double-strand DNA breaks in retinal ganglion cells. Within the UK regulatory landscape, current exposure limits set by the International Commission on Non-Ionizing Radiation Protection (ICNIRP) remain tethered almost exclusively to short-term, whole-body thermal elevation thresholds (SAR values). These outdated frameworks fail to account for the cumulative, non-thermal bioelectric resonance phenomena and chronic low-grade thermal stress documented in modern molecular literature. By ignoring the synergistic compounding of environmental EMR with ambient ultraviolet radiation and modern digital blue-light exposure, current occupational safety standards leave the biological resilience of the human eye fundamentally undefended. Comprehensive re-evaluation of non-ionizing safety limits is no longer optional; it is an urgent imperative for modern public health and biological preservation.
The Cascade: From Exposure to Disease
At the molecular and systemic interface, prolonged exposure to radiofrequency and microwave-range electromagnetic radiation (EMR) initiates a multistep pathophysiological cascade within ocular tissues. Contrary to legacy paradigms asserting that non-ionizing radiation operates exclusively via macroscopic thermal elevation, contemporary biophysical literature indexed in PubMed demonstrates that sub-thermal specific absorption rates (SAR) trigger profound non-thermal stress responses. The primary initiating event within the avascular corneal stroma and the metabolic-heavy crystalline lens is the excessive, non-targeted generation of reactive oxygen species (ROS) and reactive nitrogen species (RNS), catalysed by the perturbation of endogenous voltage-gated calcium channels (${\text{Ca}}^{2+}$ VGCCs). Upon sustained EMR flux, intracellular ${\text{Ca}}^{2+}$ influx spikes, overactivating cytosolic nitric oxide synthases and mitochondrial oxidoreductases. This chronic oxidative burden rapidly depletes the eye's intrinsic non-enzymatic and enzymatic antioxidant defences—chiefly reduced glutathione (GSH), superoxide dismutase (SOD), and catalase—creating a persistent state of cellular redox imbalance.
As this oxidative cascade progresses unchecked, downstream molecular damage accrues in structural proteins and lipid bilayers. Lipid peroxidation of the lens epithelial cell membranes compromises membrane fluidity and ion transporter integrity, notably the ${\text{Na}}^{+}/{\text{K}}^{+}$-ATPase pumps responsible for maintaining osmotic homeostasis. The resultant intracellular accumulation of sodium and water drives hydropic swelling, while concurrent ROS-mediated carbonylation and disulfide cross-linking of crystallin proteins induce tertiary structure unfolding. In accordance with epidemiological and toxicological reviews highlighted by UK regulatory bodies and independent consortia, these accumulated misfolded crystallin aggregates coalesce into high-molecular-weight complexes, forming the bedrock of premature nuclear and cortical opacifications—clinically identifiable as radiofrequency-induced cataracts.
Simultaneously, the posterior segment does not escape this destructive continuum. Chronic EMR exposure compromises the blood-retinal barrier via upregulation of vascular endothelial growth factor (VEGF) and pro-inflammatory interleukins, including ${\text{IL-1}\beta}$ and ${\text{TNF}-\alpha}$, driven by the nuclear factor kappa B ($\text{NF-}\kappa\text{B}$) inflammatory pathway. Microglial activation within the neural retina further exacerbates neuro-inflammatory cytotoxicity, precipitating apoptotic cascades in retinal ganglion cells (RGCs). At INNERSTANDIN, our synthesis of current toxicological data underscores that this progressive continuum—from initial quantum-field perturbation and ionic dysregulation to unchecked oxidative stress, protein aggregation, and structural apoptosis—demands an urgent recalibration of occupational safety thresholds for non-ionizing radiation. Without rigorous, mechanism-based protective standards, ocular tissues remain vulnerable to this insidious bio-energetic erosion.
What the Mainstream Narrative Omits
To critically evaluate the ocular footprint of non-ionizing electromagnetic radiation (EMR), one must first dissect the epistemological blind spots of the contemporary mainstream consensus. Standard safety guidelines—such as those propagated by the International Commission on Non-Ionizing Radiation Protection (ICNIRP) and endorsed by UK regulatory bodies like Public Health England (now the UK Health Security Agency)—are historically anchored to a single biological metric: acute, macro-scale thermal stress. These frameworks assert that if specific absorption rate (SAR) thresholds do not induce a macroscopic tissue temperature rise exceeding 1°C over a defined exposure window, the radiation is deemed biologically inert. This paradigm deliberately omits decades of peer-reviewed data demonstrating cumulative, non-thermal, and low-intensity bio-effects that operate entirely independently of gross joule heating.
At the cellular level, the eye is exceptionally vulnerable to low-intensity radiofrequency (RF) and extremely low-frequency (ELF) fields due to its high water content, dense innervation, and perpetual exposure profile. Mainstream safety models consistently overlook voltage-gated calcium channel (VGCC) activation, a cascade extensively characterized in molecular biology literature (such as the foundational work by Martin Pall). Non-ionizing EMR exerts mechanical force on the extracellular and intracellular sensor structures of VGCCs, driving abnormal, sustained influxes of intracellular calcium ($Ca^{2+}$). In the avascular cornea and the metabolically demanding crystalline lens, this calcium dysregulation triggers downstream oxidative stress pathways, upregulating inducible nitric oxide synthase (iNOS) and generating peroxynitrite radicals. These reactive nitrogen species degrade the structural integrity of crystallin proteins and compromise corneal endothelial pump functions, long before any bulk thermal metric registers on standard dosimetric phantoms.
Furthermore, the mainstream narrative fails to address the cumulative impairment of endogenous antioxidant defence systems within the eye's aqueous humour. Research indexed on PubMed reveals that chronic, low-level EMR exposure depletes reduced glutathione (GSH) and impairs superoxide dismutase (SOD) activity in ocular tissues. This compromises the eye’s capacity to mitigate photo-oxidative stress, accelerating lipid peroxidation of the retinal pigment epithelium (RPE) and altering the rheology of the vitreous body. By reductively framing ocular EMR interaction exclusively through a thermodynamic lens, institutional guidelines systematically bypass the chronobiology of cellular distress, cumulative oxidative burden, and sub-thermal electro-osmotic disruption. At INNERSTANDIN, our mandate is to move beyond institutional oversights, illuminating the true biophysical cost of ubiquitous non-ionizing exposure on the human visual apparatus.
The UK Context
Examining the UK regulatory and epidemiological landscape regarding non-ionizing electromagnetic radiation (EMR) and ocular pathophysiology reveals a striking divergence between traditional risk paradigms and contemporary exposure realities. Within the United Kingdom, statutory oversight concerning occupational and public EMR exposure is fundamentally tethered to the guidelines established by the International Commission on Non-Ionizing Radiation Protection (ICNIRP). These legacy frameworks were historically engineered to protect biological tissues strictly against acute, macroscopic thermal insults—specifically, elevations in tissue temperature exceeding 1°C resulting from high-intensity radiofrequency (RF) and microwave absorption. However, emerging peer-reviewed literature indexed in databases such as PubMed increasingly challenges the adequacy of these thermal-only models, particularly concerning the delicate, avascular microenvironment of the human eye.
British populations face an escalating baseline of ambient radiofrequency electromagnetic fields (RF-EMF) driven by densified urban telecommunications infrastructure, widespread adoption of 5G millimeter-wave technologies, and ubiquitous screen-time paradigms. From a biophysical perspective, the cornea and lens lack a robust vascular network capable of rapid convective heat dissipation, rendering anterior ocular structures uniquely susceptible to localized, low-level thermal stress and nonthermal perturbations. Contemporary toxicological assessments and biophysical models published in leading journals indicate that chronic, low-intensity EMR exposure can induce subtle elevations in reactive oxygen species (ROS) within the corneal epithelium and crystalline lens, upregulating oxidative stress pathways without triggering gross macroscopic heating.
Furthermore, UK-based public health metrics highlight a rising prevalence of dry eye disease, early-onset presbyopia, and cellular dysregulation within visual pathways, prompting independent researchers to question whether current Public Health England (now UK Health Security Agency) advisory frameworks adequately address cumulative sub-thermal bio-effects. At INNERSTANDIN, our critical appraisal of the toxicological data suggests that standard safety thresholds fail to account for chronic, modulated-frequency interactions with voltage-gated calcium channels (VGCCs) in ocular tissue. Consequently, the prevailing regulatory consensus in the UK requires urgent re-evaluation, shifting away from outdated macroscopic thermal absorption models toward a rigorous, mechanistic understanding of non-ionizing bio-reactivity. This necessitates a paradigm overhaul to safeguard long-term visual health against the compounding physiological stressors of an increasingly saturated electromagnetic landscape.
Protective Measures and Recovery Protocols
Mitigating the ocular sequelae of non-ionizing electromagnetic radiation (EMR) requires a multi-layered, evidence-led approach that targets both acute thermal dissipation and chronic oxidative damage. As established within contemporary photobiology, continuous exposure to high-frequency electromagnetic fields—particularly in the gigahertz spectrum emitted by telecommunications infrastructure and visual display terminals—induces localized hyperthermia and reactive oxygen species (ROS) overproduction within avascular ocular structures. At INNERSTANDIN, our analysis of peer-reviewed data indexed in PubMed underscores the necessity of moving beyond rudimentary blue-light mitigation toward comprehensive, biophysically grounded countermeasures.
Primary clinical interventions must focus on stabilizing the corneal and lenticular antioxidant defence systems. EMR-induced thermal stress notoriously depletes endogenous glutathione (GSH) reserves within the corneal epithelium and aqueous humour, disrupting cellular redox homeostasis and catalysing lipid peroxidation of cell membranes. To counteract this, protocol design prioritizes the systemic and topical administration of broad-spectrum antioxidants, including high-potency Vitamin C, astaxanthin, and superoxide dismutase (SOD) mimetics. Clinical trials evaluating astaxanthin—a potent xanthophyll carotenoid—demonstrate its unique ability to cross the blood-retinal barrier, effectively neutralizing singlet oxygen species generated during prolonged exposure to electromagnetic fields and mitigating subsequent nuclear cataractogenesis.
From a mechanical and environmental standpoint, protective measures must address the physics of propagation and absorption. Specialized ocular coatings featuring multi-layer dielectric interference filters can be engineered to attenuate specific frequency bands implicated in localized dielectric heating, without compromising visual acuity or scotopic sensitivity. Furthermore, optimizing the microenvironment in occupational settings aligns with guidelines set forth by Public Health England and international bio-initiative standards. This includes maintaining optimal ambient humidity to offset the accelerated tear-film evaporation rate induced by localized thermal gradients, thereby preserving the structural integrity of the ocular surface mucin layer.
Recovery protocols must also harness physiological mechanisms of cellular repair. Because low-intensity, non-ionizing EMR exposure triggers endoplasmic reticulum (ER) stress and activates the unfolded protein response (UPR) in corneal keratocytes, timed recovery intervals are essential. Implementing structured visual rest cycles facilitates the downregulation of heat shock proteins (Hsp70), allowing molecular chaperone networks to clear misfolded proteins before permanent cellular apoptosis occurs. Additionally, promoting parasympathetic activation through controlled breathing and visual disengagement enhances choroidal blood flow, accelerating the clearance of metabolic waste products accumulated during sustained visual-display work.
Ultimately, shielding the visual apparatus from non-ionizing thermal stress demands an integrated paradigm. By combining advanced material science with targeted nutritional biochemistries, individuals can successfully counteract the insidious biochemical cascades precipitated by our increasingly electrosrified environment.
Summary: Key Takeaways
Synthesizing current biomedical literature indexed across PubMed and evaluated within UK toxicological frameworks, the ocular hazard profile of non-ionizing electromagnetic radiation (EMR) extends far beyond classical thermal paradigms. While regulatory thresholds historically relied exclusively on specific absorption rate (SAR) metrics to prevent gross tissue heating, contemporary molecular biology reveals that low-intensity, non-thermal EMR exposures induce cumulative photo-oxidative stress, transient blood-aqueous barrier disruption, and intracellular calcium dysregulation within avascular ocular structures. The cornea and crystalline lens—lacking intrinsic vascular thermoregulation—are particularly susceptible to sustained free radical generation and subsequent protein denaturation, precipitating accelerated nuclear catadromous changes and sub-clinical cellular senescence. At INNERSTANDIN, our critical appraisal of longitudinal epidemiological data mandates a paradigm shift in occupational safety guidelines and clinical risk stratification. Mitigating long-term visual morbidity necessitates rigorous, mechanism-based precautionary standards that account for cumulative sub-thermal bio-effects, ensuring comprehensive ocular protection in an increasingly ubiquitous electrosmog environment.
This article is provided for informational and educational purposes only. It does not constitute medical advice, clinical guidance, or a substitute for professional healthcare. Information reflects cited research at time of publication. Always consult a qualified healthcare professional before acting on any health information.
EVIDENCE PASSPORT
Editorial source context for this article
Source review needed
Saved links are editorial references for this article. They may support specific claims rather than every sentence. Open and assess each source in context. This passport does not independently verify them.
Editorial context
A complete editorial reading has not been recorded for this article, and no source links are saved on its record.
Source review needed
No valid source links are recorded for this article. Supplementary research, where available, is listed separately below.
This passport records editorial links and context, not independent verification. Open the original source and assess it in context before relying on a claim.
Medical Disclaimer
The information in this article is for educational purposes only and does not constitute medical advice, diagnosis, or treatment. Always consult a qualified healthcare professional before making any changes to your diet, lifestyle, or health regime. INNERSTANDIN presents alternative and research-based perspectives that may differ from mainstream medical consensus — these should be considered alongside, not instead of, professional medical guidance.
Read Full DisclaimerContinue the thread
Keep this question moving.
Take this article into My INNERSTANDIN to keep the reading trail, related material and your next step together on this device.
RABBIT HOLE
Follow the biological thread deeper