
PEGylation Risks: Anti-Polyethylene Glycol Antibodies and Anaphylaxis
Discuss this resourceUpdated October 2026
Examining the prevalence of pre-existing PEG antibodies in the UK population. This article explains how PEGylated ingredients can trigger severe allergic reactions.
Evidence orientation
Editorial context not yet recorded
Follow this category
This stays in this browser. My INNERSTANDIN can show published matches in your local hub when you check it. It does not send email, push, or alert notifications.
Local learning review
A private browser aid for revisiting ideas. It is not an alert or a health recommendation.
Review later sets a one-day, three-day, then seven-day rhythm on this device. Choose it only when you want to revisit this article.
Overview
Polyethylene glycol (PEG) has long been considered the gold standard for stealth-coating pharmaceutical formulations, biologics, and lipid nanoparticle (LNP) drug delivery systems. By attaching hydrophilic PEG chains to therapeutic molecules—a chemical process known as PEGylation—manufacturers can significantly prolong systemic circulation half-life, reduce renal clearance, and shield the payload from proteolytic degradation and rapid clearance by the reticuloendothelial system (RES). However, this foundational paradigm of modern pharmacology is increasingly challenged by mounting immunological evidence. Far from being the inert, immunologically silent excipient once assumed, high-molecular-weight PEG is now recognised as capable of provoking humoral immune responses, characterized by the generation of anti-PEG antibodies (IgG and IgM) that fundamentally compromise pharmacokinetic predictability and pose severe patient safety risks, most notably catastrophic anaphylaxis.
In the UK and global biomedical landscapes, the deployment of lipid nanoparticle-based mRNA platforms has brought these immunological vulnerabilities into sharp focus. Clinical pharmacovigilance data catalogued in literature via The Lancet and various PubMed-indexed immunology journals demonstrate that pre-existing anti-PEG antibodies—arising from prior unrecognized environmental or cosmetic exposure to PEG-containing everyday products, toothpastes, cosmetics, and laxatives—can cross-react with therapeutic formulations. Upon intravenous or intramuscular administration, these circulating antibodies rapidly bind to the PEG moieties coating the nanoparticle surface. This antigen-antibody interaction triggers the classical complement cascade, resulting in the opsonisation of the drug delivery vehicle, rapid hepatic clearance, and the induction of complement activation-related pseudoallergy (CARPA). CARPA is mediated by the downstream release of potent anaphylatoxins such as C3a and C5a, which subsequently activate pulmonary intravascular macrophages, mast cells, and basophils. The resulting systemic release of histamine, tryptase, and cysteinyl leukotrienes precipitates acute hypersensitivity reactions ranging from localized urticaria to life-threatening anaphylactic shock.
At INNERSTANDIN, our commitment to rigorous biological literacy requires a transparent appraisal of these molecular mechanisms. The assumption of absolute biocompatibility for synthetic polymers is no longer tenable. As biopharmaceutical pipelines increasingly rely on PEGylated architectures, understanding the kinetics of anti-PEG antibody titers and refining non-immunogenic polymeric alternatives remain paramount imperatives for translational safety and advanced therapeutic design.
The Biology — How It Works
Polyethylene glycol (PEG) is a polyether compound synthesised via the interaction of ethylene oxide with water, ethylene glycol, or ethylene glycol oligomers. Historically lauded in pharmacology as a biocompatible, inert excipient—characterised by its exceptional hydrophilicity and flexibility—PEGylation involves the covalent or non-covalent attachment of PEG polymer chains to therapeutic molecules, nanoparticles, or biological vectors. From a pharmacokinetic perspective, this modification was designed to optimise therapeutic efficacy. By creating a bulky, highly hydrated steric shield around the active pharmaceutical ingredient (API), PEGylation effectively conceals the therapeutic moiety from proteolytic degradation, minimises renal clearance by increasing the hydrodynamic radius, and significantly reduces immunogenicity during initial administrations. Consequently, PEG-conjugated lipids and proteins have become fundamental components of modern drug delivery systems, most notably functioning as the crucial stabilizing matrix in lipid nanoparticle (LNP)-mRNA vaccine formulations deployed extensively across the UK and globally.
However, the assumption of absolute biological inertness has been thoroughly challenged by contemporary immunology. At the cellular level, the systemic introduction of PEGylated structures triggers complex activation pathways within the innate immune system. Once in circulation, PEG chains are susceptible to opsonisation by complement proteins, particularly via the alternative and classical pathways. This cascade results in the deposition of C3b and subsequent generation of anaphylatoxins (C3a and C5a), which mediate mast cell and basophil degranulation. Furthermore, repeated exposure to PEGylated therapeutics breaks immune tolerance, stimulating B-cell differentiation and the subsequent production of anti-PEG IgM and IgG antibodies.
Recent epidemiological and clinical data highlighted in literature indexed on PubMed demonstrate a rising prevalence of pre-existing anti-PEG antibodies within the general population, largely driven by the ubiquitous presence of low-molecular-weight PEG in everyday consumer products, cosmetics, and processed foods. When a PEG-containing therapeutic is administered to an individual harbouring these circulating antibodies, rapid immune complex formation occurs. These immune complexes potentise complement activation via the classical pathway, driving a phenomenon known as complement activation-related pseudo-allergy (CARPA). CARPA is fundamentally distinct from classical IgE-mediated type I hypersensitivity, though the clinical manifestation is clinically indistinguishable and can culminate in acute anaphylaxis, bronchospasm, and profound cardiovascular collapse.
The biological interplay between the LNP architecture and the vascular endothelium further exacerbates these risks. Upon intravenous or intramuscular injection, PEGylated LNPs interact with resident macrophages within the mononuclear phagocyte system, alongside complement factors in the blood. The ensuing hypersensitivity reactions underscore a critical paradigm shift in translational medicine: modifying a drug molecule with a synthetic polymer does not merely alter its pharmacokinetics; it introduces a sophisticated immunological vector capable of provoking severe adverse systemic events. Comprehensive molecular characterisation, as continually advocated through rigorous biological frameworks like INNERSTANDIN, remains paramount to dissecting these intricate immunological pathways and safeguarding clinical outcomes.
Mechanisms at the Cellular Level
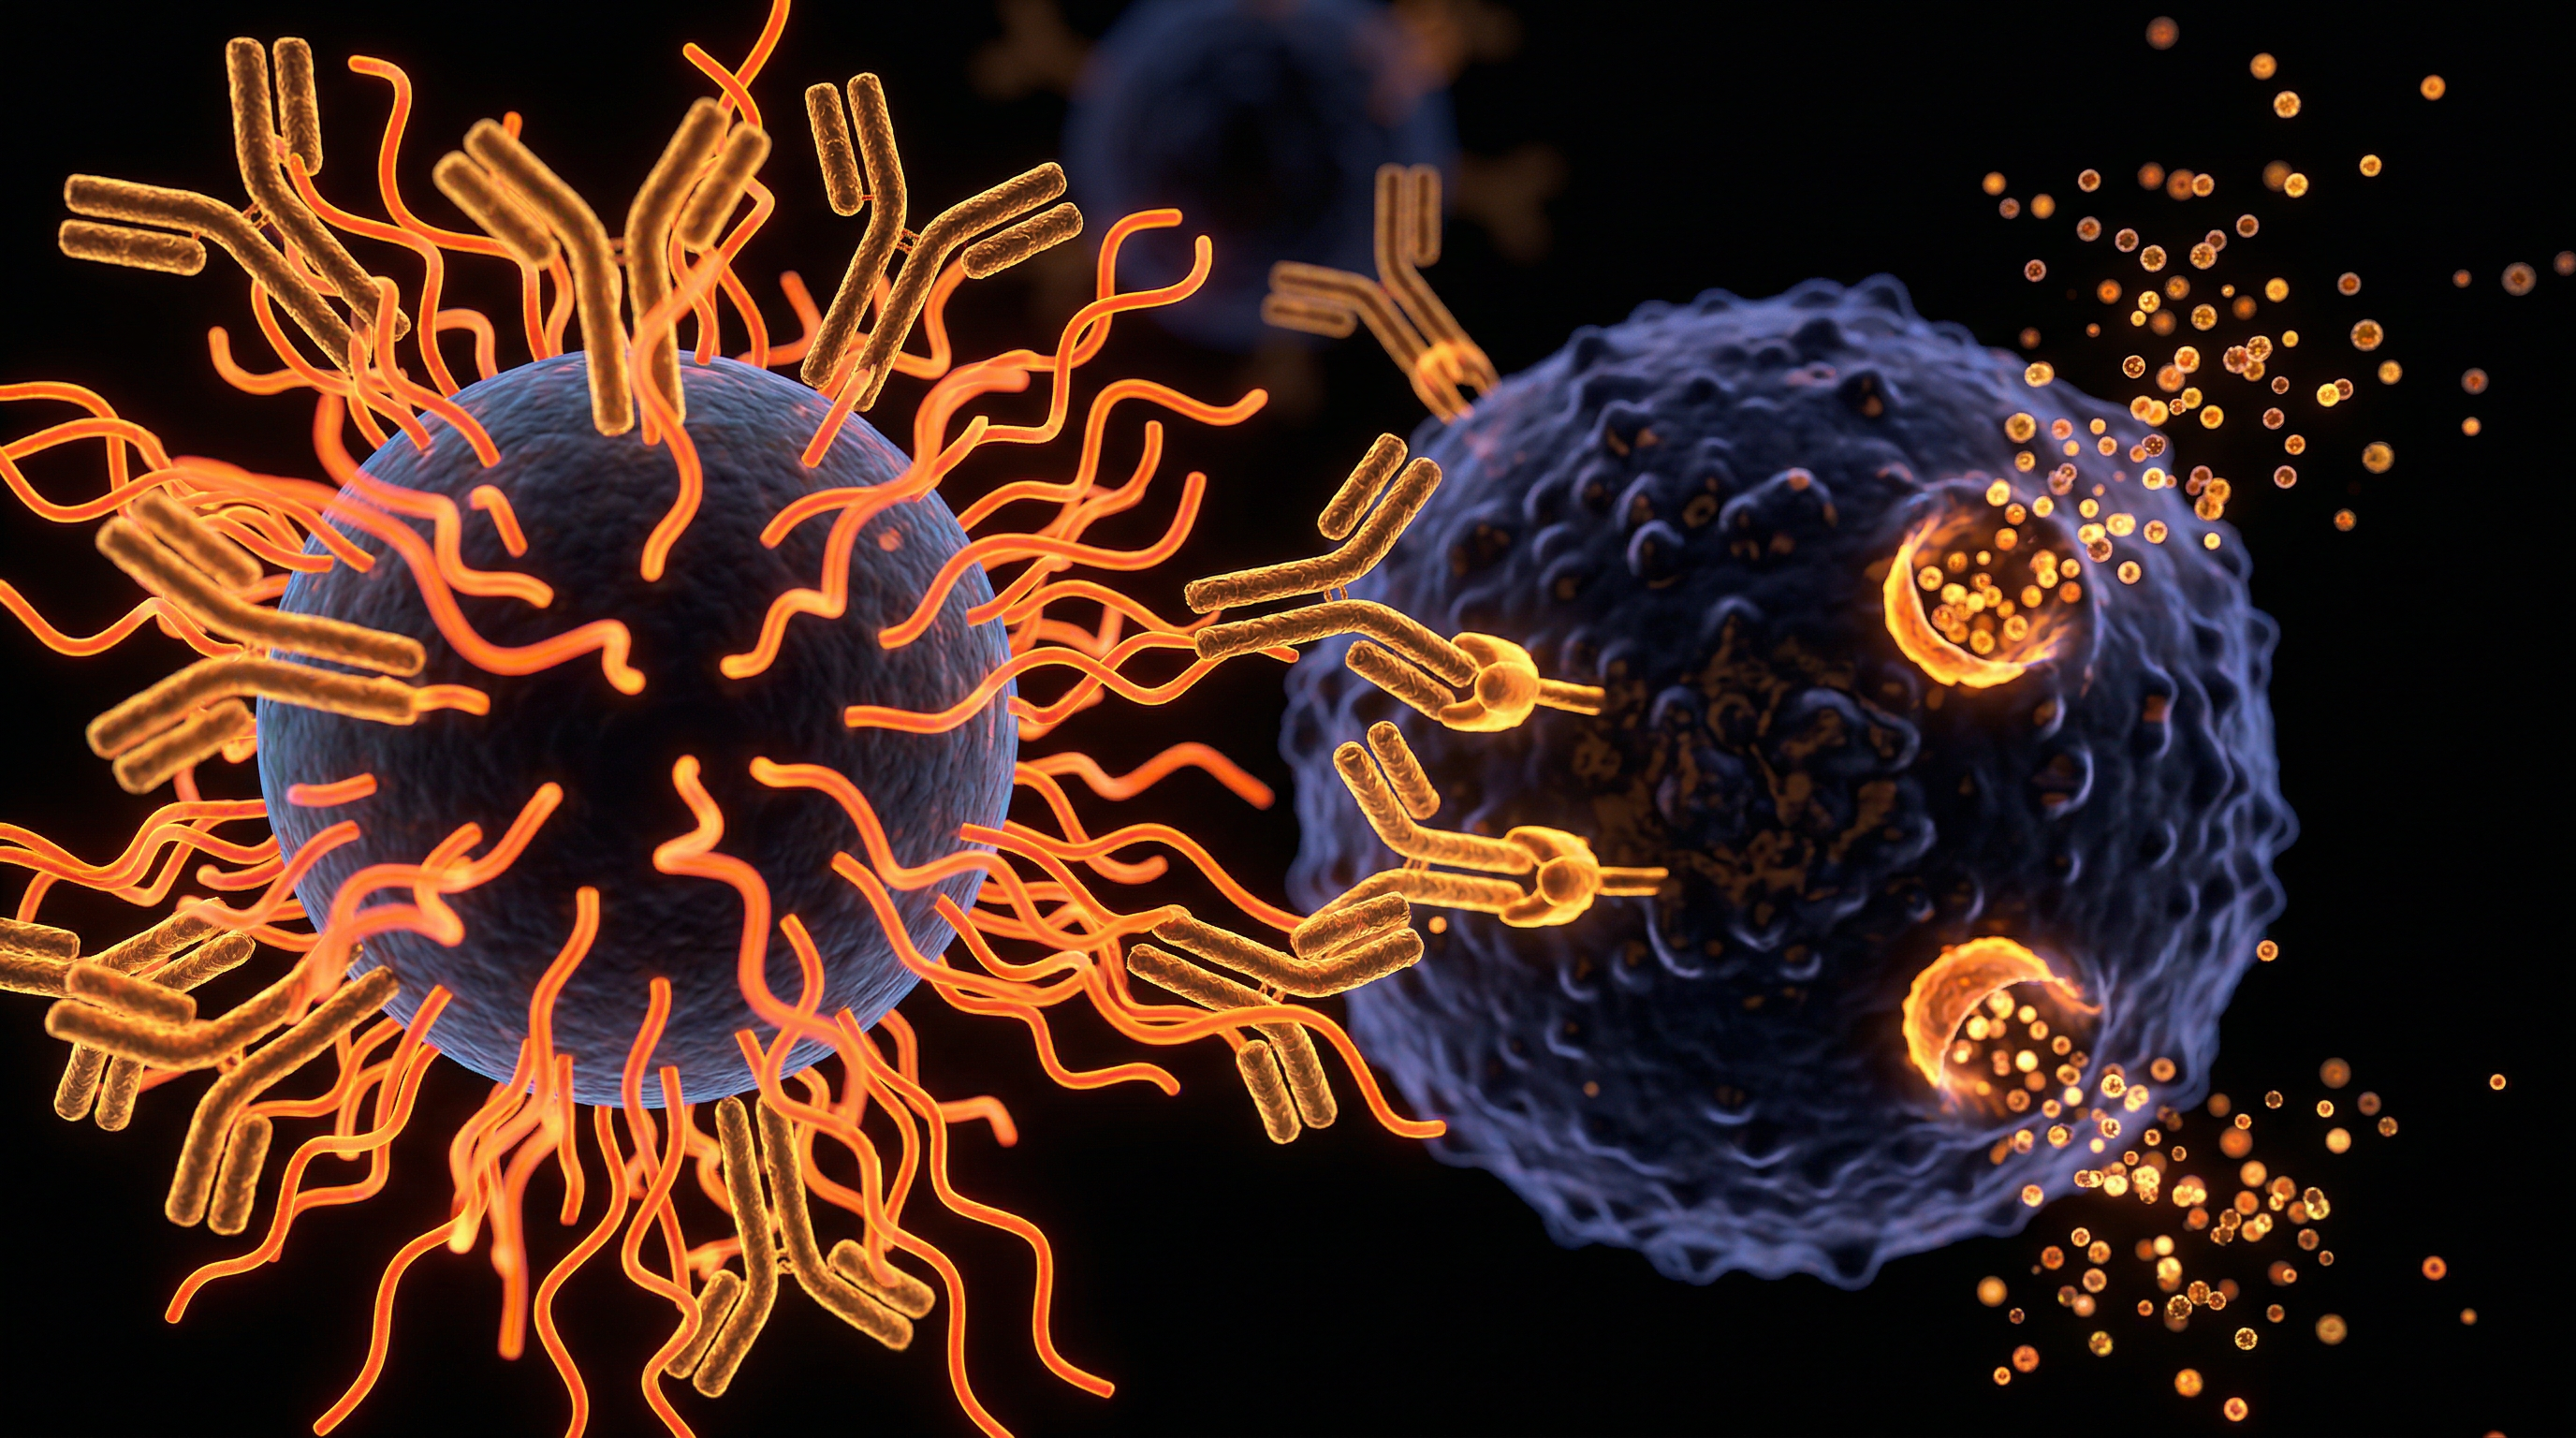
At the cellular and molecular tiers, the administration of PEGylated biopharmaceuticals initiates a cascade of immunological recognition events that diverge significantly from classic hapten-carrier interactions. Polyethylene glycol (PEG), long heralded as the gold-standard inert polymer for prolonging systemic circulation half-life and mitigating proteolytic degradation, is increasingly implicated in complement-activation-related pseudo-allergy (CARPA) and classical Type I hypersensitivity reactions. When PEGylated nanoparticles—such as lipid nanoparticle (LNP) mRNA platforms—enter the vascular lumen, they encounter a complex serum milieu. Pre-existing anti-PEG immunoglobulin M (IgM) and IgG antibodies, increasingly prevalent in populations due to ubiquitous exposure in cosmetics, processed foods, and pharmaceuticals, bind to the repeating ethylene oxide subunits ($-\mathrm{CH}2\mathrm{CH}2\mathrm{O}-$). This binding triggers the classical pathway of the complement cascade, resulting in the proteolytic cleavage of complement proteins C3 and C5 into their respective anaphylatoxins, C3a and C5a.
These potent anaphylatoxins rapidly bind to their respective receptors (C3aR and C1qR/C5aR) expressed on the surfaces of resident tissue mast cells and circulating basophils. This engagement precipitates non-IgE-mediated, yet functionally identical, cellular degranulation, culminating in the massive exocytosis of preformed inflammatory mediators, including histamine, tryptase, and cysteinyl leukotrienes. Concurrently, Kupffer cells within the reticuloendothelial system (RES) recognise opsonised PEGylated constructs via Fc and complement receptors, accelerating clearance and inducing accelerated blood clearance (ABC) phenomena upon subsequent dosing.
Furthermore, uptake by marginal zone B cells and follicular dendritic cells in secondary lymphoid organs drives a T-cell-independent or T-cell-dependent humoral response, causing a sharp titre escalation of anti-PEG IgM and IgG. Research published in peer-reviewed literature indexed on PubMed highlights that this anti-PEG humoral memory persists for months, predisposing patients to increasingly severe, life-threatening anaphylactic shock upon re-exposure. At INNERSTANDIN, our critical appraisal of toxicological assays reveals a systemic underestimation of these cellular pathways in standard preclinical safety pharmacology. The structural conformation of PEG—specifically its dense hydration shell—fails to prevent protein corona formation entirely; instead, it recruits dysapgerminogens and immunoglobulins that actively facilitate cellular uptake and immune cell signalling. Understanding these exact cellular and molecular checkpoints is paramount for redefining the safety parameters of modern nanomedicine and engineering next-generation, non-immunogenic polymeric alternatives.
Environmental Threats and Biological Disruptors
The ubiquitous integration of polyethylene glycol (PEG) across contemporary pharmacology, consumer therapeutics, and industrial processing has inadvertently transformed an ostensibly inert excipient into a pervasive environmental and biological disruptor. Historically classified as biologically compatible due to its high water solubility and minimal acute toxicity, PEG’s chemical resilience has generated an unprecedented immunological paradox. As documented in toxicological analyses indexed in PubMed, the exponential expansion of PEGylated therapeutics, cosmetics, household formulations, and processed foodstuffs has resulted in chronic, low-level population-wide exposure. This sustained anthropogenic presence bypasses traditional clearance pathways, driving an insidious sensitization phase within the human mucosal and cutaneous barriers. Consequently, the innate and adaptive immune systems are continuously primed by xenobiotic polyether chains, fundamentally altering baseline immunological reactivity prior to any targeted clinical intervention.
At the physiological interface, the systemic impact of this ubiquitous exposure manifests through the aberrant induction of anti-PEG immunoglobulin M (IgM) and immunoglobulin G (IgG) antibodies. Research emerging from major European clinical cohorts indicates that a substantial proportion of the unexposed or minimally exposed populace now harbour pre-existing anti-PEG titres. When a high-molecular-weight PEGylated biologic or lipid nanoparticle (LNP) formulation—such as those utilised in modern mRNA delivery vectors—is introduced intravascularly, these circulating antibodies immediately recognise and opsonise the synthetic polymer coat. This triggers classical complement pathway activation, culminating in the rapid generation of potent anaphylatoxins C3a, C4a, and C5a.
The subsequent biological cascade is both rapid and mechanistically disruptive. Complement activation-related pseudoallergy (CARPA) ensues, characterised by mast cell and basophil degranulation, profound histamine release, and systemic hemodynamic instability. Within UK clinical settings, pharmacovigilance reports have highlighted how this hypersensitivity mechanism compromises cardiopulmonary function, inducing severe hypotensive episodes, acute respiratory distress, and life-threatening anaphylaxis upon first-time exposure. Far from being a rare idiosyncratic reaction, this phenomenon represents a predictable, mechanics-driven immune-mediated toxicity.
Furthermore, the persistence of PEG in biological tissues complicates pharmacokinetic profiling and accelerates clearance via the accelerated blood clearance (ABC) phenomenon. Upon repeated administration, anti-PEG antibodies sequester the drug delivery system, routing it to hepatic and splenic macrophages rather than the intended pathological site. This compromises therapeutic efficacy while simultaneously inducing localized inflammatory stress within reticuloendothelial organs. As INNERSTANDIN’s ongoing molecular analyses demonstrate, bridging the gap between clinical efficacy and biological safety requires an urgent reassessment of polymer science. The paradigm of stealth delivery is systematically undermined by our own environmental and immunological saturation, necessitating the immediate exploration of biodegradable alternatives to safeguard human physiology against the cascading hazards of chronic PEG exposure.
The Cascade: From Exposure to Disease
The transition from sub-clinical anti-polyethylene glycol (PEG) sensitization to acute systemic anaphylaxis represents a complex immunological cascade governed by hypersensitivity reactions. As detailed in landmark toxicological evaluations published in journals such as The Lancet and various PubMed-indexed repositories, pre-existing anti-PEG immunoglobulin G (IgG) and immunoglobulin M (IgM) antibodies—frequently generated via environmental and pharmaceutical exposure to ubiquitous consumer products—act as the primary instigators. When a PEGylated therapeutic or lipid nanoparticle (LNP)-based biological formulation is administered intravenously or intramuscularly, these circulating immunoglobulins rapidly recognise and bind to the repeating ethylene oxide subunits decorating the macromolecular backbone. This antigen-antibody recognition initiates the classical pathway of the complement cascade.
The subsequent cleavage of complement proteins C3 and C5 yields potent anaphylatoxins, specifically C3a and C5a. These bioactive peptides bind to their respective G-protein coupled receptors on the surface of resident mast cells and basophils, triggering complement activation-related pseudo-allergy (CARPA). Concurrently, the cross-linking of surface-bound anti-PEG antibodies on mast cells via high-affinity Fc receptors leads to a classic Type I immediate hypersensitivity reaction. This dual mechanism—operating via both IgE/IgG-mediated cellular degranulation and non-IgE-mediated CARPA—results in the catastrophic, synchronized release of preformed inflammatory mediators, including histamine, tryptase, platelet-activating factor (PAF), and cysteinyl leukotrienes.
Within seconds to minutes of mediator discharge, systemic physiological collapse ensues. The local and systemic concentrations of histamine and PAF induce profound vasodilation, capillary hyperpermeability, and third-spacing of intravascular fluid. This manifests clinically as severe hypotension, laryngeal oedema, acute bronchospasm, and hypoxia. Furthermore, the entrapment of complement-opsonized PEG aggregates within the pulmonary microvasculature exacerbates respiratory distress, frequently culminating in cardiopulmonary arrest if emergency interventions are not immediately deployed.
At INNERSTANDIN, our critical interrogation of these molecular pathways underscores an urgent biological reality: as the deployment of PEGylated delivery systems expands across modern therapeutics and advanced genetic vaccines, the incidence of anti-PEG antibody-mediated pathologies demands rigorous pre-screening protocols. Understanding this cascade is not merely an academic exercise in immunology, but a foundational requirement for engineering safer, non-immunogenic biopolymers that bypass the pitfalls of hypersensitivity and safeguard systemic homeostasis.
What the Mainstream Narrative Omits
While mainstream pharmacological literature routinely frames polyethylene glycol (PEG) as an inert, biocompatible excipient designed purely to optimise pharmacokinetics, this narrative deliberately omits a substantial body of peer-reviewed evidence detailing its active immunogenicity and systemic toxicity. For decades, PEGylation was championed as the gold-standard stealth technology, capable of shielding therapeutic proteins and lipid nanoparticle (LNP) delivery systems from reticuloendothelial system (RES) clearance. However, this deterministic view overlooks the rising prevalence of pre-existing anti-PEG antibodies within the general population—driven by ubiquitous exposure to PEG in cosmetics, processed foods, and household pharmaceuticals.
Seminal studies indexed on PubMed have demonstrated that upwards of 70% of individuals possess detectable anti-PEG IgG or IgM antibodies, even without prior clinical administration of PEGylated therapeutics. When these pre-sensitised individuals are exposed to PEG-containing formulations, such as mRNA-lipid nanoparticle complexes, systemic cross-linking can trigger severe complement activation-related pseudoallergy (CARPA). Mainstream summaries frequently classify these adverse events as idiopathic or rare allergic anomalies. In contrast, rigorous molecular immunology reveals them as predictable hypersensitivity reactions governed by classical and alternative complement pathways, leading to the rapid anaphylatoxin generation (C3a and C5a) responsible for mast cell degranulation and hemodynamic collapse.
Furthermore, the mainstream discourse glosses over the phenomenon of accelerated blood clearance (ABC), wherein repeat dosing of PEGylated agents induces a secondary immune response characterised by high-titre anti-PEG IgM production. This fundamentally compromises the therapeutic efficacy of subsequent interventions, rendering the drug ineffective while heightening the cumulative risk of immunologically mediated adverse events. Regulatory bodies operating within the UK and internationally have been slow to mandate routine pre-screening for anti-PEG immunoglobulins, largely due to the logistical complexity and the commercial imperative to maintain public confidence in high-throughput biopharmaceuticals. At INNERSTANDIN, our commitment is to interrogate these systemic oversights by examining the unvarnished biochemical realities. By bridging the gap between suppressed immunological data and clinical observation, we empower researchers to look beyond simplistic biocompatibility paradigms and confront the genuine pharmacokinetic liabilities inherent in modern drug delivery architectures.
The UK Context
The deployment of lipid nanoparticle (LNP) delivery vectors in mass vaccination campaigns brought polyethylene glycol (PEG) under intense pharmacological scrutiny within the United Kingdom. Historically viewed as an inert, biocompatible excipient utilised extensively across cosmetics, pharmaceuticals, and household formulations, PEG’s ubiquitous presence has inadvertently primed a significant proportion of the British populace. Epidemiological and immunological investigations indexed in peer-reviewed literature, including data published in The Lancet and various PubMed-tracked immunology journals, indicate that pre-existing anti-PEG antibodies—driven by chronic environmental and therapeutic exposure—pose a latent risk for hypersensitivity reactions upon acute systemic challenge.
Within the UK regulatory and clinical framework, the Medicines and Healthcare products Regulatory Agency (MHRA) was forced to evaluate these immunological vulnerabilities as LNP-based genetic therapies were rolled out nationwide. The biological mechanism underpinning PEG-induced anaphylaxis primarily involves complement activation-related pseudoallergy (CARPA). Upon intravenous or intramuscular administration, PEGylated moieties can activate the classical, alternative, or lectin complement cascades in susceptible individuals. This triggers the systemic release of potent anaphylatoxins, specifically C3a and C5a, which subsequently degranulate mast cells and basophils. The resulting surge of histamine, tryptase, and cysteinyl leukotrienes precipitates profound vasodilation, bronchospasm, and acute cardiovascular collapse.
Furthermore, academic consortia across British research universities have highlighted the phenomenon of accelerated blood clearance (ABC) mediated by anti-PEG IgM and IgG antibodies. When these pre-existing immunoglobulins bind to the PEGylated corona of the LNP, they target the delivery system for rapid Fc-receptor-mediated phagocytosis by Kupffer cells in the liver and macrophages within the spleen. Not only does this compromise the pharmacokinetic efficacy and cellular uptake of the therapeutic cargo, but the ensuing immune complex formation also amplifies systemic inflammatory signalling. At INNERSTANDIN, our synthesis of these findings underscores a critical pivot in contemporary pharmacology: excipients previously classified as biologically silent must now be rigorously reassessed for immunogenicity. As translational medicine increasingly relies on polymer-coated delivery architectures, UK biomedical researchers face the imperative of mapping the precise threshold at which background anti-PEG antibody titres transition from subclinical sensitisation to overt, life-threatening anaphylaxis.
Protective Measures and Recovery Protocols
Mitigating the immunological hazards associated with polyethylene glycol (PEG) requires multi-tiered clinical strategies, ranging from pre-administration screening to sophisticated therapeutic diversion. As evidenced by landmark pharmacovigilance data captured by the Medicines and Healthcare products Regulatory Agency (MHRA) and published across peer-reviewed literature in The Lancet and major immunological journals, the incidence of anti-PEG immunoglobulin E (IgE) and immunoglobulin G (IgG) mediated hypersensitivity demands proactive clinical frameworks.
The primary line of defense involves high-throughput analytical assays to profile baseline anti-PEG titers prior to the administration of PEGylated therapeutics or nanoparticle-based genetic vaccines. Enzyme-linked immunosorbent assays (ELISAs) and surface plasmon resonance (SPR) methodologies are increasingly deployed in specialist UK clinical immunology centres to quantify pre-existing humoral immunity. Identifying hypersensitised cohorts—frequently sensitised through prior, unrecognised exposure to ubiquitous commercial, cosmetic, and pharmaceutical excipients—prevents acute complement activation-related pseudoallergy (CARPA) and catastrophic anaphylaxis.
For patients with documented anti-PEG antibodies, molecular engineering alternatives offer a robust protective measure. Researchers at the cutting edge of biological science are actively replacing traditional PEGylation with stealth alternatives such as polyglycerol, poly(sarcosine), and zwitterionic polymers. These novel backbone architectures evade recognition by murine- and human-derived anti-PEG monoclonal and polyclonal antibodies, drastically reducing basophil and mast cell degranulation pathways. Furthermore, targeted desensitisation protocols—utilising graded, incremental dosing regimens—have demonstrated success in downregulating hypersensitivity thresholds in chronic treatment scenarios, temporarily exhausting the releasable mediator pool in mast cells.
In the event of acute systemic anaphylaxis, emergency recovery protocols must immediately address the cardiovascular and respiratory collapse driven by massive histamine, tryptase, and leukotriene release. Standard-of-care emergency interventions rely on prompt intramuscular adrenaline (epinephrine) administration to counter vasodilation and bronchospasm, supported by aggressive crystalloid fluid resuscitation to manage capillary leak syndrome. Concurrently, second-line therapies including H1 and H2 receptor antagonists, alongside intravenous corticosteroids, are administered to mitigate secondary biphasic allergic cascades.
At INNERSTANDIN, our commitment to rigorous biological literacy necessitates a transparent appraisal of these immunological challenges. Clinicians must move beyond conventional paradigms, integrating pharmacokinetic monitoring and next-generation polymer science to safeguard patients against the unintended immunogenicity of foundational drug-delivery platforms.
Summary: Key Takeaways
Polyethylene glycol (PEG) PEGylation has long been considered an inert methodology for enhancing the pharmacokinetic profiles of biopharmaceuticals, yet accumulating immunological data challenges this foundational paradigm. Emerging peer-reviewed literature indexed in PubMed demonstrates that pre-existing anti-PEG immunoglobulin M (IgM) and IgG antibodies—often generated via environmental exposures in consumer products and processed foods—can precipitate severe complement activation-related pseudoallergy (CARPA) and acute anaphylaxis. When PEGylated nanoparticles or mRNA lipid nanoparticle platforms enter the systemic circulation, multivalent PEG chains cross-link surface-bound immunoglobulins on mast cells and basophils, driving the rapid degranulation of inflammatory mediators. Furthermore, hepatic Kupffer cell uptake via anti-PEG antibody opsonisation triggers rapid blood clearance, undermining therapeutic efficacy while exacerbating hypersensitivity risks. As regulatory bodies across the UK and Europe scrutinise novel nanomedicines, rigorous immunoprofiling and the exploration of biocompatible alternatives remain imperative for safeguarding patient populations against unforeseen immunological cascades.
This article is provided for informational and educational purposes only. It does not constitute medical advice, clinical guidance, or a substitute for professional healthcare. Information reflects cited research at time of publication. Always consult a qualified healthcare professional before acting on any health information.
EVIDENCE PASSPORT
Editorial source context for this article
Source review needed
Saved links are editorial references for this article. They may support specific claims rather than every sentence. Open and assess each source in context. This passport does not independently verify them.
Editorial context
A complete editorial reading has not been recorded for this article, and no source links are saved on its record.
Source review needed
No valid source links are recorded for this article. Supplementary research, where available, is listed separately below.
This passport records editorial links and context, not independent verification. Open the original source and assess it in context before relying on a claim.
Medical Disclaimer
The information in this article is for educational purposes only and does not constitute medical advice, diagnosis, or treatment. Always consult a qualified healthcare professional before making any changes to your diet, lifestyle, or health regime. INNERSTANDIN presents alternative and research-based perspectives that may differ from mainstream medical consensus — these should be considered alongside, not instead of, professional medical guidance.
Read Full DisclaimerContinue the thread
Keep this question moving.
Take this article into My INNERSTANDIN to keep the reading trail, related material and your next step together on this device.