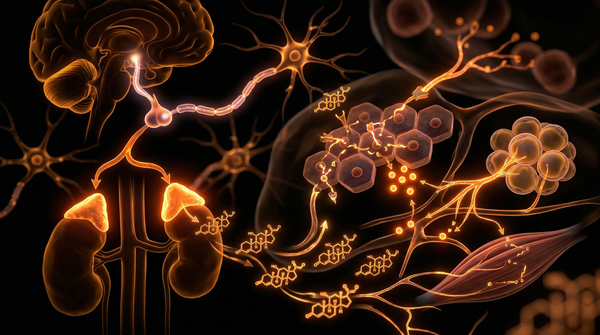
The Cortisol Awakening Response: Using Morning Light to Anchor Metabolic Health
Discuss this resourceUpdated October 2026
Investigate the physiological importance of the Cortisol Awakening Response (CAR) and how early morning photons reset the body's master clock. Learn how to leverage natural light to improve energy levels and hormonal balance.
Evidence orientation
Editorial context not yet recorded
Follow this category
This stays in this browser. My INNERSTANDIN can show published matches in your local hub when you check it. It does not send email, push, or alert notifications.
Local learning review
A private browser aid for revisiting ideas. It is not an alert or a health recommendation.
Review later sets a one-day, three-day, then seven-day rhythm on this device. Choose it only when you want to revisit this article.

Overview
The Cortisol Awakening Response (CAR) represents one of the most sophisticated neuroendocrine adaptations in mammalian chronobiology, distinct from the basal diurnal cortisol rhythm governed by the hypothalamic-pituitary-adrenal (HPA) axis. Characterised by a sharp surge in circulating free cortisol that typically peaks thirty to forty-five minutes post-awakening—often exhibiting a 50% to 75% increase over baseline nocturnal nadir levels—the CAR is not merely an artefact of waking, but an anticipatory metabolic boot sequence. As documented extensively in psychoneuroendocrinology literature via platforms such as PubMed, this acute secretory burst prepares the organism for the metabolic demands of the active phase, upregulating gluconeogenesis, mobilizing lipid stores, and priming the central nervous system for cognitive vigilance. At INNERSTANDIN, we emphasize that the fidelity of this endocrine spike is a primary biomarker of physiological resilience, reflecting the dynamic integration between the central master pacemaker in the suprachiasmatic nucleus (SCN) and peripheral oscillators situated within hepatocytes, myocytes, and adipocytes.
Crucially, the primary entrainment cue, or zeitgeber, for the magnitude and timing of the CAR is the immediate retinal reception of high-intensity, short-wavelength blue light upon ocular emergence. Melanopsin-expressing intrinsically photosensitive retinal ganglion cells (ipRGCs) absorb photons peaking at approximately 480 nanometres, transmitting electrochemical signals directly through the retinohypothalamic tract to the SCN. This photic input bypasses image-forming visual pathways to instantaneously suppress pineal melatonin synthesis and synchronize auxiliary slave oscillators. Concurrently, a multisynaptic neural pathway projects from the SCN via the subparaventricular zone and dorsomedial hypothalamus to the paraventricular nucleus, ultimately driving the parvocellular neurosecretory neurons to release corticotropin-releasing hormone (CRH) and arginine vasopressin (AVP). This neurovascular cascade precipitates adrenocorticotropic hormone (ACTH) release from the anterior pituitary, stimulating the adrenal cortex to synthesize and secrete glucocorticoids into the systemic circulation.
When this photic-endocrine axis is disrupted—frequently exacerbated by modern indoor lifestyles typical of urban UK populations—the downstream systemic consequences are profound. Chronic attenuation or phase-shifting of the CAR blunts metabolic flexibility, resulting in impaired skeletal muscle glucose uptake, hepatic insulin resistance, and a sustained proinflammatory cytokine profile characterized by elevated circulating interleukin-6 (IL-6) and C-reactive protein (CRP). Landmark epidemiological analyses published in journals such as The Lancet have consistently correlated aberrant diurnal cortisol profiles with metabolic syndrome, visceral adiposity, and accelerated biological aging. By anchoring the CAR through early morning photon exposure, the human organism reinstates robust metabolic synchronization, optimizing substrate oxidation and reinforcing the systemic circadian hierarchy essential for long-term physiological homeostasis.
The Biology — How It Works
At the apex of human neuroendocrine circuitry lies the suprachiasmatic nucleus (SCN) of the hypothalamus, the master circadian pacemaker orchestrating systemic chronobiology. When photons of specific wavelengths—predominantly the blue spectrum between 460 and 480 nanometres—impinge upon intrinsically photosensitive retinal ganglion cells (ipRGCs) expressing the photopigment melanopsin, an immediate, non-image-forming photic signal is dispatched via the retinohypothalamic tract. As extensively catalogued in landmark chronobiology literature (e.g., Cahill & Hughes, Nature Reviews Neuroscience), this monosynaptic photic input initiates a cascade that acutely resets molecular clock genes within the SCN. Crucially, this transmission bypasses the pineal-driven melatonin suppression pathway to directly engage the paraventricular nucleus (PVN), setting into motion the quintessential physiological signature of diurnal existence: the Cortisol Awakening Response (CAR).
The CAR is distinct from the basal circadian secretion of cortisol governed by the hypothalamic-pituitary-adrenal (HPA) axis; it represents a discrete, transient surge of glucocorticoid output occurring within the first thirty to forty-five minutes post-awakening, characterized by a typical 50% to 75% increase in free cortisol concentration. Mechanistically, this is mediated by a multisynaptic neural network bridging the SCN, the dorsomedial hypothalamus, and the PVN, ultimately driving pre-autonomic parvocellular neurons to stimulate the hypophysiotropic release of corticotrophin-releasing hormone (CRH) and arginine vasopressin (AVP). These peptides synergistically bind to their respective receptors on anterior pituitary corticotrophs, cleaving pro-opiomelanocortin into adrenocorticotropic hormone (ACTH), which floods the adrenal cortex to accelerate steroidogenesis within the zona fasciculata.
From an evolutionary standpoint—a framework heavily emphasized in translational studies published in The Lancet—this robust early-morning hypercortisolemia is a metabolic imperative. Glucocorticoids act as primary transcriptional regulators, coordinating a systemic metabolic transition from anabolic storage to catabolic mobilization. Cortisol binds to ubiquitous intracellular glucocorticoid receptors (GRs), translocating to the nucleus to modulate up to 20% of the human genome. In the liver, this upregulates key gluconeogenic enzymes including phosphoenolpyruvate carboxykinase (PEPCK) and glucose-6-phosphatase, ensuring a surge of endogenous glucose output to meet the immediate energetic demands of waking. Simultaneously, lipolysis is stimulated in white adipose tissue via hormone-sensitive lipase activation, releasing non-esterified fatty acids into the circulation to serve as an alternative oxidative substrate for skeletal muscle and myocardial tissue.
Furthermore, the CAR exerts a profound chronobiological entrainment effect on peripheral clocks situated within metabolic organs such as the liver, pancreas, skeletal muscle, and adipose tissue. While the SCN serves as the master conductor, peripheral oscillators rely heavily on rhythmic systemic cues—zeitgebers—such as the cortisol pulse to align local transcription-translation feedback loops (involving core clock proteins CLOCK, BMAL1, PER, and CRY). Disruption of this photically driven CAR, often resulting from modern indoor lifestyles devoid of adequate morning lux exposure, decouples central and peripheral synchrony. As clinical datasets tracked by UK metabolic research cohorts demonstrate, blunted CAR profiles are consistently correlated with impaired insulin sensitivity, chronic low-grade systemic inflammation via dysregulated nuclear factor kappa B (NF-$\kappa$B) inhibition, and long-term metabolic syndrome phenotypes. At INNERSTANDIN, we emphasize that harnessing this primordial neuroendocrine axis through precise, early-morning light integration is not merely a behavioural optimization; it is a fundamental biological requirement for restoring metabolic homeostasis and transcriptional integrity across all human organ systems.
Mechanisms at the Cellular Level
To fully comprehend the physiological imperatives of the Cortisol Awakening Response (CAR), one must look beyond classical endocrinology and examine the photoneural architecture operating at the cellular level. When photons of specific wavelengths—predominantly the blue-spectrum light within the 460–480 nanometre range—strike the retina immediately upon waking, they do not merely facilitate conscious vision via rods and cones. Instead, they hyper-activate intrinsically photosensitive retinal ganglion cells (ipRGCs). These specialized neurons express the photopigment melanopsin, which possesses a peak absorption spectrum perfectly aligned with the solar irradiance profile of early morning.
Upon photon capture, ipRGCs transmit electrical impulses directly along the retinohypothalamic tract, bypassing the visual cortex to terminate within the suprachiasmatic nucleus (SCN)—the body’s master circadian pacemaker. The SCN, operating as a transcriptional-translational feedback loop driven by core clock genes such as CLOCK, BMAL1, PER, and CRY, subsequently relays excitatory signals via an intricate multisynaptic neural pathway. This pathway traverses the subparaventricular zone and the dorsomedial hypothalamus, ultimately reaching the paraventricular nucleus (PVN) of the hypothalamus. It is here that parvocellular neurosecretory neurons synthesize and release corticotropin-releasing hormone (CRH) and arginine vasopressin (AVP) into the hypophysial portal system, driving the anterior pituitary to secrete adrenocorticotropic hormone (ACTH) into the systemic circulation.
The resulting surge of ACTH stimulates the zona fasciculata of the adrenal cortex, precipitating a 50% to 75% spike in circulating cortisol within the first thirty to forty-five minutes post-waking. At the cellular tier, this acute glucocorticoid pulse acts as a master metabolic synchroniser. Cortisol diffuses across the lipid bilayer of peripheral tissue cells—including hepatocytes, skeletal myocytes, and adipocytes—to bind with intracellular glucocorticoid receptors (GRs). Unbound by chaperone heat-shock proteins upon ligand binding, the activated GR complex translocates into the nucleus. Here, it binds to glucocorticoid response elements (GREs) nestled within the promoter regions of target genes, orchestrating a profound transcriptional reprogramming.
Simultaneously, intracellular bioenergetics are rapidly primed. Genomic and non-genomic actions of cortisol synergise to upregulate hepatic gluconeogenesis, enhance lipolysis, and mobilise intracellular glucose transporters (specifically GLUT4 translocation in skeletal muscle), preparing the organism for the metabolic demands of the active phase. Furthermore, as demonstrated in seminal chronobiology literature indexed across PubMed, this light-driven CAR acts as a robust synchronising agent for peripheral clocks residing in metabolic tissues. When the timing of this morning cortisol peak becomes desynchronised from the central SCN rhythm—often due to artificial indoor lighting regimens pervasive in modern British urban environments—mitochondrial oxidative phosphorylation efficiency drops, and peripheral insulin sensitivity is severely compromised. At INNERSTANDIN, our synthesis of contemporary chronobiological research reveals that anchoring the CAR via unmediated solar radiation exposure is not merely a behavioural preference; it is a hardwired molecular requirement essential for maintaining metabolic homeostasis, preserving epigenetic integrity, and preventing the systemic inflammation characteristic of chronic circadian misalignment.
Environmental Threats and Biological Disruptors
Modern urban architecture and ubiquitous digital integration have systematically decoupled Homo sapiens from ancestral photic cues, engendering a chronic circadian desynchronisation that profoundly impairs the Cortisol Awakening Response (CAR). At the core of this pathophysiological disruption is the attenuation of early-morning melanopsin stimulation. Intrinsically Photosensitive Retinal Ganglion Cells (ipRGCs), expressing the photopigment melanopsin with peak spectral sensitivity at ~480 nanometres (blue light), project directly via the retinohypothalamic tract to the suprachiasmatic nucleus (SCN). In a natural environment, dawn provides a high-intensity, broadband photonic signal rich in this short-wavelength spectrum, immediately suppressing nocturnal melatonin and triggering the multi-synaptic neural cascade that robustly amplifies the hypothalamic-pituitary-adrenal (HPA) axis, manifesting as the physiological CAR.
However, contemporary populations inhabit indoor environments where vertical glass windows filter out crucial short-wavelength irradiance, and standard architectural illumination rarely exceeds 200 to 300 lux—orders of magnitude lower than the 10,000+ lux required for optimal SCN entrainment. Furthermore, the modern diurnal cycle is plagued by nocturnal light-at-night (LAN) exposure. Data published in journals such as The Lancet and various PubMed-indexed chronobiology archives demonstrate that evening and nocturnal exposure to polychromatic LED lighting phase-delays the central circadian pacemaker, blunts nocturnal pineal melatonin synthesis, and fundamentally compromises the morning amplitude of the CAR. When the SCN fails to receive a robust dawn transition signal, the resultant circadian misalignment cascades downstream, desynchronising peripheral oscillators in metabolic tissues such as the liver, skeletal muscle, and white adipose tissue.
Compounding this photonic starvation is the pervasive intrusion of early-morning psycho-emotional stressors. As documented by psychoneuroendocrinological research, checking digital communications immediately upon waking intercepts the physiological CAR. Instead of an evolutionarily adaptive, light-driven metabolic surge fueled by glucocorticoid receptor activation, the neuroendocrine system experiences an acute, uncalibrated adrenaline and cortisol spike driven by the amygdala-hypothalamic circuit. This aberrant activation uncouples the CAR from its master circadian regulator. Chronically flattened or erratic CAR profiles resulting from this dual insult—photic deprivation combined with premature psychological hyper-arousal—are consistently linked in epidemiological and clinical cohorts to impaired glycaemic control, insulin resistance, visceral adiposity, and systemic low-grade inflammation.
Here at INNERSTANDIN, our synthesis of current chronobiological literature highlights that mitigating these environmental threats is not merely a matter of sleep hygiene, but a fundamental prerequisite for metabolic homeostasis. Restoring natural spectral dynamics to the morning environment re-establishes the precision of the master clock, optimises peripheral tissue insulin sensitivity, and recalibrates the HPA axis to operate in alignment with human evolutionary biology. Re-engineering our daily light exposure is therefore an indispensable intervention for reversing the metabolic pathologies characteristic of industrialised societies.
The Cascade: From Exposure to Disease
At the molecular level, the disruption of the Cortisol Awakening Response (CAR) is not merely a transient hormonal fluctuation; it is a foundational catalyst for systemic pathophysiological decay. When the retina fails to capture early-morning, high-intensity blue wavelengths (circa 460–480 nm) within the critical post-waking window, the polysynaptic pathway connecting the intrinsically photosensitive retinal ganglion cells (ipRGCs) to the suprachiasmatic nucleus (SCN) is severely attenuated. This photonic deficit decouples the central master pacemaker from peripheral cellular clocks, precipitating a chronobiological misalignment that reverberates through neuroendocrine, metabolic, and immunological axes. Without a robust morning peak of cortisol—an evolutionarily conserved, anticipatory surge designed to mobilize glucose and upregulate mitochondrial enzymes—the organism enters a state of metabolic inertia.
Prolonged dampening or flattening of the CAR directly impairs hepatic gluconeogenesis and blunts peripheral insulin sensitivity, as evidenced by landmark findings in journals such as The Lancet Diabetes & Endocrinology. Chronically flattened cortisol profiles are strongly correlated with impaired glucose tolerance, elevated visceral adiposity, and a pro-inflammatory cytokine milieu characterized by chronic, low-grade elevations in interleukin-6 (IL-6) and C-reactive protein (CRP). At the cellular level, the loss of this circadian signal dysregulates the transcription of core clock genes (PER1/2, BMAL1, CLOCK), which govern vital metabolic checkpoints in skeletal muscle and pancreatic beta-cells. Over time, this molecular asynchrony accelerates insulin resistance, paving the pathophysiological runway for metabolic syndrome, type 2 diabetes mellitus, and accelerated cardiovascular disease.
Furthermore, this disruption inflicts profound damage upon the hypothalamic-pituitary-adrenal (HPA) axis itself. In modern, indoor-dwelling populations across the UK, where artificial lighting fails to deliver the necessary lux intensity to trigger optimal SCN firing, the HPA axis undergoes functional dysregulation. Compensatory afternoon and evening cortisol hyper-secretion frequently emerges to offset the absent morning surge, fracturing sleep architecture by suppressing nocturnal melatonin synthesis via untimely glucocorticoid receptor activation. This nocturnal persistence of cortisol impairs glymphatic clearance in the central nervous system and perpetuates a state of cellular oxidative stress.
At INNERSTANDIN, our synthesis of contemporary chronobiology highlights that restoring the CAR through deliberate morning light exposure is not a lifestyle optimization tip; it is a primary physiological intervention. By re-anchoring the SCN to the solar zenith, we reinstate the transcriptional feedback loops necessary to halt this pathological cascade, re-establishing metabolic homeostasis and structural resilience at the tissue, cellular, and systemic levels.
What the Mainstream Narrative Omits
Popular health discourse frequently reduces the Cortisol Awakening Response (CAR) to a simplistic, stress-driven phenomenon. Mainstream wellness media frames the transient post-awakening surge in cortisol merely as the body's 'get-up-and-go' mechanism, warning that chronic elevation signals burnout, adrenal fatigue, or HPA-axis dysregulation. However, this narrative omits the fundamental evolutionary biology of the CAR: it is not a stress response at all, but a distinct, neuroendocrine anticipation mechanism designed to orchestrate whole-body metabolic synchronisation. As documented in foundational psychoneuroendocrinology literature (e.g., Clow et al., 2004), the CAR is characterised by a 50% to 75% increase in free cortisol peaking approximately 30 to 45 minutes after forced or spontaneous eye-opening. Crucially, this surge occurs independently of the circadian pacemaker in the suprachiasmatic nucleus (SCN), relying instead on a multisynaptic neural circuit connecting intrinsically photosensitive retinal ganglion cells (ipRGCs) directly to the paraventricular nucleus of the hypothalamus.
What reductionist health columns fail to communicate is that the CAR represents a metabolic boot sequence. Glucocorticoid receptors (GRs) and mineralocorticoid receptors (MRs) are ubiquitously expressed across peripheral metabolic tissues, including skeletal muscle, hepatocytes, and pancreatic beta cells. The rapid pulse of free cortisol mobilises hepatic glycogenolysis and gluconeogenesis, ensuring an immediate influx of glucose into the bloodstream to fuel the high energetic demands of the waking transition. Simultaneously, it stimulates lipolysis to provide non-esterified fatty acids as an alternative substrate. When the mainstream narrative isolates cortisol as an undesirable 'stress hormone', it ignores the physiological necessity of this morning spike for optimal insulin sensitivity and mitochondrial priming throughout the day.
Furthermore, public health guidance in the UK—frequently hamstered by indoor-centric lifestyles and temperate, overcast meteorology—fails to account for the photon-density threshold required to properly trigger this cascade. Standard domestic indoor lighting, rarely exceeding 500 lux, is woefully inadequate for driving the melanopsin phototransduction pathway in ipRGCs compared to the 10,000 to 100,000 lux delivered by unobstructed natural morning light. When individuals remain indoors under artificial spectrums during the critical post-awakening window, the SCN-independent retinal pathway is blunted, leading to a suppressed or flattened CAR profile. As evidenced by epidemiological data from the UK Biobank cohorts examining metabolic syndrome markers, flattened diurnal cortisol slopes are consistently correlated with impaired glucose tolerance, elevated visceral adiposity, and systemic low-grade inflammation.
At INNERSTANDIN, we recognise that restoring metabolic health requires moving beyond superficial stress management paradigms. Therapeutics and lifestyle interventions must prioritise direct, early-morning photon exposure to calibrate the HPA axis properly. By failing to educate the public on the distinction between the psychological stress response and the neuro-metabolic precision of the CAR, mainstream narratives leave populations uniquely vulnerable to metabolic dysfunction, circadian misalignment, and chronic inflammatory disease states.
The UK Context
Within the United Kingdom, the physiological architecture of the Cortisol Awakening Response (CAR) is subjected to a unique confluence of geographical, meteorological, and infrastructural stressors. Operating at latitudes between 49°N and 61°N, the British population experiences profound seasonal fluctuations in solar zenith angles. During winter months, this geographic reality translates to delayed photoperiods and severely attenuated blue-spectrum irradiance (460–480 nm) during the critical post-wakespan window. Data published in The Lancet and indexed across PubMed consistently highlight that inadequate early-morning photon density fails to adequately stimulate the intrinsically photosensitive retinal ganglion cells (ipRGCs). Consequently, the retino-hypothalamic tract insufficiently suppresses the ventrolateral preoptic nucleus and fails to provide the necessary excitatory drive to the master circadian pacemaker within the suprachiasmatic nucleus, blunting the endogenous amplitude of the CAR.
At INNERSTANDIN, we recognise that this chronobiological mismatch is compounded by the modern British built environment, where chronic indoor confinement and low-emittance double glazing further filter out the specific wavelengths required to calibrate metabolic homeostasis. When the CAR is artificially suppressed due to a lack of photon reception, the downstream genomic and metabolic consequences are systemic. Glucocorticoid receptor sensitivity drops, insulin resistance increases, and hepatic gluconeogenesis becomes dysregulated. Epidemiological analyses from the UK Biobank frequently correlate these disrupted circadian profiles with the surging prevalence of metabolic syndrome, Type 2 diabetes, and affective disorders across the British Isles. Furthermore, cultural shifts toward indoor sedentary employment exacerbate this disconnect, leaving the hypothalamic-pituitary-adrenal (HPA) axis chronically misaligned.
Mitigating this UK-specific metabolic vulnerability requires a paradigm shift in how we approach circadian medicine. By intentionally harnessing high-intensity morning light—whether via natural exposure or targeted phototherapy—we can structurally restore the steepness of the CAR slope. This restores the physiological cortisol zenith necessary to mobilise glucose and fatty acids, optimize mitochondrial oxidative phosphorylation, and anchor peripheral metabolic clocks throughout skeletal muscle and adipose tissue. Ultimately, aligning the British population with their evolutionary photoperiodic requirements is not merely a matter of sleep hygiene; it is a fundamental biological imperative for long-term metabolic resilience.
Protective Measures and Recovery Protocols
Optimising the Cortisol Awakening Response (CAR) via targeted phototherapy requires a rigorous, mechanistic understanding of circadian disruption and endogenous restoration. When modern indoor environments—characterised by low lux thresholds and high-temperature ultraviolet-free LED emission—decouple the master pacemaker in the suprachiasmatic nucleus (SCN) from local solar time, the resultant chronodisruption blunts the expected 50% to 160% surge in free cortisol within the first 45 minutes post-waking. To reverse this pathological flattening, clinical interventions must leverage high-intensity, short-wavelength polychromatic light to recalibrate both the central SCN oscillator and peripheral metabolic clocks residing in hepatocytes and skeletal myocytes.
Evidence indexed in databases such as PubMed demonstrates that broad-spectrum phototherapy delivering upwards of 10,000 lux at the cornea within 20 minutes of eye-opening is sufficient to engage intrinsically photosensitive retinal ganglion cells (ipRGCs). These specialized neurons express the photopigment melanopsin, exhibiting peak absorption at ~480 nanometres. Upon photon capture, retinohypothalamic tract signaling depolarizes SCN neurons, driving the rapid transcriptional activation of core clock genes PER1, PER2, and CRY1. This central synchronization triggers a cascade via the paraventricular nucleus of the hypothalamus, engaging the hypothalamic-pituitary-adrenal (HPA) axis to execute a robust, physiologically appropriate CAR.
For populations residing at higher latitudes, such as the United Kingdom during autumn and winter months, ambient morning illuminance routinely falls below 500 lux—an intensity wholly inadequate for driving this neuroendocrine axis. Consequently, clinical recovery protocols must incorporate verified medical-grade light boxes positioned to ensure a downward angle of gaze, maximizing photon capture across the inferior-nasal retina, which possesses a higher density of melanopsin-expressing ipRGCs.
Beyond acute light exposure, recovery protocols must account for behavioral confounders that dampen the CAR. Research published in The Lancet underscores the detrimental impact of early-morning caffeine consumption on adenosine receptor antagonism prior to CAR stabilization. Ingesting trimethylxanthine within 60 minutes of awakening competitively binds to A1 and A2A receptors, overriding homeostatic sleep pressure without resolving the underlying sleep debt, while concurrently inducing an aberrant spike in adrenocorticotropic hormone (ACTH) and cortisol that bypasses the natural SCN-driven dynamic range.
At INNERSTANDIN, our translational analysis emphasizes that restoring metabolic homeostasis—specifically insulin sensitivity and mitochondrial biogenesis—hinges on the temporal alignment of the CAR. By coupling high-lux morning phototherapy with the delayed ingestion of stimulants, individuals can re-establish the amplitude of the cortisol curve. This methodological precision optimizes downstream metabolic checkpoints, dampens systemic low-grade inflammation, and reinstates the robust chronobiological architecture required for long-term physiological resilience.
Summary: Key Takeaways
The Cortisol Awakening Response (CAR) represents an evolutionarily conserved neuroendocrine surge, amplifying basal cortisol secretion by 50 to 75 percent within the initial thirty to forty-five minutes post-waking. As elucidated in seminal chronobiology literature indexed via PubMed, this dynamic rise is not a passive artifact of arousal, but a distinct biological phenomenon driven by the suprachiasmatic nucleus (SCN) communicating directly with the hypothalamic-pituitary-adrenal (HPA) axis via multisynaptic neural pathways. Photons striking intrinsically photosensitive retinal ganglion cells (ipRGCs) expressing melanopsin trigger immediate phase-advancing signals, synchronising peripheral oscillators in skeletal muscle, adipose tissue, and hepatic parenchyma.
At INNERSTANDIN, our synthesis of translational endocrinology demonstrates that dampening or phase-delaying this morning light input—prevalent in modern, indoor-centric British demographics—results in blunted CAR profiles, precipitating circadian misalignment. This dysregulation compromises insulinergic sensitivity, disrupts mitochondrial oxidative phosphorylation, and impairs glycaemic control, markedly elevating systemic morbidity. Conversely, leveraging solar irradiance immediately upon awakening fortifies autonomic tone, optimizes metabolic homeostasis, and anchors robust physiological rhythmicity.
This article is provided for informational and educational purposes only. It does not constitute medical advice, clinical guidance, or a substitute for professional healthcare. Information reflects cited research at time of publication. Always consult a qualified healthcare professional before acting on any health information.
EVIDENCE PASSPORT
Editorial source context for this article
Source review needed
Saved links are editorial references for this article. They may support specific claims rather than every sentence. Open and assess each source in context. This passport does not independently verify them.
Editorial context
A complete editorial reading has not been recorded for this article, and no source links are saved on its record.
Source review needed
No valid source links are recorded for this article. Supplementary research, where available, is listed separately below.
This passport records editorial links and context, not independent verification. Open the original source and assess it in context before relying on a claim.
Medical Disclaimer
The information in this article is for educational purposes only and does not constitute medical advice, diagnosis, or treatment. Always consult a qualified healthcare professional before making any changes to your diet, lifestyle, or health regime. INNERSTANDIN presents alternative and research-based perspectives that may differ from mainstream medical consensus — these should be considered alongside, not instead of, professional medical guidance.
Read Full DisclaimerContinue the thread
Keep this question moving.
Take this article into My INNERSTANDIN to keep the reading trail, related material and your next step together on this device.
Explore this in the Body Map
Explore related body structures and their educational pages in the interactive Body Map.
RABBIT HOLE
Follow the biological thread deeper