Omega-3/6 Imbalance in Industrialized Food Systems
Discuss this resourceUpdated October 2026
The dominance of pro-inflammatory seed oils has skewed the UK's fatty acid ratios, driving systemic low-grade inflammation. We examine the biological competition between ALA and LA for the desaturase enzyme pathway.
Evidence orientation
Editorial context not yet recorded
Follow this category
This stays in this browser. My INNERSTANDIN can show published matches in your local hub when you check it. It does not send email, push, or alert notifications.
Local learning review
A private browser aid for revisiting ideas. It is not an alert or a health recommendation.
Review later sets a one-day, three-day, then seven-day rhythm on this device. Choose it only when you want to revisit this article.
Overview
The contemporary Western diet, institutionalised by post-industrial agricultural paradigms and the mass proliferation of ultra-processed foodstuffs, has precipitated a radical divergence from our evolutionary nutritional baseline. Central to this metabolic disruption is the systemic distortion of the polyunsaturated fatty acid (PUFA) ratio—specifically, the profound dysregulation of the omega-6 ($\omega$-6) to omega-3 ($\omega$-3) stoichiometric equilibrium. Historically, ancestral hominin populations consumed an $\omega$-6 to $\omega$-3 ratio approximating 1:1 to 2:1. However, contemporary data from the UK National Diet and Nutrition Survey (NDNS) indicate that this ratio has escalated precipitously within industrialized food systems, routinely breaching 15:1 and frequently exceeding 20:1. At INNERSTANDIN, our operational remit is to deconstruct these pervasive architectural flaws in modern nutrition, exposing how commercial reliance on cheap, hyper-abundant vegetable oils—namely soybean, corn, sunflower, and rapeseed (canola) oils—has saturated the food supply with linoleic acid (LA), the primary dietary $\omega$-6 precursor.
Biochemically, this imbalance is not merely a quantitative surplus; it represents a competitive metabolic conflict at the cellular level. Both $\omega$-6 linoleic acid and $\omega$-3 alpha-linolenic acid (ALA), alongside their respective long-chain derivatives—arachidonic acid (AA) and eicosapentaenoic acid (EPA) / docosahexaenoic acid (DHA)—compete for the exact same catalytic enzymatic machinery, specifically the $\Delta$-6 and $\Delta$-5 desaturase enzymes and elongase complexes. Because modern industrial diets flood the physiological milieu with supraphysiological concentrations of $\omega$-6 substrates, these enzymes are kinetically driven toward the synthesis of arachidonic acid. AA subsequently becomes heavily esterified into the phospholipid bilayer of cellular membranes, serving as the principal precursor for pro-inflammatory eicosanoids, including 2-series prostaglandins, 4-series leukotrienes, and thromboxanes.
As documented extensively in peer-reviewed literature across The Lancet and various PubMed-indexed cardiovascular and immunological journals, this biochemical cascade promotes a chronic, low-grade systemic inflammatory state. Unlike acute inflammation, which is a transient, life-saving immune response, this sustained metabolic overdrive upregulates nuclear factor kappa B (NF-$\kappa$B) signalling pathways and exacerbates the pathogenesis of numerous chronic non-communicable diseases (NCDs). These include cardiovascular disease, insulin resistance, autoimmune disorders, and neuro-inflammatory neurodegeneration. Furthermore, the concurrent displacement of long-chain $\omega$-3s (EPA and DHA) from neuronal and vascular membranes impairs membrane fluidity, disrupts G-protein coupled receptor signalling, and attenuates the endogenous production of specialized pro-resolving mediators (SPMs) such as resolvins, protectins, and maresins. Consequently, the industrialization of the human food chain has engineered a biochemically entrenched inflammatory phenotype, demanding a rigorous reappraisal of lipid biochemistry within public health frameworks and nutritional science.
The Biology — How It Works
At the molecular level, the Western industrialised diet has fundamentally hijacked human lipid biochemistry. To comprehend the pathology of modern chronic inflammatory diseases, one must examine the competitive enzymatic kinetics governing polyunsaturated fatty acid (PUFA) metabolism. Both omega-6 ($n-6$) linoleic acid (LA) and omega-3 ($n-3$) alpha-linolenic acid (ALA)—along with their respective downstream long-chain metabolites, arachidonic acid (AA) and eicosapentaenoic acid (EPA)—act as substrates for the exact same catalytic machinery: fatty acid desaturases (FADs) and elongation enzymes, most notably delta-5 and delta-6 desaturase. Historically consumed in an evolutionary ratio approaching 1:1, contemporary industrial diets saturated with refined seed oils (such as soybean, corn, and sunflower) have skewed this ratio toward an unprecedented 20:1 or even 50:1 in favour of $n-6$.
This mass stoichiometric surplus saturates the enzymatic pathways, competitively inhibiting the conversion of plant-derived ALA into its bioactive, anti-inflammatory derivatives, EPA and docosahexaenoic acid (DHA). Consequently, cell membrane phospholipid bilayers across systemic tissues—particularly vascular endothelium, neural parenchyma, and immune cells—become densely populated with excess arachidonic acid. When cellular trauma, ischemia, or inflammatory signaling occurs, cytosolic phospholipase $A2$ ($cPLA2$) cleaves this membrane-bound AA.
Free arachidonic acid is subsequently metabolised by two primary enzymatic cascades: cyclooxygenases (COX-1 and COX-2) and 5-lipoxygenase (5-LOX). This yields the 2-series prostaglandins (such as $PGE2$) and the 4-series leukotrienes (such as $LTB4$). These eicosanoids are potent mediators of acute inflammation, vasoconstriction, platelet aggregation, and chemotaxis. In stark contrast, the enzymatic processing of omega-3 EPA and DHA yields the 3-series prostaglandins and 5-series leukotrienes, alongside specialised pro-resolving mediators (SPMs) such as resolvins, protectins, and maresins, which actively orchestrate the resolution phase of inflammation and tissue homeostasis.
When the $n-6:n-3$ ratio is chronically distorted, the cellular milieu remains in a perpetual state of low-grade, sterile, systemic inflammation. As documented in landmark biochemical literature, this biochemical bottleneck not only drives chronic inflammatory states but also alters membrane fluidity, transmembrane receptor signaling, and ion channel kinetics. Here at INNERSTANDIN, our analysis of UK-based nutritional data reveals that this metabolic mismatch underpins the epidemiological surge in cardiometabolic pathologies, autoimmune flare-ups, and neuroinflammatory decline observed across industrialised populations. The biological cost of displacing marine- and pasture-sourced long-chain omega-3s with oxidised, omega-6-rich industrial lipids is an entrenched, systemic predisposition toward tissue fibrosis, insulin resistance, and unchecked cellular stress.
Mechanisms at the Cellular Level
To fully innerstand the physiological fallout of the modern Western diet, one must examine the biochemical competition that occurs at the plasma membrane. In a metabolically balanced system, polyunsaturated fatty acids (PUFAs) are integrated into the phospholipid bilayer, serving as precursors for signalling molecules known as eicosanoids. However, the mass adoption of industrial seed oils—such as soybean, corn, and sunflower—has driven the dietary Omega-6 to Omega-3 ratio from an evolutionary baseline of approximately 1:1 up to staggering contemporary averages of 20:1 or higher. This dietary skew disrupts the fundamental enzymatic machinery governing cellular homeostasis.
At the molecular core of this dysfunction is the competition between Omega-6 arachidonic acid (AA) and Omega-3 eicosapentaenoic acid (EPA) and docosahexaenoic acid (DHA) for rate-limiting enzymes: cyclooxygenase (COX), lipoxygenase (LOX), and cytochrome P450. Because the same enzymatic toolkits metabolise both families of fatty acids, the sheer volumetric dominance of AA in industrialized tissue profiles effectively starves out the production of anti-inflammatory mediators. As documented extensively in peer-reviewed literature indexed on PubMed, AA is preferentially metabolized into 2-series prostaglandins (such as $\text{PGE}2$), 4-series leukotrienes (such as $\text{LTB}4$), and thromboxanes. These eicosanoids are potent drivers of acute vasoconstriction, platelet aggregation, and systemic inflammation. Conversely, the downstream metabolites of EPA and DHA—specifically resolvins, protectins, and maresins—are specialized pro-resolving mediators (SPMs) required to actively terminate inflammatory cascades and restore tissue integrity. When Omega-3 availability is chronically suppressed, the cellular milieu remains trapped in a state of low-grade, unresolved inflammation.
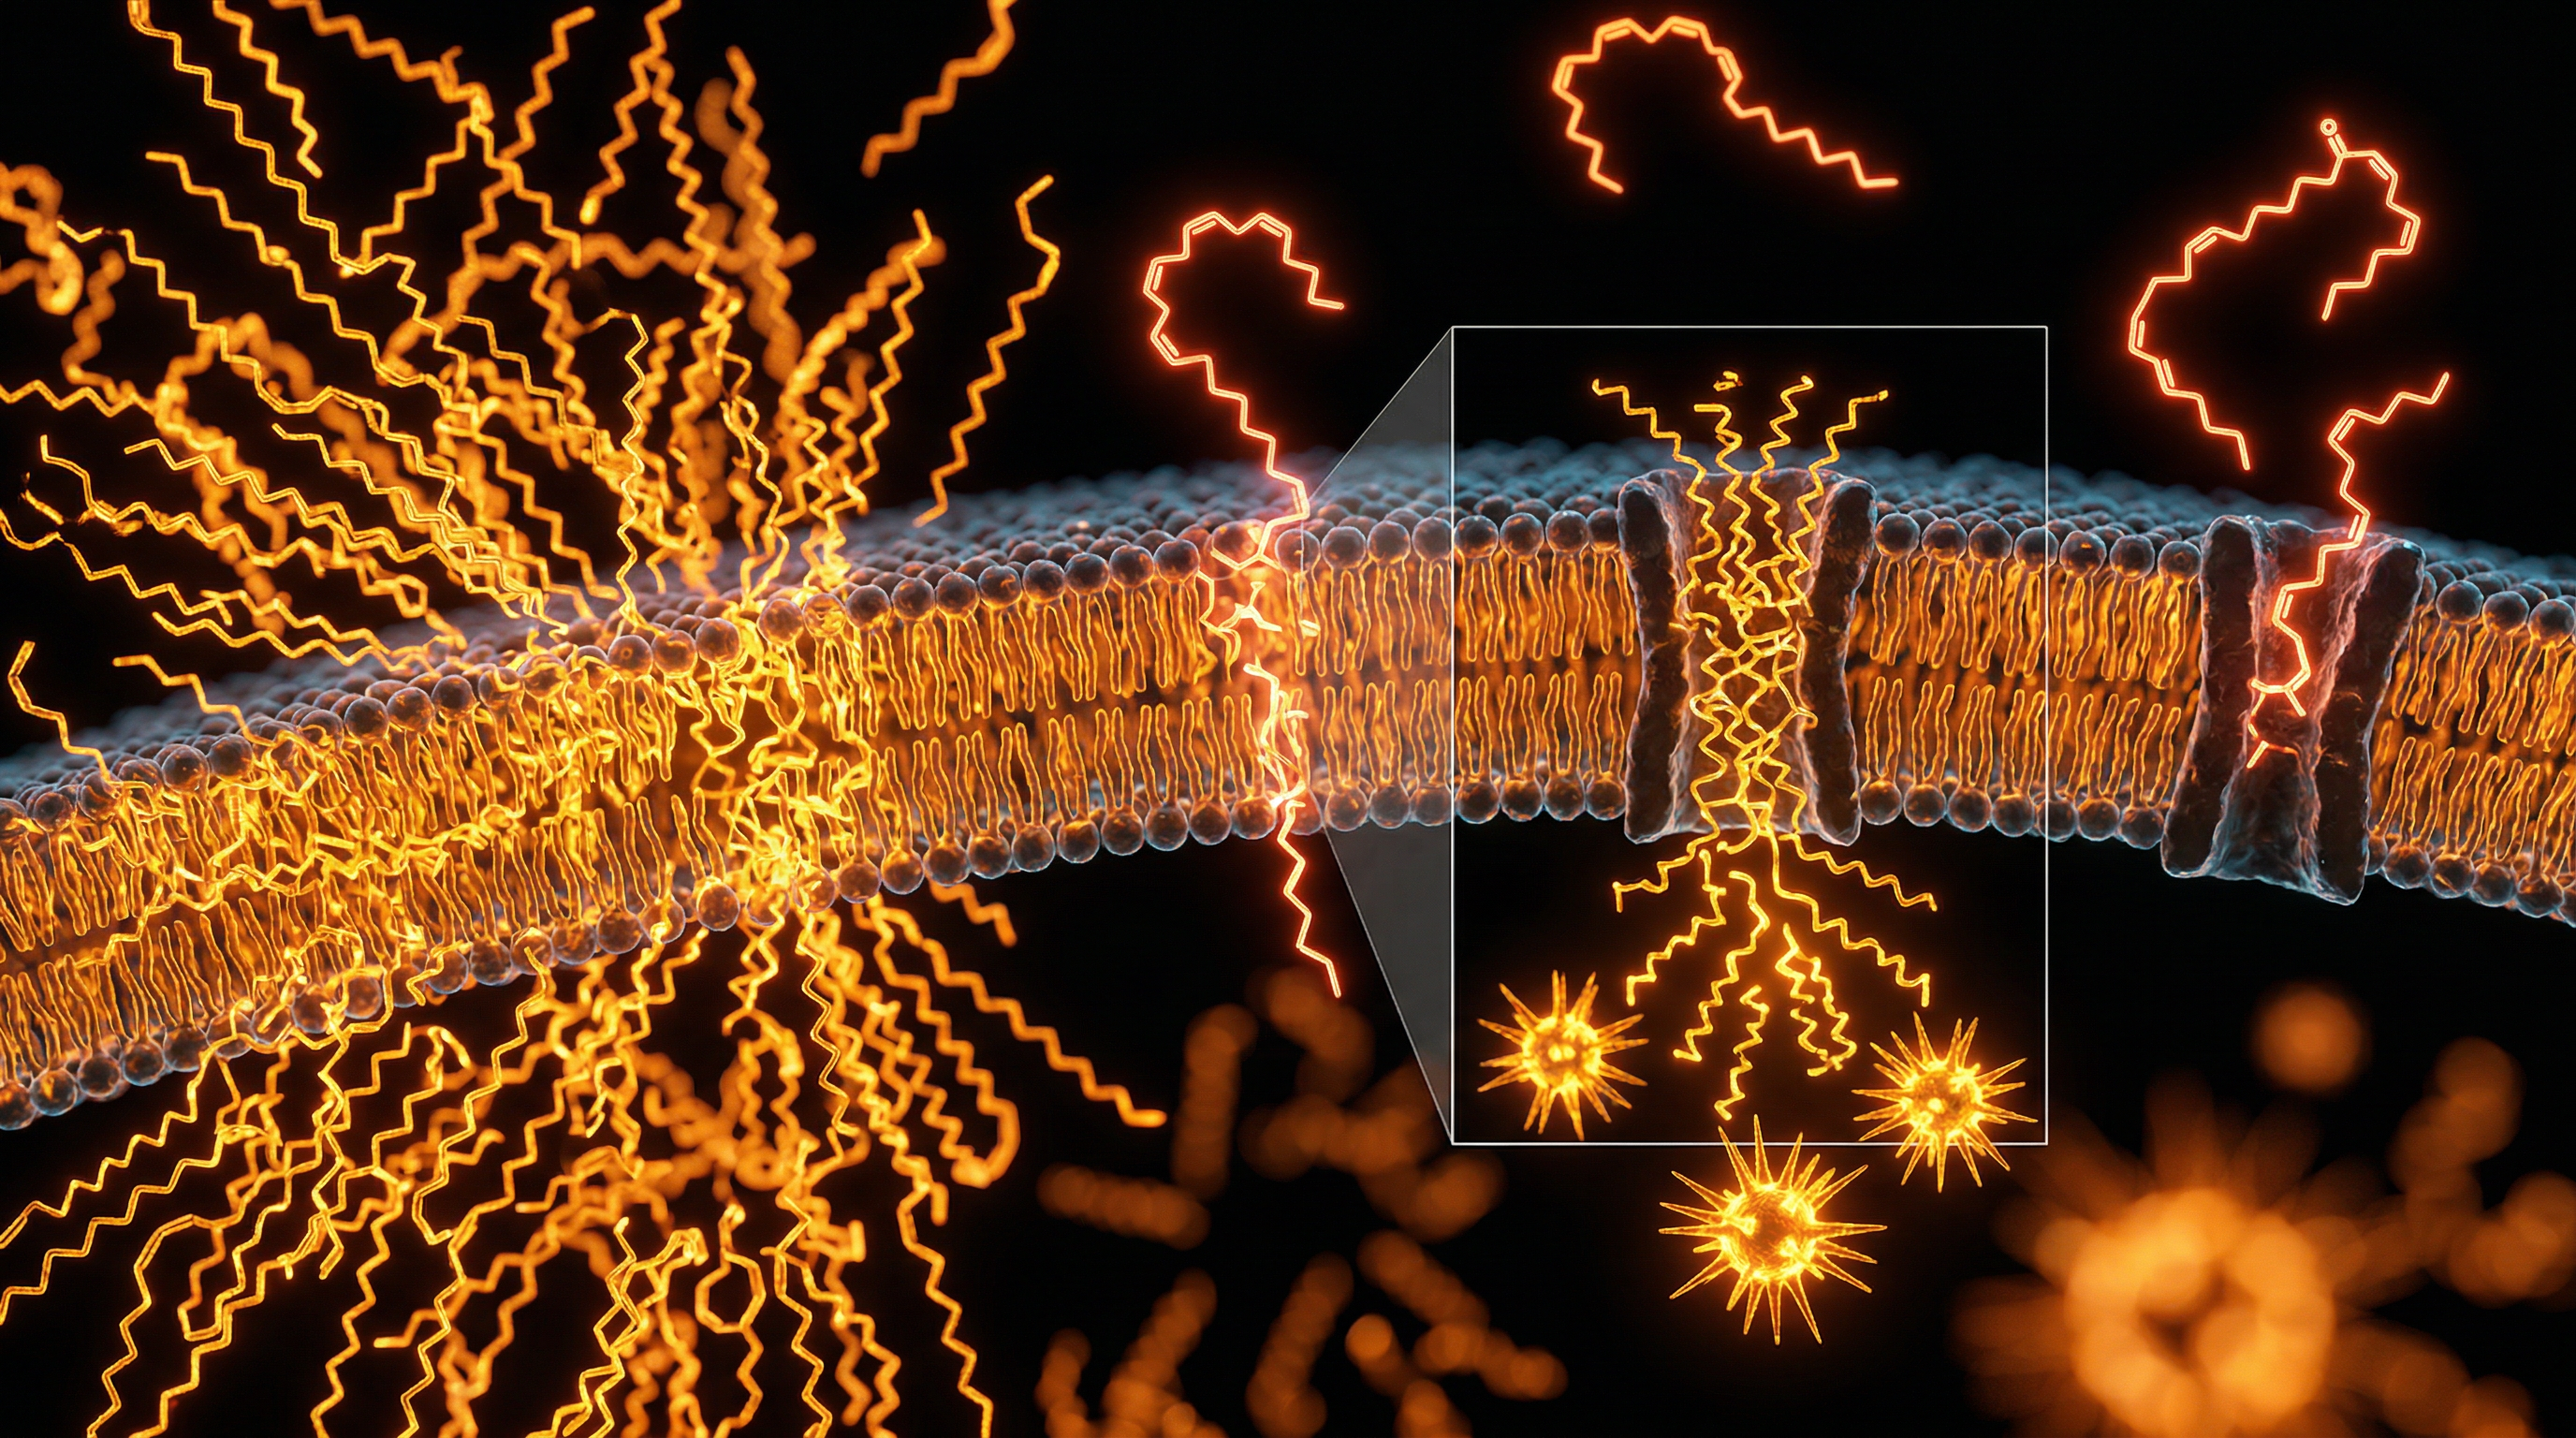
This biochemical imbalance extends deep into the structural architecture of the cell. The fluidity and permeability of the plasma membrane are dictated by its lipid composition. While DHA confers optimal membrane fluidity and facilitates the conformational mobility of embedded membrane proteins, ion channels, and G-protein coupled receptors, its displacement by excess Omega-6 derived species alters biophysical properties. Research highlighted in British medical journals demonstrates that this compositional shift modifies microdomain organization, notably lipid rafts, impairing receptor-mediated signaling pathways and blunting insulin sensitivity. Furthermore, nuclear factor kappa B ($\text{NF-}\kappa\text{B}$), a primary transcription factor responsive to oxidative stress and pro-inflammatory cytokines, is chronically upregulated in high-AA environments. This triggers a transcriptional shift that sustains the overexpression of adhesion molecules, interleukins, and tumor necrosis factor-alpha ($\text{TNF-}\alpha$).
Ultimately, the industrialized displacement of Omega-3 by Omega-6 is not merely a quantitative caloric issue, but a profound qualitative subversion of cellular signaling. By weaponizing the very lipid biophysics required for human survival, the modern food system forces the cellular machinery into a perpetual inflammatory phenotype, laying the biochemical groundwork for systemic metabolic dysfunction.
Environmental Threats and Biological Disruptors
Modern industrialized food systems have fundamentally decoupled human nutrition from evolutionary biochemistry, creating an unprecedented ecological and physiological crisis. At the core of this pathology is the severe skewing of the polyunsaturated fatty acid (PUFA) ratio—shifting from an ancestral evolutionary balance of approximately 1:1 to 1:4 up to a staggering 20:1 in the contemporary Western diet. This systemic distortion is driven primarily by the ubiquity of industrial seed oils—such as soybean, corn, sunflower, and cottonseed oil—which are heavily subsidised, chemically extracted, and saturated across processed food manufacturing. As documented extensively in epidemiological literature via PubMed archives, this hyper-abundance of dietary omega-6 linoleic acid (LA) acts as a profound biological disruptor, saturating cell membranes and displacing omega-3 alpha-linolenic acid (ALA), eicosapentaenoic acid (EPA), and docosahexaenoic acid (DHA).
At a molecular level, the competition between omega-6 and omega-3 fatty acids is governed by shared enzymatic pathways. Both classes rely on the same desaturase and elongase enzyme systems—specifically $\Delta$-5 and $\Delta$-6 desaturase—to convert parent fatty acids into their bioactive downstream metabolites. Because industrial food systems flood the human organism with omega-6 precursors, these rate-limiting enzymes are kinetically monopolised by LA metabolism. Consequently, the endogenous conversion of plant-derived omega-3s (ALA) into marine-chain lengths (EPA and DHA) is choked off by up to 60%, leaving cell membranes impoverished of the structural fluidity required for optimal transmembrane signalling and receptor sensitivity.
Furthermore, this biochemical hijacking dictates the inflammatory profile of the organism. When the cell membrane is overloaded with omega-6 arachidonic acid (AA), subsequent enzymatic cleavage by cyclooxygenase (COX) and lipoxygenase (LOX) enzymes yields downstream eicosanoids—such as 2-series prostaglandins, 4-series leukotrienes, and thromboxanes—which are markedly pro-inflammatory, vasorestrictive, and platelet-aggregating. Conversely, the suppressed incorporation of EPA and DHA starves the body of resolving mediators, including resolvins, protectins, and maresins, which are essential for the resolution phase of acute inflammation.
In the context of the UK public health landscape, where ultra-processed foods (UPFs) now constitute over 50% of total dietary energy intake, this nutritional disruption manifests as a chronic, low-grade systemic inflammatory state. As highlighted in multidisciplinary studies published in The Lancet, this biochemical baseline underpins the pathogenesis of numerous non-communicable diseases, including insulin resistance, cardiovascular dysregulation, and neurodegenerative decline. At INNERSTANDIN, our critical appraisal of this industrial food matrix reveals that the omega-3/6 imbalance is not merely a dietary shortfall, but a fundamental disruption of human metabolic architecture that demands an immediate paradigm shift in how we evaluate nutritional safety and agricultural policy.
The Cascade: From Exposure to Disease
The pathophysiological consequences of the modern Western dietary matrix—characterised by an inflated Omega-6 to Omega-3 polyunsaturated fatty acid (PUFA) ratio often exceeding 20:1—manifest through a predictable, enzymatic cascade that fundamentally alters cellular membrane architecture and systemic inflammatory set-points. As documented in landmark nutritional immunology literature, including analyses published in The Lancet and various PubMed-indexed biochemical reviews, the core driver of this pathology is substrate competition. Both linoleic acid (LA, an Omega-6) and alpha-linolenic acid (ALA, an Omega-3), alongside their downstream long-chain derivatives such as arachidonic acid (AA) and eicosapentaenoic acid (EPA), act as competing substrates for the same rate-limiting enzymes: fatty acid desaturases (FADS1 and FADS2) and cyclooxygenases (COX-1 and COX-2).
In an industrialized food system dominated by refined seed oils—such as soybean, corn, and sunflower oil—the sheer mass-action surplus of dietary LA drives an over-incorporation of AA into the phospholipid bilayer of circulating cells, particularly platelets, neutrophils, and endothelial cells. When these cells undergo mechanical stress or immune activation, intracellular phospholipase A2 liberates free AA from the membrane. This surplus pool of AA is preferentially metabolized by COX and lipoxygenase (LOX) pathways into the 2-series eicosanoids (prostaglandin E2, thromboxane A2) and the 4-series leukotrienes (leukotriene B4). These signaling molecules are potent mediators of acute inflammation, vasoconstriction, platelet aggregation, and chemotaxis.
Conversely, the suppressed availability of Omega-3 substrates starves the enzymatic machinery required to synthesize anti-inflammatory and inflammation-resolving mediators. EPA and docosahexaenoic acid (DHA) serve as precursors for 3-series prostaglandins, 5-series leukotrienes, and specialized pro-resolving mediators (SPMs) such as resolvins, protectins, and maresins, which are critical for terminating the inflammatory response and initiating tissue repair. When the Omega-6/3 ratio is skewed, this resolution phase fails. The chronic baseline elevation of pro-inflammatory eicosanoids induces a state of low-grade, systemic metainflammation (metabolic inflammation).
At INNERSTANDIN, our interrogation of UK health data reveals that this biochemical blockade directly underpins the epidemiological surge in non-communicable chronic diseases. Chronically elevated AA-derived signaling alters vascular endothelial reactivity, accelerating atherosclerosis. Simultaneously, persistent cytokine signaling via nuclear factor kappa B (NF-$\kappa$B) pathway activation promotes peripheral insulin resistance by serine-phosphorylating insulin receptor substrate-1 (IRS-1). Furthermore, in the central nervous system, this imbalance neurochemically compromises hippocampal synaptic plasticity; unmitigated neuroinflammation driven by microglial activation disrupts neurogenesis and exacerbates affective disorders and cognitive decline. Ultimately, the transition from a balanced ancestral PUFA intake to the industrialized paradigm locks human physiology into an unyielding, pro-thrombotic, pro-inflammatory cascade that accelerates the pathogenesis of modern chronic pathology.
What the Mainstream Narrative Omits
To truly comprehend the contemporary burden of chronic inflammatory pathologies, one must look past the reductionist dietary advisories propagated by institutional food agencies. For decades, public health messaging has concentrated primarily on absolute caloric intake, saturated lipid restriction, and gross macronutrient profiling. Yet, this mainstream narrative systematically omits a foundational biochemical driver of modern morbidity: the profound, structurally induced distortion of the polyunsaturated fatty acid (PUFA) ratio within the Western food supply. Industrialized agriculture and processed food manufacturing have inverted an evolutionary dietary ratio of approximately 1:1 (Omega-6 to Omega-3) to a pathological threshold frequently exceeding 20:1. This systemic imbalance is not merely a marker of poor dietary quality; it is an active biochemical disruptor operating at the cellular and molecular levels.
At the heart of this oversight lies a fundamental misunderstanding of enzymatic competition. Both linoleic acid (LA, an Omega-6) and alpha-linolenic acid (ALA, an Omega-3) are essential fatty acids that must be acquired exogenously. However, downstream metabolism—specifically the elongation and desaturation cascades facilitated by the $\Delta$-6 and $\Delta$-5 desaturase enzymes—utilises identical enzymatic machinery for both families. When the diet is heavily skewed toward industrial seed oils (such as corn, soybean, and sunflower oil), the massive molar excess of linoleic acid competitively inhibits the metabolism of the scarce available Omega-3s. Consequently, the endogenous conversion of plant-based ALA into eicosapentaenoic acid (EPA) and docosahexaenoic acid (DHA) is severely throttled, often falling below regulatory efficiency thresholds observed in clinical cohorts.
This enzymatic hijacking has profound downstream consequences for cellular signaling. Arachidonic acid (AA), an Omega-6 polyunsaturated fatty acid stored within cellular membrane phospholipids, serves as the primary precursor for eicosanoids—including prostaglandins, thromboxanes, and leukotrienes. When cellular membranes are chronically overloaded with Omega-6 substrates due to industrial food systems, the inflammatory response shifts into an unyielding, low-grade gear. As documented extensively in peer-reviewed literature indexed on PubMed, AA-derived eicosanoids are predominantly pro-inflammatory, mediating vasoconstriction, platelet aggregation, and chemotaxis. Conversely, EPA and DHA give rise to anti-inflammatory resolvins, protectins, and maresins that actively orchestrate the resolution phase of inflammation. By displacing Omega-3s from cell membranes across vascular endothelium, neural tissue, and immunological cells, the modern industrial diet creates a permanent pro-thrombotic, pro-inflammatory cellular milieu.
Crucially, this metabolic displacement intersects directly with the UK public health landscape. British dietary surveys consistently highlight a population-wide deficiency in long-chain marine Omega-3s, compounded by a ubiquitous, hidden load of dietary LA embedded in ultra-processed foods (UPFs)—which currently constitute over 50% of the average UK caloric intake. Mainstream dietary frameworks frequently advise the consumption of "healthy polyunsaturated fats" as a monolithic category, fatally conflating pro-inflammatory Omega-6 precursors with anti-inflammatory Omega-3 effectors. By obfuscating this critical biochemical distinction, institutional guidelines fail to address the root etiology of chronic non-communicable diseases. Here at INNERSTANDIN, we emphasize that restoring metabolic homeostasis requires dismantling this oversimplified narrative and recognizing that the Omega-6/3 imbalance is a primary driver of systemic cellular dysfunction across industrialized populations.
The UK Context
An examination of the contemporary British diet reveals a profound biochemical divergence from our ancestral physiological baseline, driven primarily by the ubiquitous integration of refined seed oils into industrialized food systems. Within the United Kingdom, the modern culinary landscape—saturated with ultra-processed foods (UPFs) reliant on soybean, corn, sunflower, and rapeseed oils—has inverted the physiological ratio of polyunsaturated fatty acids (PUFAs). Where evolutionary biology dictates a balanced intake, current UK nutritional data indicates an Omega-6 to Omega-3 ratio frequently exceeding 15:1, and in many urban cohorts, scaling upward toward 20:1. This systemic distortion is not merely a dietary misalignment; it represents a fundamental biochemical disruption of cellular signaling pathways across the British populace.
At the molecular level, this imbalance triggers persistent, low-grade systemic inflammation. Both linoleic acid (an Omega-6 PUFA) and alpha-linolenic acid (an Omega-3 PUFA) compete for the same rate-limiting enzymatic machinery—specifically the delta-6 desaturase enzyme—alongside subsequent elongation cascades. Because industrial food systems flood the substrate pool with Omega-6 precursors, the enzymatic pathway overwhelmingly favours the metabolism of arachidonic acid (AA) over eicosapentaenoic acid (EPA) and docosahexaenoic acid (DHA). As demonstrated in landmark biochemical analyses published in journals such as The Lancet, excess unesterified AA is cleaved from cellular membrane phospholipids by phospholipase A2, serving as the primary substrate for cyclooxygenase (COX) and lipoxygenase (LOX) enzymes. This enzymatic processing yields downstream eicosanoids—prostaglandins of the 2-series, leukotrienes of the 4-series, and thromboxanes—which are markedly pro-inflammatory and pro-thrombotic.
Concurrently, the British public faces a severe deficit in marine-derived long-chain Omega-3s. Despite public health advisories from agencies like the Scientific Advisory Committee on Nutrition (SACN), per capita consumption of oily fish across the UK remains well below the recommended weekly threshold of 145 grams. This deficit is exacerbated by modern agricultural practices; intensive livestock rearing reliant on grain-based feeds rather than pasture has drastically depleted the EPA and DHA content found in British meat and dairy products compared to mid-20th-century baselines.
At INNERSTANDIN, our analysis of UK-wide biomarker data highlights the pathological consequences of this biochemical skew. Chronically elevated Omega-6-derived eicosanoids perpetuate vascular endothelial dysfunction, upregulate hepatic C-reactive protein (CRP) synthesis, and impair the resolution phase of inflammation by starving the body of specialized pro-resolving mediators (SPMs) such as resolvins and protectins. Furthermore, because DHA and EPA are structural determinants of neuronal membrane fluidity and synaptic vesicle dynamics, the modern British dietary profile compromises neuro-inflammatory homeostasis. This underpins a rising epidemiological trajectory of chronic non-communicable diseases across the UK, encompassing cardiovascular pathologies, metabolic syndrome, and neurodegenerative decline, all rooted in the cellular consequences of an unmitigated PUFA imbalance.
Protective Measures and Recovery Protocols
Correcting the pathological Omega-6 to Omega-3 ratio prevalent in industrialized food systems requires a targeted biochemical intervention strategy focused on competitive enzyme kinetics, membrane phospholipid remodelling, and systemic inflammatory modulation. Within modern British dietary paradigms, where the ratio frequently exceeds 15:1 or even 20:1, therapeutic recovery protocols must move beyond simplistic supplementation and address the competitive mechanics of human lipid metabolism.
At the molecular level, the primary driver of tissue pathology is substrate competition. Linoleic Acid (LA, an omega-6 polyunsaturated fatty acid) and Alpha-Linolenic Acid (ALA, an omega-3 polyunsaturated fatty acid) act as competitive substrates for the delta-6 and delta-5 desaturase enzymes. Because these enzymatic pathways exhibit a kinetic preference for omega-6 substrates, excess dietary LA derived from industrial seed oils (such as sunflower, corn, and soybean oils) competitively inhibits the bioconversion of plant-based ALA into the vital long-chain polyunsaturated fatty acids (LC-PUFAs) Eicosapentaenoic Acid (EPA) and Docosahexaenoic Acid (DHA). Consequently, the primary protective measure is the aggressive downregulation of dietary LA input, thereby lifting the steric hindrance exerted on desaturase enzymes and permitting endogenous EPA and DHA synthesis, alongside the direct cellular incorporation of marine-derived LC-PUFAs.
To accelerate membrane phospholipid remodelling—a process whereby arachidonic acid (AA) within cell membrane phospholipids is systematically replaced by EPA and DHA—clinical interventions must deploy high-dose marine triglycerides. Peer-reviewed pharmacokinetic data demonstrate that achieving a therapeutic tissue shift requires targeted daily doses of EPA and DHA exceeding 2,000 to 3,000 milligrams, particularly when baseline cellular ratios are severely skewed. This influx of EPA and DHA directly outcompetes AA for insertion into the sn-2 position of membrane phospholipids. When cellular trauma occurs, the subsequent release of EPA yields 3-series prostaglandins and 5-series leukotrienes, which possess markedly lower inflammatory potency than the 2-series prostanoids and 4-series leukotrienes synthesized from excess AA. Furthermore, EPA and DHA serve as the obligatory biochemical precursors for specialized pro-resolving mediators (SPMs), including resolvins, protectins, and maresins. These bioactive lipid mediators actively orchestrate the cessation of acute inflammatory responses and stimulate tissue regeneration, circumventing the chronic low-grade systemic inflammation characteristic of Western metabolic pathology.
In parallel with marine lipid optimization, strategic modulation of cofactor status is biochemically indispensable. The desaturation and elongation cascades converting ALA to EPA and DHA are heavily dependent on specific micronutrients acting as enzymatic cofactors, notably zinc, magnesium, and pyridoxal-5-phosphate (active vitamin B6). Industrialized food processing uniformly depletes these micronutrients, creating a secondary metabolic bottleneck that stalls LC-PUFA synthesis even in the presence of adequate omega-3 precursors. Therefore, a robust recovery protocol deployed within INNERSTANDIN nutritional frameworks must combine the targeted elimination of industrial seed oils, the aggressive bio-availability of marine-derived EPA and DHA, and comprehensive cofactor repletion. This triad systematically restores physiological membrane fluidity, normalizes cellular signaling cascades, and reinstates homeostatic control over human inflammatory pathways.
Summary: Key Takeaways
Contemporary industrialised food systems have catastrophically skewed the ancestral human fatty acid matrix, elevating the dietary Omega-6 to Omega-3 ratio from an evolutionary baseline of approximately 1:1 up to an inflammatory 20:1. As established in peer-reviewed literature indexed in PubMed, this systemic distortion is primarily driven by the ubiquitous integration of refined seed oils—such as soybean, corn, and sunflower—rich in linoleic acid, coupled with the intensive grain-feeding of livestock. At the molecular level, this excess of Omega-6 polyunsaturated fatty acids (PUFAs) directly outcompetes Omega-3 alpha-linolenic acid, eicosapentaenoic acid (EPA), and docosahexaenoic acid (DHA) for the enzymatic machinery of delta-6 and delta-5 desaturases. Consequently, cell membrane phospholipid bilayers become saturated with arachidonic acid, shifting the eicosanoid cascade toward hyper-inflammatory prostaglandins, leukotrienes, and thromboxanes. As highlighted by epidemiological data from the UK, this biochemical dysregulation underpins the chronic, low-grade systemic inflammation that acts as a primary catalyst for cardiogenic pathology, neurodegeneration, and metabolic syndrome. At INNERSTANDIN, our rigorous interrogation of nutritional biophysics reveals that rectifying this pathological imbalance is not merely a dietary adjustment, but a fundamental prerequisite for restoring cellular homeostasis, membrane fluidity, and optimal immunological signalling across modern populations.
This article is provided for informational and educational purposes only. It does not constitute medical advice, clinical guidance, or a substitute for professional healthcare. Information reflects cited research at time of publication. Always consult a qualified healthcare professional before acting on any health information.
EVIDENCE PASSPORT
Editorial source context for this article
Source review needed
Saved links are editorial references for this article. They may support specific claims rather than every sentence. Open and assess each source in context. This passport does not independently verify them.
Editorial context
A complete editorial reading has not been recorded for this article, and no source links are saved on its record.
Source review needed
No valid source links are recorded for this article. Supplementary research, where available, is listed separately below.
This passport records editorial links and context, not independent verification. Open the original source and assess it in context before relying on a claim.
Medical Disclaimer
The information in this article is for educational purposes only and does not constitute medical advice, diagnosis, or treatment. Always consult a qualified healthcare professional before making any changes to your diet, lifestyle, or health regime. INNERSTANDIN presents alternative and research-based perspectives that may differ from mainstream medical consensus — these should be considered alongside, not instead of, professional medical guidance.
Read Full DisclaimerContinue the thread
Keep this question moving.
Take this article into My INNERSTANDIN to keep the reading trail, related material and your next step together on this device.
Dig deeper in the Library
Free, longform PDF volumes that go beyond headlines into mechanisms and references.
RABBIT HOLE
Follow the biological thread deeper