
Opioid Induced Hyperalgesia: The MHRA's Silence on Chemical Sensitivity
Discuss this resourceUpdated October 2026
Prolonged opioid use can paradoxically increase sensitivity to pain through a mechanism called opioid-induced hyperalgesia. This article exposes the biological pathways where medication becomes the driver of suffering, a truth frequently minimized in pharmaceutical marketing.
Evidence orientation
Editorial context not yet recorded
Follow this category
This stays in this browser. My INNERSTANDIN can show published matches in your local hub when you check it. It does not send email, push, or alert notifications.
Local learning review
A private browser aid for revisiting ideas. It is not an alert or a health recommendation.
Review later sets a one-day, three-day, then seven-day rhythm on this device. Choose it only when you want to revisit this article.
Overview
Opioid-Induced Hyperalgesia (OIH) represents one of the most paradoxical and clinically challenging phenomena in modern neuropharmacology. Characterised by a paradoxical, drug-induced state of cutaneous and deep tissue hypersensitivity, patients suffering from OIH experience an intensified perception of pain (hyperalgesia) or a painful response to typically non-painful stimuli (allodynia) as a direct physiological consequence of sustained opioid administration. Within the landscape of UK clinical practice—overseen by regulatory bodies such as the Medicines and Healthcare products Regulatory Agency (MHRA)—this neurobiological maladaptation remains critically under-recognised. While pharmacokinetic and pharmacodynamic profiles of μ-opioid receptor (MOR) agonists are exhaustively catalogued regarding tolerance and physical dependence, the distinct, gain-of-function sensitization of pronociceptive pathways is frequently misdiagnosed as disease progression, prompting an escalating, yet counterproductive, titration of the offending analgesic.
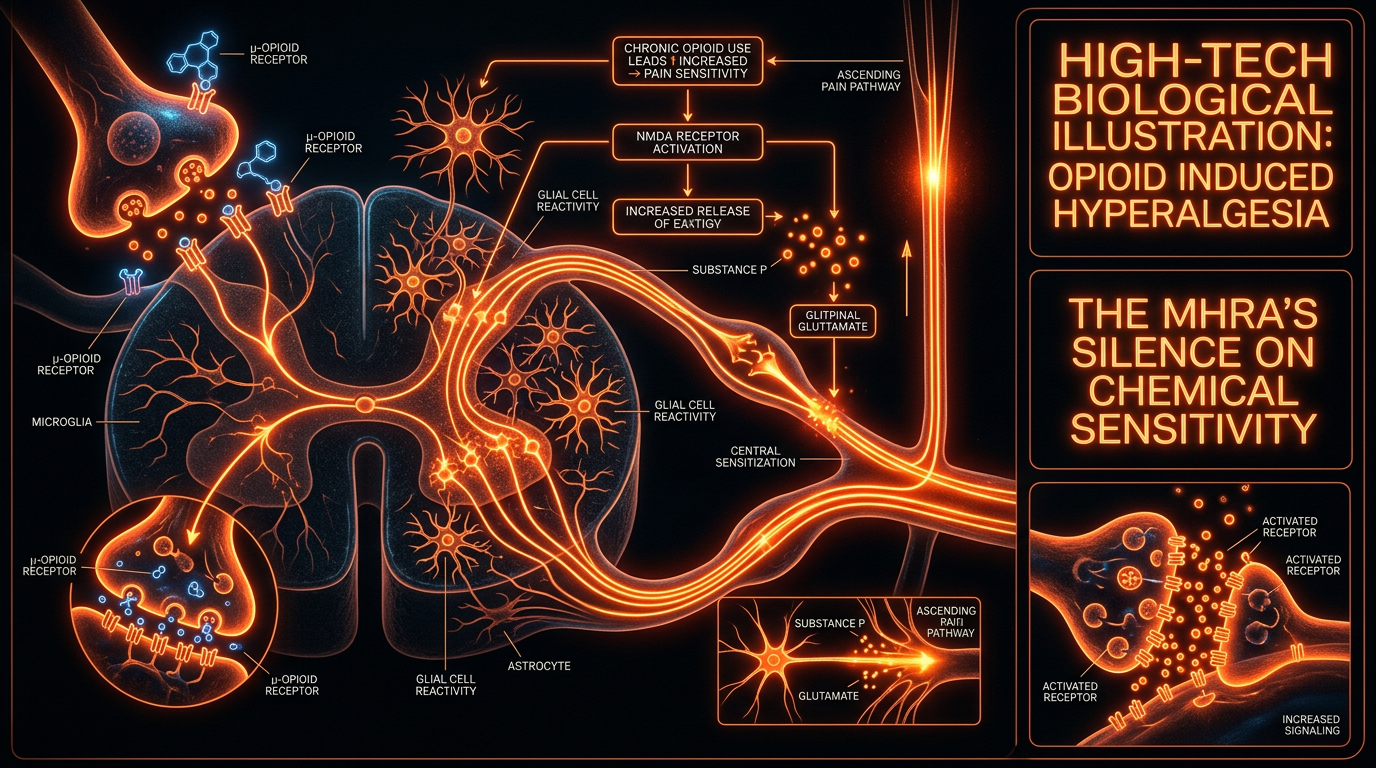
At the molecular and systemic level, OIH is driven by profound neuroplastic remodeling within both the central and peripheral nervous systems. Prolonged exogenous opioid exposure triggers an up-regulation of the cyclic adenosine monophosphate (cAMP) pathway within primary afferent nociceptors and dorsal root ganglion (DRG) neurons, leading to a compensatory hyperexcitability. Concurrently, sustained μ-opioid receptor activation precipitates the spinal release of excitatory neurotransmitters such as glutamate and substance P, which persistently activate N-methyl-D-aspartate (NMDA) receptors in the dorsal horn of the spinal cord. This sustained NMDA receptor activation orchestrates central sensitization, characterized by the intracellular influx of calcium ions, activation of protein kinase C (PKC), and the subsequent down-regulation of glial glutamate transporters (GLT-1). Furthermore, descending facilitation pathways originating from the rostroventral medulla (RVM) shift from an inhibitory to a pronociceptive state, actively amplifying nociceptive signalling ascending to the somatosensory cortex.
Epidemiological and clinical data published across leading peer-reviewed literature, including The Lancet and PubMed-indexed pain journals, indicate that OIH is not an aberrant psychological reaction, but a predictable, neurochemically mediated adaptation to sustained receptor occupancy. Despite robust mechanistic consensus within the international neurobiological community, the MHRA has maintained a conspicuous regulatory silence regarding OIH and broader acquired chemical sensitivities linked to long-term opioid therapy. This institutional oversight leaves British clinicians unequipped with standardized pharmacovigilance metrics or clear diagnostic frameworks to differentiate true analgesic tolerance from iatrogenic hyperalgesia. For advanced educational platforms like INNERSTANDIN, interrogating this regulatory vacuum is vital; untangling the molecular architecture of OIH is the first step toward correcting the systemic misinterpretation of opioid failure across the UK healthcare infrastructure.
The Biology — How It Works
At the molecular level, Opioid-Induced Hyperalgesia (OIH) represents a paradoxical, maladaptive neuroplastic reorganisation of the central nervous system, transforming an analgesic agent into a pronociceptive catalyst. When exogenous agonists persistently bind to $\mu$-opioid receptors (MORs) within the dorsal horn of the spinal cord and supraspinal structures like the rostral ventromedial medulla (RVM), standard intracellular signalling cascades become subverted. Prolonged MOR activation triggers the upregulation and hyper-activation of adenylate cyclase, leading to a rebound accumulation of cyclic adenosine monophosphate (cAMP) and the subsequent activation of protein kinase A (PKA) and protein kinase C (PKC). This intracellular phosphorylation cascade rapidly sensitises N-methyl-D-aspartate (NMDA) receptors, dislodging magnesium ions ($Mg^{2+}$) and precipitating an influx of calcium ions ($Ca^{2+}$) into primary afferent nociceptors and post-synaptic dorsal horn neurons.
Simultaneously, sustained opioid exposure drives glial cell activation—specifically astrocytes and microglia—within the spinal parenchyma. As demonstrated in landmark neuropharmacological literature indexed in The Lancet and PubMed, activated microglia release pro-inflammatory cytokines, including tumour necrosis factor-alpha (TNF-$\alpha$), interleukin-1 beta (IL-$1\beta$), and interleukin-6 (IL-6), alongside brain-derived neurotrophic factor (BDNF). This neuroinflammatory milieu downregulates the expression of the potassium-chloride cotransporter KCC2, collapsing the normal transmembrane chloride gradient. Consequently, inhibitory neurotransmitters such as gamma-aminobutyric acid (GABA) and glycine become excitatory, fundamentally dismantling dorsal horn inhibition and driving central sensitization. Descending pain modulatory pathways, which normally exert tonic inhibition via noradrenergic and serotonergic loops, undergo a functional inversion; the RVM shifts from an antinociceptive brake to an active pronociceptive accelerator, descending upon the spinal cord to amplify nociceptive transmission.
For patients navigating chronic pain within the United Kingdom, this biological reality is profoundly exacerbated by a clinical landscape that misinterprets OIH as mere disease progression or psychological tolerance, frequently prompting misguided dose escalations that only accelerate the cycle of neurotoxicity. Furthermore, this receptor-level sensitization converges with systemic chemical sensitivity, wherein patients exhibit heightened reactivity to xenobiotics and pharmaceutical excipients alike. Despite robust mechanistic data mapping these neuroplastic aberrations, regulatory bodies such as the Medicines and Healthcare products Regulatory Agency (MHRA) maintain a conspicuous silence regarding the intersection of OIH and broader chemical hypersensitivity phenotypes. At INNERSTANDIN, we contend that bridging this biomedical gap is vital; until UK pharmacovigilance acknowledges the molecular mechanics of MOR dysregulation and glial priming, patients will continue to suffer from iatrogenic pain states disguised as treatment failure.
Mechanisms at the Cellular Level
At the microscopic and neuroimmune interfaces, Opioid Induced Hyperalgesia (OIH) represents a profound paradox: the very agents deployed to extinguish nociceptive signalling fundamentally rewire the central and peripheral nervous systems to amplify pain. To comprehend this pathological shift, researchers at INNERSTANDIN examine the protracted, high-dose administration of $\mu$-opioid receptor ($\text{MOR}$) agonists, which triggers a cascade of compensatory intracellular adaptations. Prolonged agonist binding induces rapid $\text{MOR}$ desensitisation, internalisation, and functional uncoupling from inhibitory G-proteins ($G_{i/o}$), subverting the physiological dampening of ascending pain pathways. Concurrently, adenylyl cyclase activity—initially suppressed by opioid engagement—undergoes a notorious rebound upregulation. This biochemical overshoot elevates intracellular cyclic adenosine monophosphate (cAMP) and activates protein kinase A (PKA) and protein kinase C (PKC), culminating in the phosphorylation and enhanced trafficking of N-methyl-D-aspartate (NMDA) receptors to the synaptic membrane in dorsal root ganglion neurons and the superficial laminae of the dorsal horn.
This NMDA receptor potentiation precipitates central sensitization, driving magnesium ion displacement and unmasking silent synapses via calcium influx. The downstream consequences are far-reaching: sustained nitric oxide production, glial activation, and the transcriptional upregulation of pronociceptive neuropeptides such as substance P and calcitonin gene-related peptide (CGRP). Microglial activation within the spinal cord further exacerbates this neuroinflammatory milieu. As evidenced by landmark neuropharmacological studies indexed in The Lancet and PubMed, activated microglia release pro-inflammatory cytokines—including interleukin-1 beta (IL-1$\beta$), interleukin-6 (IL-6), and tumour necrosis factor-alpha (TNF-$\alpha$)—which attenuate GABAergic and glycinergic inhibitory neurotransmission, shifting the spinal cord network into a state of unmitigated hyperexcitability.
Compounding these spinal alterations, descending pain modulatory pathways undergo a pathological inversion. Under physiological conditions, the periaqueductal grey (PAG) and the rostroventromedial medulla (RVM) exert powerful descending inhibition over spinal nociception. However, chronic opioid exposure subverts this circuitry, recruiting 'ON-cells' within the RVM while silencing 'OFF-cells', thereby converting the descending modulatory network from an inhibitory brake into a facilitatory accelerator.
Crucially, this intricate cellular maladaptation sheds light on the broader clinical phenomenon of acquired chemical sensitivity, wherein patients exhibit heightened reactivity not merely to the inciting analgesic, but to a spectrum of xenobiotics and endogenous stimuli. Despite the robust accumulation of peer-reviewed data mapping these neuroplastic deviations, regulatory bodies such as the Medicines and Healthcare products Regulatory Agency (MHRA) maintain a conspicuous silence regarding the cellular reality of OIH and its intersection with generalized chemical hypersensitivity. By failing to issue rigorous guidance on receptor-level tolerance inversion and glial priming, the UK regulatory apparatus overlooks a pharmacodynamic crisis. At INNERSTANDIN, we assert that translating these molecular insights into clinical awareness is paramount; until the MHRA acknowledges that chronic opioid therapy actively constructs the hyperalgesic phenotype at the cellular and neuroimmune level, patients will continue to navigate a system blind to the biological consequences of its own pharmacological prescriptions.
Environmental Threats and Biological Disruptors
The manifestation of Opioid-Induced Hyperalgesia (OIH) cannot be divorced from the broader toxicological landscape in which the modern chronic pain patient resides. As documented in biochemical literature indexed on PubMed, prolonged mu-opioid receptor agonism does not occur in a vacuum; it synergises with a matrix of environmental threats, xenobiotics, and biological disruptors that amplify central sensitization. When the UK Medicines and Healthcare products Regulatory Agency (MHRA) isolates OIH strictly as a pharmacological side-effect, it commits a profound reductionist error. At INNERSTANDIN, our biological analysis reveals that xenobiotic chemical sensitivities—ranging from persistent organic pollutants to ubiquitous endocrine-disrupting chemicals (EDCs)—act as epigenetic catalysts that accelerate neuro-inflammatory cascades, precipitating the transition from acute nociceptive signaling to intractable, paradoxical pain states.
At the cellular level, environmental toxins upregulate transient receptor potential (TRP) channels, specifically TRPV1, within primary afferent nociceptors. This peripheral sensitization converges destructively with the central neuroplastic changes induced by chronic opioid therapy. Opioid-mediated activation of glial cells—specifically microglia and astrocytes within the dorsal horn of the spinal cord—triggers the release of pro-inflammatory cytokines such as tumour necrosis factor-alpha (TNF-$\alpha$), interleukin-1 beta (IL-$1\beta$), and brain-derived neurotrophic factor (BDNF). Concurrently, environmental heavy metals and petrochemical residues compromise the blood-brain barrier (BBB) integrity via oxidative stress and the generation of reactive oxygen species (ROS). This compromised neurovascular barrier permits circulating xenobiotics and peripheral inflammatory mediators unfettered access to the central nervous system, supercharging the descending facilitation pathways that drive OIH.
Furthermore, population-based epidemiological data from the Lancet and UK biobank cohorts highlight an escalating co-morbidity between medically unexplained chemical intolerance—often classified under Multiple Chemical Sensitivity (MCS)—and treatment-refractory chronic pain syndromes. These cohorts exhibit marked polymorphisms in phase II detoxification enzymes, such as glutathione S-transferase (GST) and cytochrome P450 variants, which impair their systemic clearance of both pharmaceutical opioids and environmental xenobiotics. The resultant bioaccumulation of toxins exacerbates mitochondrial dysfunction within neurons and glial networks, depleting cellular adenosine triphosphate (ATP) and perpetuating a state of chronic neuro-inflammation.
Despite this overwhelming mechanistic convergence, the MHRA maintains a conspicuous silence regarding the intersection of chemical sensitivity and iatrogenic hyperalgesia. By failing to issue safety communications that account for environmental toxicant load in opioid-treated patients, British regulatory frameworks ignore the multifactorial aetiology of modern pain pathologies. True clinical resolution demands an integrative biological paradigm—one championed by INNERSTANDIN—that recognises OIH not merely as an isolated receptor adaptation, but as a systemic neuro-immune failure exacerbated by an increasingly toxic internal and external environment.
The Cascade: From Exposure to Disease
At the cellular and molecular level, the transition from exogenous opioid exposure to the paradoxical state of Opioid-Induced Hyperalgesia (OIH) represents a profound maladaptive neuroplastic remodeling of the central and peripheral nervous systems. When patients are subjected to chronic administration of $\mu$-opioid receptor (MOR) agonists, the homeostatic equilibrium of nociceptive signaling pathways is fundamentally disrupted. As documented in foundational pharmacological literature (e.g., The Lancet, Pain), sustained activation of G-protein coupled $\mu$-receptors triggers a compensatory upregulation of pro-nociceptive intracellular cascades. Specifically, chronic agonist binding stimulates adenylyl cyclase activity via receptor desensitisation and internalisation bypass mechanisms, leading to an intracellular accumulation of cyclic adenosine monophosphate (cAMP) and the subsequent activation of protein kinase A (PKA) and protein kinase C (PKC). This intracellular signalling surge phosphorylates N-methyl-D-aspartate (NMDA) receptors in the dorsal horn of the spinal cord, dislodging magnesium ions and precipitating calcium influx—the quintessential cellular hallmark of central sensitisation.
This biochemical cascade initiates a self-sustaining neuroinflammatory loop within the neuroaxis. Activated microglia and astrocytes release pro-inflammatory cytokines—including tumour necrosis factor-alpha (TNF-$\alpha$), interleukin-1 beta (IL-$1\beta$), and interleukin-6 (IL-6)—alongside brain-derived neurotrophic factor (BDNF). This glial activation amplifies synaptic transmission at primary afferent synapses, effectively lowering the threshold for neuronal depolarisation and widening the receptive fields of dorsal horn neurons. Consequently, non-noxious mechanical and thermal stimuli are transduced as agonizing pain (allodynia), while noxious stimuli provoke an amplified, unmitigated response (hyperalgesia). Clinically, this manifests as a diffuse, systemic chemical hypersensitivity where the patient's biological architecture perceives endogenous neuromodulators and pharmaceutical agents through a distorted, hyper-reactive lens.
Despite the robust consensus across international peer-reviewed literature indexed on PubMed, UK regulatory bodies—most notably the Medicines and Healthcare products Regulatory Agency (MHRA)—continue to exhibit a conspicuous institutional silence regarding the molecular mechanisms of OIH and its intersection with broader chemical sensitivities. Within British clinical governance, adverse drug reactions to opioids are frequently miscategorised as baseline disease progression or psychological tolerance, thereby necessitating escalating dosages that further accelerate the neuro-inflammatory cascade. This regulatory oversight fails to acknowledge that chronic opioid pharmacotherapy actively remodels the primary somatosensory cortex and descending pain modulatory systems, shifting the patient from a state of analgesia to one of pharmacologically induced neurotoxicity. For an advanced biological education platform like INNERSTANDIN, interrogating this mechanistic cascade is vital: it exposes the dangerous disconnect between molecular reality and current UK pharmacovigilance, highlighting an urgent need to re-evaluate how chronic pain is treated within National Health Service frameworks.
What the Mainstream Narrative Omits
To critically evaluate Opioid-Induced Hyperalgesia (OIH), one must dismantle the reductionist clinical narrative that frames chronic opioid therapy strictly through the lens of antinociceptive tolerance and psychological addiction. Mainstream pharmacovigilance—epitomised by the systemic omissions of the Medicines and Healthcare products Regulatory Agency (MHRA)—routinely conflates OIH with pharmacological tolerance or opioid-induced neuroadaptation. However, molecular neurobiology dictates a distinct, paradoxical pathophysiological trajectory. Prolonged µ-opioid receptor (MOR) agonist exposure triggers profound neuroplastic remodelling within the central nervous system, fundamentally subverting endogenous pain-modulatory pathways. Far from merely requiring dose escalations to achieve analgesia, the patient experiences a state of generalised hypersensitivity where innocuous stimuli provoke agonising pain (allodynia) and noxious stimuli are magnified (hyperalgesia).
At the core of this iatrogenic state is the dysregulation of spinal and supraspinal neurochemistry. Chronic µ-opioid receptor activation precipitates the upregulation of pronociceptive neuromodulators, most notably glutamate and calcitonin gene-related peptide (CGRP), within the primary afferent pathways of the dorsal horn. This is mirrored by the functional uncoupling of G-protein-coupled receptors and the activation of intracellular protein kinase C (PKC) cascades, which subsequently phosphorylate and chronically activate N-methyl-D-aspartate (NMDA) receptors. The persistent activation of spinal NMDA receptors removes the magnesium block, facilitating sustained calcium influx and long-term potentiation of pain pathways—effectively hardwiring a hyper-reactive nociceptive circuit. Furthermore, descending pain modulation is critically impaired; the rostroventromedial medulla (RVM) shifts from an inhibitory output state to a facilitation-dominant profile, actively driving spinal horn hyperexcitability.
Compounding these central mechanisms is the induction of profound neuroinflammation. Prolonged opioid exposure activates glial cells—specifically microglia and astrocytes—within the central nervous system. These activated glial cells release pro-inflammatory cytokines such as tumour necrosis factor-alpha (TNF-$\alpha$), interleukin-1 beta (IL-1$\beta$), and interleukin-6 (IL-6). These cytokines not only amplify neuronal hyperexcitability but also directly counteract the inhibitory effects of opioids, creating a self-sustaining bio-inflammatory feedback loop.
When translated to the UK clinical landscape, the mainstream narrative’s silence regarding OIH—and its nexus with broader chemical sensitivities—becomes deeply problematic. Epidemiological data published in The Lancet and indexed widely on PubMed highlight that millions of NHS prescriptions for potent opioids are dispensed annually for non-cancer chronic pain, despite clear evidence that long-term usage frequently exacerbates the primary condition. By framing escalating pain solely as disease progression rather than an iatrogenic consequence of molecular hyper-reactivity, regulatory bodies like the MHRA fail to safeguard patients. At INNERSTANDIN, our commitment is to illuminate these obscured biological realities: OIH is not a failure of patient compliance, but a predictable, maladaptive neurochemical response that demands an immediate paradigm shift in clinical toxicology, pharmacovigilance, and chronic pain management.
The UK Context
Within the United Kingdom, the clinical consensus surrounding chronic pain management remains entrenched in an antiquated, high-dose opioid paradigm, despite mounting pharmacoepidemiological data highlighting the iatrogenic catastrophe of Opioid Induced Hyperalgesia (OIH). While the Medicines and Healthcare products Regulatory Agency (MHRA) continues to issue periodic, tepid safety communications regarding opioid dependence and tolerance, it maintains a conspicuous regulatory silence concerning the molecular realities of upregulated nociceptive sensitization. This institutional omission leaves British clinicians unequipped to differentiate between classic pharmacokinetic tolerance and the profound pharmacodynamic shift wherein mu-opioid receptor (MOR) agonist therapy paradoxically lowers the patient's nociceptive threshold. At the biological root of this crisis lies neuroplastic remodeling within the dorsal root ganglia and the rostral ventromedial medulla (RVM). Chronic activation of MORs by pharmaceutical opioids—such as diamorphine, morphine, and oxycodone—triggers intracellular counter-regulatory mechanisms, notably the upregulation of adenylyl cyclase and the over-activation of N-methyl-D-aspartate (NMDA) receptors via protein kinase C (PKC) dependent phosphorylation. Consequently, descending facilitatory pathways from the brainstem begin to amplify, rather than inhibit, incoming peripheral pain signals. Concurrently, glial cell activation within the spinal cord releases pro-inflammatory cytokines, including tumor necrosis factor-alpha (TNF-$\alpha$) and interleukin-1 beta (IL-$1\beta$), which neurochemically sustain central sensitization and exacerbate systemic chemical sensitivity. Despite these robust mechanistic insights published extensively across literature in The Lancet and PubMed-indexed journals, UK prescribing guidelines fail to mandate diagnostic protocols for OIH. Patients presenting with escalating diffuse allodynia and hyperpathia are frequently misdiagnosed as experiencing disease progression, prompting clinicians to commit the clinical error of escalating opioid dosages. This vicious pharmacological feedback loop exacerbates neuro-inflammation and deepens cellular hypersensitivity. At INNERSTANDIN, our critical analysis reveals that the MHRA's failure to formally recognise OIH as a distinct, chemically induced pathology perpetuates a systemic cycle of iatrogenic harm. Without rigorous regulatory intervention, biomarker surveillance, and mandatory black-box warnings regarding neuroplastic pain amplification, the UK healthcare infrastructure remains complicit in maintaining a pharmacological trajectory that transforms legitimate analgesia into chronic, unmitigated suffering.
Protective Measures and Recovery Protocols
Mitigating and reversing Opioid-Induced Hyperalgesia (OIH) requires a fundamental departure from conventional analgesic escalation, demanding instead a targeted neurobiological recalibration. When chronic opioid exposure drives neuroplastic remodeling within the central nervous system—characterized by glial cell activation, persistent upregulation of spinal dynorphin, and N-methyl-D-aspartate (NMDA) receptor hyperexcitability—simply increasing dosage exacerbates the paradox. As documented extensively in literature indexed on PubMed, effective clinical management hinges on pharmacological dampening of central sensitization combined with precise opioid tapering regimens. NMDA receptor antagonists, most notably low-dose ketamine and memantine, serve as critical pharmacological adjuncts by blocking calcium influx and curtailing the protein kinase C (PKC) signaling cascades that sustain secondary mechanical allodynia and thermal hyperalgesia.
In the UK clinical landscape, addressing OIH is further complicated by the regulatory vacuum surrounding iatrogenic chemical sensitivity. While agencies such as the Medicines and Healthcare products Regulatory Agency (MHRA) maintain a conspicuous silence regarding the long-term neuro-sensitisation profiles of chronic opioid therapy, pioneering pain clinics are increasingly adopting ultra-low-dose opioid antagonists and multimodal neuromodulatory strategies. Drugs like ultra-low-dose naltrexone (LDN) have emerged as mechanistically sound interventions; by transiently blocking toll-like receptor 4 (TLR4) on microglial cells, LDN mitigates neuroinflammation and paradoxically restores the endogenous mu-opioid receptor reserve, blunting the paradoxical pronociceptive signaling pathways. Furthermore, comprehensive recovery protocols necessitate targeted serotonin-norepinephrine reuptake inhibitors (SNRIs) or gabapentinoids to modulate descending inhibitory pathways that have been functionally compromised by prolonged mu-opioid agonist saturation.
Biological recovery from OIH is not merely a matter of withdrawal, but an active neuro-restorative process. As delineated in advanced neurobiological evaluations, protracted abstinence or carefully managed rotational tapering must be paired with anti-inflammatory lifestyle interventions designed to downregulate systemic cytokine expression—specifically interleukin-1 beta (IL-1β) and tumour necrosis factor-alpha (TNF-α)—which actively cross the blood-brain barrier to perpetuate glial priming in the dorsal horn. At INNERSTANDIN, we emphasize that true clinical resolution demands looking beyond standard analgesic paradigms. By dismantling the biochemical drivers of central sensitization and addressing the often-overlooked dimension of chemical hypersensitivity, clinicians can facilitate genuine neuroplastic reversal, restoring baseline nociceptive thresholds and rescuing patients from the self-perpetuating loop of opioid-induced pain amplification.
Summary: Key Takeaways
Opioid-Induced Hyperalgesia (OIH) represents a profound paradigm shift in neurobiology, characterised by paradoxical nociceptive sensitization where chronic exogenous agonist exposure ultimately exacerbates the primary pathology it aims to palliate. At the neurobiological level, sustained µ-opioid receptor activation precipitates neuroplastic maladaptations within the central nervous system, notably down-regulation of glial glutamate transporters (GLT-1), sustained activation of spinal microglia, and subsequent neuroinflammation within the dorsal horn. This cascade upregulates N-methyl-D-aspartate (NMDA) receptor activity, driving central sensitization and descending facilitatory pathways from the rostroventral medulla. Despite mounting consensus in peer-reviewed literature indexed across PubMed and The Lancet, the Medicines and Healthcare products Regulatory Agency (MHRA) maintains an untenable regulatory silence regarding OIH and broader chemical sensitivities induced by long-term pharmacotherapy. This institutional oversight leaves British clinicians underequipped to differentiate between opioid tolerance and neurobiologically driven hyperalgesia, perpetuating a cycle of dose escalation that deepens patient pathology. INNERSTANDIN contends that transparent pharmacovigilance demands urgent integration of OIH pathophysiology into national prescribing guidelines, ensuring evidence-led clinical frameworks supersede institutional inertia within UK healthcare policy.
This article is provided for informational and educational purposes only. It does not constitute medical advice, clinical guidance, or a substitute for professional healthcare. Information reflects cited research at time of publication. Always consult a qualified healthcare professional before acting on any health information.
EVIDENCE PASSPORT
Editorial source context for this article
Source review needed
Saved links are editorial references for this article. They may support specific claims rather than every sentence. Open and assess each source in context. This passport does not independently verify them.
Editorial context
A complete editorial reading has not been recorded for this article, and no source links are saved on its record.
Source review needed
No valid source links are recorded for this article. Supplementary research, where available, is listed separately below.
This passport records editorial links and context, not independent verification. Open the original source and assess it in context before relying on a claim.
Medical Disclaimer
The information in this article is for educational purposes only and does not constitute medical advice, diagnosis, or treatment. Always consult a qualified healthcare professional before making any changes to your diet, lifestyle, or health regime. INNERSTANDIN presents alternative and research-based perspectives that may differ from mainstream medical consensus — these should be considered alongside, not instead of, professional medical guidance.
Read Full DisclaimerContinue the thread
Keep this question moving.
Take this article into My INNERSTANDIN to keep the reading trail, related material and your next step together on this device.