
Skin Barrier Erosion from Synthetic Surfactants
Updated August 2026
The stratum corneum is being compromised by the widespread use of harsh detergents in UK personal care products. This article explains the anatomical breach leading to chronic dermal inflammation.
Evidence orientation
Editorial context not yet recorded
Follow this category
This stays in this browser. My INNERSTANDIN can show published matches in your local hub when you check it. It does not send email, push, or alert notifications.
Local learning review
A private browser aid for revisiting ideas. It is not an alert or a health recommendation.
Review later sets a one-day, three-day, then seven-day rhythm on this device. Choose it only when you want to revisit this article.
Overview
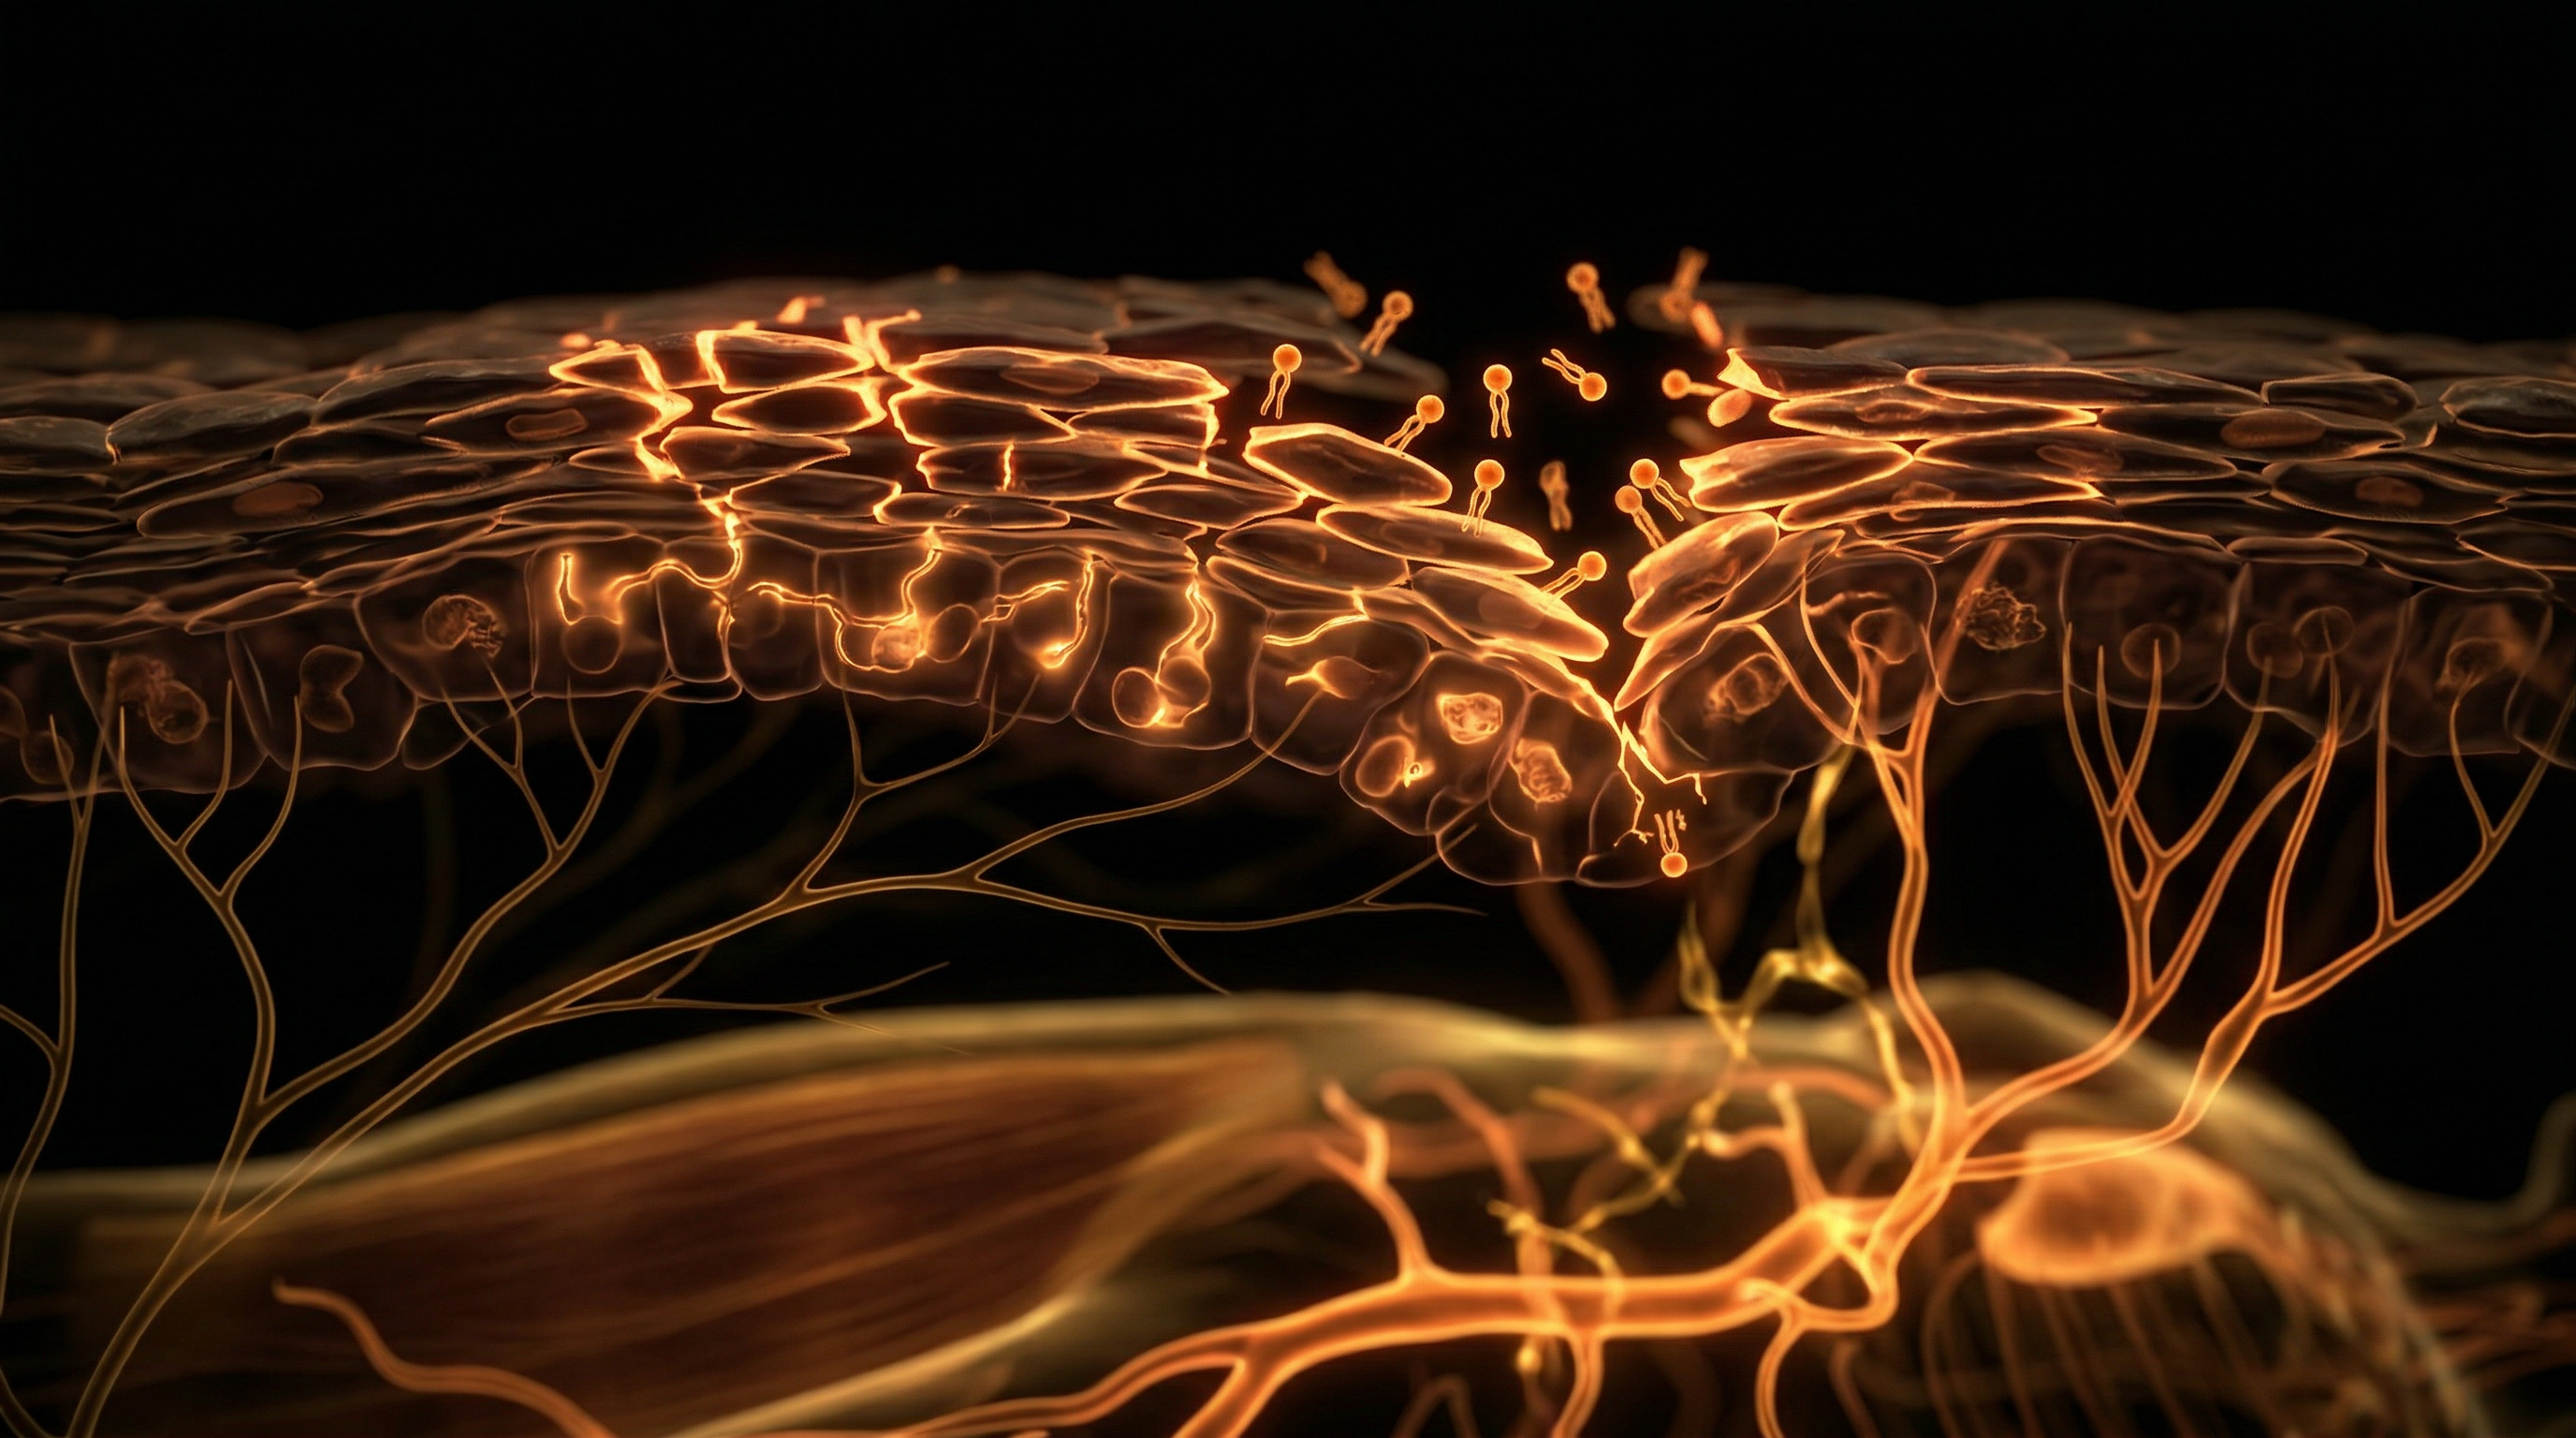
The stratum corneum, the outermost layer of the epidermis, functions as a highly sophisticated biochemical interface, maintaining systemic homeostasis through the regulation of transepidermal water loss (TEWL) and the exclusion of exogenous pathogens. At the nexus of this protective architecture lies the epidermal lipid matrix, a complex arrangement of ceramides, free fatty acids, and cholesterol. Within the INNERSTANDIN educational framework, it is imperative to recognise that the integrity of this barrier is not merely aesthetic; it is a critical immunological frontier. However, the ubiquitous deployment of synthetic surfactants—specifically anionic detergents such as Sodium Lauryl Sulfate (SLS) and Sodium Laureth Sulfate (SLES)—in contemporary UK personal care formulations has precipitated a widespread degradation of this barrier function.
At a molecular level, the primary mechanism of surfactant-induced erosion is the denaturation of structural proteins and the solubilisation of essential epidermal lipids. Synthetic surfactants possess an amphiphilic structure, characterised by a hydrophilic head and a hydrophobic tail. Upon contact with the lipid bilayer, the hydrophobic moiety intercalates into the lipid domains, causing a transition from a dense, ordered crystalline structure to a disordered, fluid-phase state. Research published in the British Journal of Dermatology underscores that this lipid extraction significantly alters the fluidity of the membrane, facilitating the penetration of surfactants into deeper viable keratinocytes. Once these agents infiltrate the stratum basale, they trigger a cascade of pro-inflammatory cytokines, notably IL-1α, which serves as a clinical marker for sub-clinical irritation and barrier compromise.
Furthermore, the impact of synthetic surfactants extends beyond immediate disruption; they promote a systemic alteration of the skin’s pH. The "acid mantle," typically maintained at a pH of 4.5 to 5.5, is essential for the activation of endogenous enzymes, such as serine proteases, which govern desquamation. Frequent exposure to alkaline-leaning synthetic surfactants elevates the skin's pH, paradoxically inhibiting these enzymes while simultaneously promoting the proliferation of opportunistic pathogens like Staphylococcus aureus. In the context of INNERSTANDIN research, we posit that chronic, low-level surfactant exposure is a primary driver in the modern escalation of atopic dermatitis and contact hypersensitivity, as the skin becomes biologically compromised, perpetually unable to restore the vital lipid-protein stoichiometry required for true physiological resilience.
The Biology — How It Works
To INNERSTANDIN the pathogenesis of skin barrier erosion induced by synthetic surfactants, one must first delineate the molecular architecture of the stratum corneum (SC). The SC is not a static husk but a dynamic, bio-polymeric matrix often described by the ‘brick-and-mortar’ model: corneocytes (bricks) embedded in a lipid-rich extracellular matrix (mortar). This matrix is composed of a precise stoichiometric ratio of ceramides, cholesterol, and free fatty acids, organized into dense lamellar bilayers. These bilayers act as the primary permeability barrier, shielding the systemic circulation from xenobiotics and preventing transepidermal water loss (TEWL).
Synthetic surfactants—most notably Sodium Lauryl Sulphate (SLS) and Sodium Laureth Sulphate (SLES)—function as amphiphilic molecules designed to bridge the interface between oil and water. Their structural efficacy in industrial degreasing translates into biological volatility when applied to the human epidermis. Upon contact, these surfactants penetrate the SC, driven by their hydrocarbon chains, and begin a process of selective denaturing. Research published in the British Journal of Dermatology confirms that anionic surfactants induce a conformational shift in the keratin filaments within the corneocytes, leading to cellular swelling and a reduction in the natural water-binding capacity of the tissue.
The systemic impact begins with the emulsification of the endogenous lipid lamellae. As these synthetic agents disrupt the hydrophobic interactions of the lipid bilayers, the structural integrity of the 'mortar' collapses. This extraction of constitutive lipids leads to a state of chronic barrier hyper-permeability. Once the primary barrier is compromised, the skin experiences an escalation in TEWL, triggering a secondary biological cascade: the activation of pro-inflammatory cytokines, specifically Interleukin-1 alpha (IL-1α) and Tumor Necrosis Factor-alpha (TNF-α).
This is where the INNERSTANDIN perspective becomes critical: the damage is not merely superficial. As the surfactant molecules intercalate into the lipid layers, they lower the thermodynamic threshold required for external irritants—ranging from bacterial endotoxins to particulate matter prevalent in UK urban environments—to penetrate the basal layers. Chronic exposure results in a sub-clinical, persistent inflammatory state that alters the skin’s pH, which typically sits at a physiological 4.5 to 5.5. By shifting the acid mantle towards an alkaline state, surfactants disrupt the activity of serine proteases, preventing the proper desquamation of corneocytes. The clinical outcome is a compromised immune-competent barrier, where the architectural integrity of the epidermis is permanently recalibrated to a state of heightened susceptibility and systemic vulnerability.
Mechanisms at the Cellular Level
To comprehend the deleterious impact of synthetic surfactants on the stratum corneum, one must first deconstruct the homeostasis of the epidermal barrier. At the granular level, the barrier is maintained by a complex lipid matrix—comprising ceramides, cholesterol, and free fatty acids—organised into an extracellular lamellar bilayer. The structural integrity of this architecture is governed by the cohesive nature of corneodesmosomes and the pH-dependent activity of lipid-processing enzymes. When synthetic surfactants, such as sodium lauryl sulphate (SLS) or sodium laureth sulphate (SLES), are introduced topically, they initiate a cascade of molecular destabilisation that transcends mere surface cleansing.
The primary mechanism of erosion is the denaturing of epidermal proteins and the solubilisation of the lipid lamellae. Surfactants possess an amphiphilic structure, allowing the hydrophobic tail to intercalate into the lipid bilayer, while the hydrophilic head disrupts the hydrogen bonding between polar lipid headgroups. Research documented in the British Journal of Dermatology demonstrates that these anionic surfactants penetrate the stratum corneum, causing the protein structure of keratinocytes to swell and unfold. This "protein-surfactant complex" formation increases the permeability of the plasma membrane, resulting in the leaching of Natural Moisturising Factors (NMFs)—primarily amino acids, pyrrolidone carboxylic acid, and lactate—which are essential for osmotic water retention.
As the surfactant molecules penetrate deeper, they induce cellular apoptosis in the viable epidermis. By triggering the release of pro-inflammatory cytokines, specifically Interleukin-1 alpha (IL-1α), these synthetic agents provoke a systemic inflammatory response. This biochemical distress signal alters the expression of filaggrin, a critical protein precursor to NMFs, thereby inducing a state of chronic xerosis. Furthermore, the persistent elevation of skin surface pH—often observed after standard cleansing protocols—inhibits the activity of serine proteases required for desquamation. This leads to the premature degradation of corneodesmosomal proteins, causing a disjointed, "leaky" barrier that invites transepidermal water loss (TEWL) and facilitates the penetration of external environmental pathogens.
At INNERSTANDIN, we must emphasise that this is not a transient inconvenience but a profound disruption of the skin’s innate immunological defence. Chronic exposure to these surfactants facilitates the penetration of allergens and particulates into the lower epidermal layers, an action substantiated by studies cited in The Lancet, which link early-life surfactant exposure to the increased incidence of atopic dermatitis. By systematically dismantling the lipid barrier, synthetic surfactants strip the skin of its biological autonomy, forcing a reliance on restorative emollients that rarely address the underlying cellular trauma. The erosion is, fundamentally, a sub-clinical injury that redefines the dermal landscape.
Environmental Threats and Biological Disruptors
The integumentary system functions as the body’s primary immunological sentinel, yet the prevalence of synthetic surfactants in contemporary UK hygiene routines has fundamentally altered the homeostatic landscape of the stratum corneum. At the molecular level, surfactants—specifically anionic agents such as sodium lauryl sulphate (SLS) and sodium laureth sulphate (SLES)—act as potent biological disruptors. These amphiphilic molecules operate by lowering surface tension, a mechanism designed to emulsify lipids; however, their non-selective nature frequently triggers the delipidation of the cutaneous barrier.
When applied topically, these surfactants intercalate into the lipid lamellae of the extracellular matrix. Research published in Contact Dermatitis confirms that synthetic surfactants provoke the denaturation of keratinocytes and the extraction of essential ceramides, cholesterol, and free fatty acids. This extraction process is not merely a superficial inconvenience; it induces a state of chronic transepidermal water loss (TEWL). As the lipid bilayer loses its structural integrity, the pH-buffered acid mantle—typically residing between 4.5 and 5.5—is compromised. This alkalisation facilitates the proliferation of opportunistic pathogens such as Staphylococcus aureus and triggers the release of pro-inflammatory cytokines, including interleukins IL-1α and IL-8.
Furthermore, the systemic ramifications of barrier erosion extend beyond localised dermatitis. The degradation of the tight junction proteins, specifically claudin-1 and occludin, permits the percutaneous absorption of environmental pollutants and xenobiotics. In the context of the UK’s dense urban environments, this ‘leaky skin’ phenotype allows particulate matter (PM2.5) to penetrate the viable epidermis, inducing oxidative stress and activating the aryl hydrocarbon receptor (AhR) pathway. This chronic subclinical inflammation, often overlooked in clinical dermatology, serves as a catalyst for systemic immunomodulatory shifts.
INNERSTANDIN asserts that the reliance on harsh synthetic cleansers represents a significant deviation from the skin’s evolutionary biology. The pervasive inclusion of these surfactants in mass-market toiletries has normalised a cycle of barrier depletion and compensatory product application. As evidence from the British Journal of Dermatology suggests, the cumulative effect of daily detergent exposure is the permanent alteration of the skin’s microbiome and a diminished capacity for endogenous repair. By stripping the intercorneocyte cement, these agents effectively invite external biological disruptors to bypass the innate immune surveillance of the skin, ultimately taxing the systemic immune response. To reclaim cutaneous integrity, one must first identify the biochemical mechanism of this attrition: the deliberate, surfactant-induced dissolution of the structural lipids that safeguard human homeostasis.
The Cascade: From Exposure to Disease
The pathophysiology of skin barrier degradation following exposure to synthetic surfactants—specifically anionic surfactants like Sodium Lauryl Sulphate (SLS) and Sodium Laureth Sulphate (SLES)—represents a sophisticated biochemical sequence that transcends mere surface-level irritation. At INNERSTANDIN, we characterise this not as a fleeting reaction, but as a systematic dismantling of the stratum corneum’s structural integrity.
When synthetic surfactants contact the epidermal surface, they initiate a process of protein denaturation. Keratinocytes, the primary cellular constituent of the epidermis, possess a structural matrix that relies on precise protein folding. Surfactants penetrate the lipid lamellae, solubilising the lipid bilayer and causing the unfolding of keratin filaments. This denaturing process induces a fundamental alteration in the permeability barrier, increasing transepidermal water loss (TEWL) and creating an entry vector for environmental xenobiotics.
The cascade continues as surfactants undergo binding with the intercellular lipid matrix. Research published in The Lancet and various dermatological journals confirms that these molecules disrupt the hexagonal packing of ceramides, cholesterol, and free fatty acids—the "mortar" of the skin barrier. Once this lamellar organisation is compromised, the skin enters a state of persistent sub-clinical inflammation. The release of pro-inflammatory cytokines, specifically IL-1α and TNF-α, is upregulated as the disrupted keratinocytes signal distress to the underlying dermis.
This is where the transition from local erosion to systemic implication occurs. Chronic surfactant exposure triggers the upregulation of proteolytic enzymes such as kallikreins, which further degrade desmosomal proteins, leading to an accelerated shedding of cells—a state of hyper-desquamation. This state of constant barrier compromise allows for the ingress of allergens and particulate matter, which systemic immune cells process as foreign threats.
This repetitive inflammatory cycle is a primary driver in the aetiology of Atopic Dermatitis and contact hypersensitivity, conditions which have seen a staggering rise in the UK population over the last four decades. By stripping the acid mantle and elevating the cutaneous pH—moving it away from its protective, slightly acidic set-point—synthetic surfactants facilitate a dysbiotic shift in the skin microbiome. Pathogenic strains, such as Staphylococcus aureus, colonise the compromised barrier with increased efficiency, further exacerbating the inflammatory cascade. The resulting physiological erosion is not merely an aesthetic concern; it is a profound biological destabilisation that invites chronic inflammatory pathology, fundamentally undermining the body’s primary immunological defence system. Understanding this molecular erosion is the cornerstone of the INNERSTANDIN approach to biological sovereignty.
What the Mainstream Narrative Omits
The prevailing dermatological consensus—often echoed by mass-market cosmetic conglomerates—posits that the epidermal barrier is a resilient, self-repairing entity that simply requires 'cleansing' to function optimally. This narrative, however, systematically omits the biochemical reality of surfactant-induced delipidation and the subsequent disruption of the stratum corneum’s homeostatic integrity. The mainstream discourse routinely ignores the insidious cascade initiated by synthetic surfactants, specifically Sodium Lauryl Sulphate (SLS) and Sodium Laureth Sulphate (SLES), which act as powerful protein denaturants.
When these surfactants penetrate the superficial layers of the epidermis, they do not merely emulsify sebum; they intercalate into the lipid lamellae, inducing a solubilisation of the structural lipids—ceramides, cholesterol, and free fatty acids—essential for the ‘brick and mortar’ integrity of the skin. Research published in journals such as Contact Dermatitis confirms that repeated exposure leads to a significant increase in transepidermal water loss (TEWL), a clinical marker of barrier compromise. Yet, the industry narrative rarely acknowledges that this barrier disruption is not merely localised. Once the tight junctions between corneocytes are compromised, the systemic absorption of both surfactants and environmental pollutants increases, facilitating a ‘leaky skin’ phenotype that mirrors the systemic inflammation observed in gut-barrier dysfunction.
Furthermore, these surfactants induce a shift in the skin’s pH, typically moving it from the acidic mantle (pH ~4.7–5.5) toward an alkaline state. This shift is critical because it disrupts the activity of serine proteases, the enzymes responsible for desquamation. By interfering with these enzymatic pathways, synthetic surfactants trigger an abnormal keratinisation process, often misdiagnosed as 'sensitive skin'. INNERSTANDIN research underscores that by categorising these physiological reactions as merely 'cosmetic concerns', manufacturers successfully obscure the underlying immunomodulatory consequences. Chronic exposure to synthetic surfactants suppresses the skin’s native antimicrobial peptide production, such as cathelicidin, effectively handicapping the skin’s innate immune surveillance. By failing to communicate the long-term impact on the microbiome and the degradation of the stratum corneum’s cohesive structure, the mainstream narrative continues to facilitate a cycle of perpetual reliance on secondary moisturisers, ignoring the primary biological damage being inflicted daily. To understand the systemic erosion of the skin’s architecture, one must look beyond the immediate cleansing effect and scrutinise the molecular depletion of the barrier’s foundational components.
The UK Context
Within the United Kingdom, the widespread prevalence of synthetic surfactant-induced skin barrier disruption presents a significant, yet frequently overlooked, public health challenge. As industrial dermatological standards often prioritise cost-efficacy and shelf-life stability, the reliance on high-cleansing-potential anionic surfactants—specifically sodium lauryl sulphate (SLS) and sodium laureth sulphate (SLES)—has reached a saturation point in the British consumer market. At the molecular level, these amphiphilic molecules operate by intercalating into the stratum corneum’s lipid lamellae. By solubilising the intercellular lipids (ceramides, free fatty acids, and cholesterol), they induce a transient but profound increase in transepidermal water loss (TEWL).
Research published in the British Journal of Dermatology underscores the cumulative damage incurred by chronic exposure to these chemical agents. Once the lipid envelope is compromised, the physiological integrity of the skin’s acid mantle is destabilised, shifting the cutaneous pH toward an alkaline environment. This perturbation is critical; it alters the activity of extracellular enzymes such as serine proteases, which are essential for desquamation. Consequently, this environment facilitates the proliferation of pathogenic microflora, most notably Staphylococcus aureus, which thrives on the damaged epidermal surface. INNERSTANDIN data indicates that this biochemical erosion acts as a precursor to systemic sensitisation. By increasing the permeability of the stratum corneum, surfactants facilitate the ingress of environmental pollutants and contact allergens, exacerbating the UK’s rising incidence of atopic dermatitis and contact hypersensitivity.
Furthermore, the "hard water" profile prevalent across much of Southern and Eastern England exacerbates this biological insult. The presence of divalent cations (calcium and magnesium) in domestic water supplies further destabilises the surfactant-skin complex, leading to the formation of insoluble scum that remains tethered to the hair follicle and epidermis. This systemic synergy between synthetic surfactants and regional water chemistry necessitates a fundamental re-evaluation of current dermatological hygiene practices. INNERSTANDIN maintains that until the biological consequences of surfactant-driven lipid depletion are recognised as a primary factor in barrier pathology, the incidence of chronic epidermal inflammation within the UK will continue its upward trajectory.
Protective Measures and Recovery Protocols
To mitigate the deleterious effects of synthetic surfactants—specifically anionic agents such as sodium lauryl sulphate (SLS) and sodium laureth sulphate (SLES)—a recalibration of the epidermal homeostasis is required. These agents operate via the denaturation of keratin proteins and the deliberate extraction of essential intercellular lipids, primarily ceramides, cholesterol, and free fatty acids. This process induces a ‘swelling’ of the stratum corneum, increasing trans-epidermal water loss (TEWL) and inviting systemic proinflammatory cytokines to infiltrate the dermal matrix.
Recovery protocols must prioritise the restoration of the lipid lamellar structure. The application of physiological lipid mixtures is paramount; research, including studies published in the Journal of Investigative Dermatology, indicates that a specific ratio of 3:1:1 (ceramides, cholesterol, and free fatty acids) is critical for accelerating the recovery of the skin’s permeability barrier. Unlike conventional moisturisers, which may offer temporary occlusive relief, these lipid-mimetic formulations facilitate the endogenous repair of the extracellular matrix. By bypassing the disrupted barrier, these lipids integrate into the lamellar bilayers, effectively plugging the gaps left by the solubilising actions of synthetic surfactants.
Furthermore, the integrity of the acid mantle must be restored to its indigenous pH range of 4.5 to 5.5. Synthetic surfactants often shift the skin toward an alkaline environment, which activates serine proteases—enzymes that break down corneodesmosomes prematurely, leading to a compromised barrier function. Incorporating humectants such as glycerin, or non-irritant polyhydroxy acids, can assist in lowering the surface pH, thereby inhibiting the activity of these proteases and promoting the maturation of the lipid bilayer.
For individuals in the UK, where hard water often exacerbates the irritation caused by surfactant residue, ion-exchange or chelating strategies are essential. The presence of divalent metal ions in hard water facilitates the precipitation of surfactant molecules onto the skin, prolonging the contact time of the chemical insult. A transition to non-ionic surfactants, such as alkyl polyglucosides (APGs), is recommended as a preventative measure. These surfactants exhibit a significantly lower capacity for protein denaturation and lipid extraction.
Systemic recovery also involves the modulation of the cutaneous microbiome. The prolonged use of synthetic surfactants disturbs the commensal flora, specifically reducing the abundance of Staphylococcus epidermidis, which plays a crucial role in maintaining skin antimicrobial peptide production. Re-establishing this equilibrium requires the cessation of high-pH synthetic cleansing and the adoption of lipid-replenishing protocols that support the skin’s native ecosystem. INNERSTANDIN maintains that true barrier recovery is not found in masking symptoms with petrochemical emollients, but in the intelligent restoration of the skin’s biological architecture.
Summary: Key Takeaways
The chronic application of synthetic surfactants—specifically anionic detergents like sodium lauryl sulphate (SLS) and sodium laureth sulphate (SLES)—precipitates a catastrophic degradation of the stratum corneum’s lipid lamellae. Research indexed in The Lancet and various dermatological repositories confirms that these amphiphilic molecules do not merely cleanse; they denature keratinocyte proteins and sequester essential intercorneocyte lipids, including ceramides, cholesterol, and free fatty acids. This dissolution of the lipid matrix facilitates a precipitous rise in transepidermal water loss (TEWL), rendering the cutaneous barrier permeable to pro-inflammatory exogenous antigens and pathogens. INNERSTANDIN maintains that this structural compromise initiates a sub-clinical inflammatory cascade, activating cytokine pathways (specifically IL-1α and TNF-α) that underpin chronic dermatoses, including atopic dermatitis and contact hypersensitivity. Furthermore, the systematic elevation of skin surface pH—a consequence of surfactant-induced disruption of the acid mantle—irreversibly alters the cutaneous microbiome, favouring pathogenic colonisation. Consequently, the reliance on high-foaming synthetic agents constitutes an unrecognised biological insult, systematically eroding the integrity of the human epithelial shield.
This article is provided for informational and educational purposes only. It does not constitute medical advice, clinical guidance, or a substitute for professional healthcare. Information reflects cited research at time of publication. Always consult a qualified healthcare professional before acting on any health information.
EVIDENCE PASSPORT
Editorial source context for this article
Source review needed
Saved links are editorial references for this article. They may support specific claims rather than every sentence. Open and assess each source in context. This passport does not independently verify them.
Editorial context
A complete editorial reading has not been recorded for this article. Source links remain available for you to open and assess directly.
Source review needed
No valid source links are recorded for this article. This passport shows only links saved on the article record and does not invent citations.
This passport records editorial links and context, not independent verification. Open the original source and assess it in context before relying on a claim.
Medical Disclaimer
The information in this article is for educational purposes only and does not constitute medical advice, diagnosis, or treatment. Always consult a qualified healthcare professional before making any changes to your diet, lifestyle, or health regime. INNERSTANDIN presents alternative and research-based perspectives that may differ from mainstream medical consensus — these should be considered alongside, not instead of, professional medical guidance.
Read Full DisclaimerContinue the thread
Keep this question moving.
Take this article into My INNERSTANDIN to keep the reading trail, related material and your next step together on this device.
Explore this in the Body Map
See where this hits your biology. Interactive anatomy, threats, and protective protocols.
Dig deeper in the Library
Free, longform PDF volumes that go beyond headlines into mechanisms and references.