
Heavy Metal Chelation and Neural Waste Management
Discuss this resourceUpdated October 2026
Environmental exposure to lead and mercury in older UK infrastructure contributes to neural heavy metal loading. Optimizing glymphatic flow is necessary to mobilize and export these neurotoxins from the brain.
Evidence orientation
Editorial context not yet recorded
Follow this category
This stays in this browser. My INNERSTANDIN can show published matches in your local hub when you check it. It does not send email, push, or alert notifications.
Local learning review
A private browser aid for revisiting ideas. It is not an alert or a health recommendation.
Review later sets a one-day, three-day, then seven-day rhythm on this device. Choose it only when you want to revisit this article.
Overview
The human central nervous system operates as an exceptionally metabolically active landscape, generating a continuous flux of neurotoxic metabolic byproducts, including amyloid-beta oligomers, hyperphosphorylated tau proteins, and reactive oxygen species. To maintain homeostatic equilibrium, the brain relies heavily on the glymphatic system—a macroscopic perivascular clearance pathway driven primarily by astrocytic aquaporin-4 (AQP4) water channels. Recent neurobiological investigations catalogued in The Lancet Neurology and peer-reviewed PubMed repositories demonstrate that the efficacy of this waste-clearance apparatus is intimately modulated by the presence of bioaccumulated xenobiotic heavy metals, notably lead, mercury, cadmium, and inorganic aluminium. When these toxic transition elements cross the blood-brain barrier via molecular mimicry and ionic substitution, they precipitate profound structural alterations in the neurovascular unit, inducing chronic neuroinflammation and crippling the convective fluid flux necessary for optimal neural waste management.
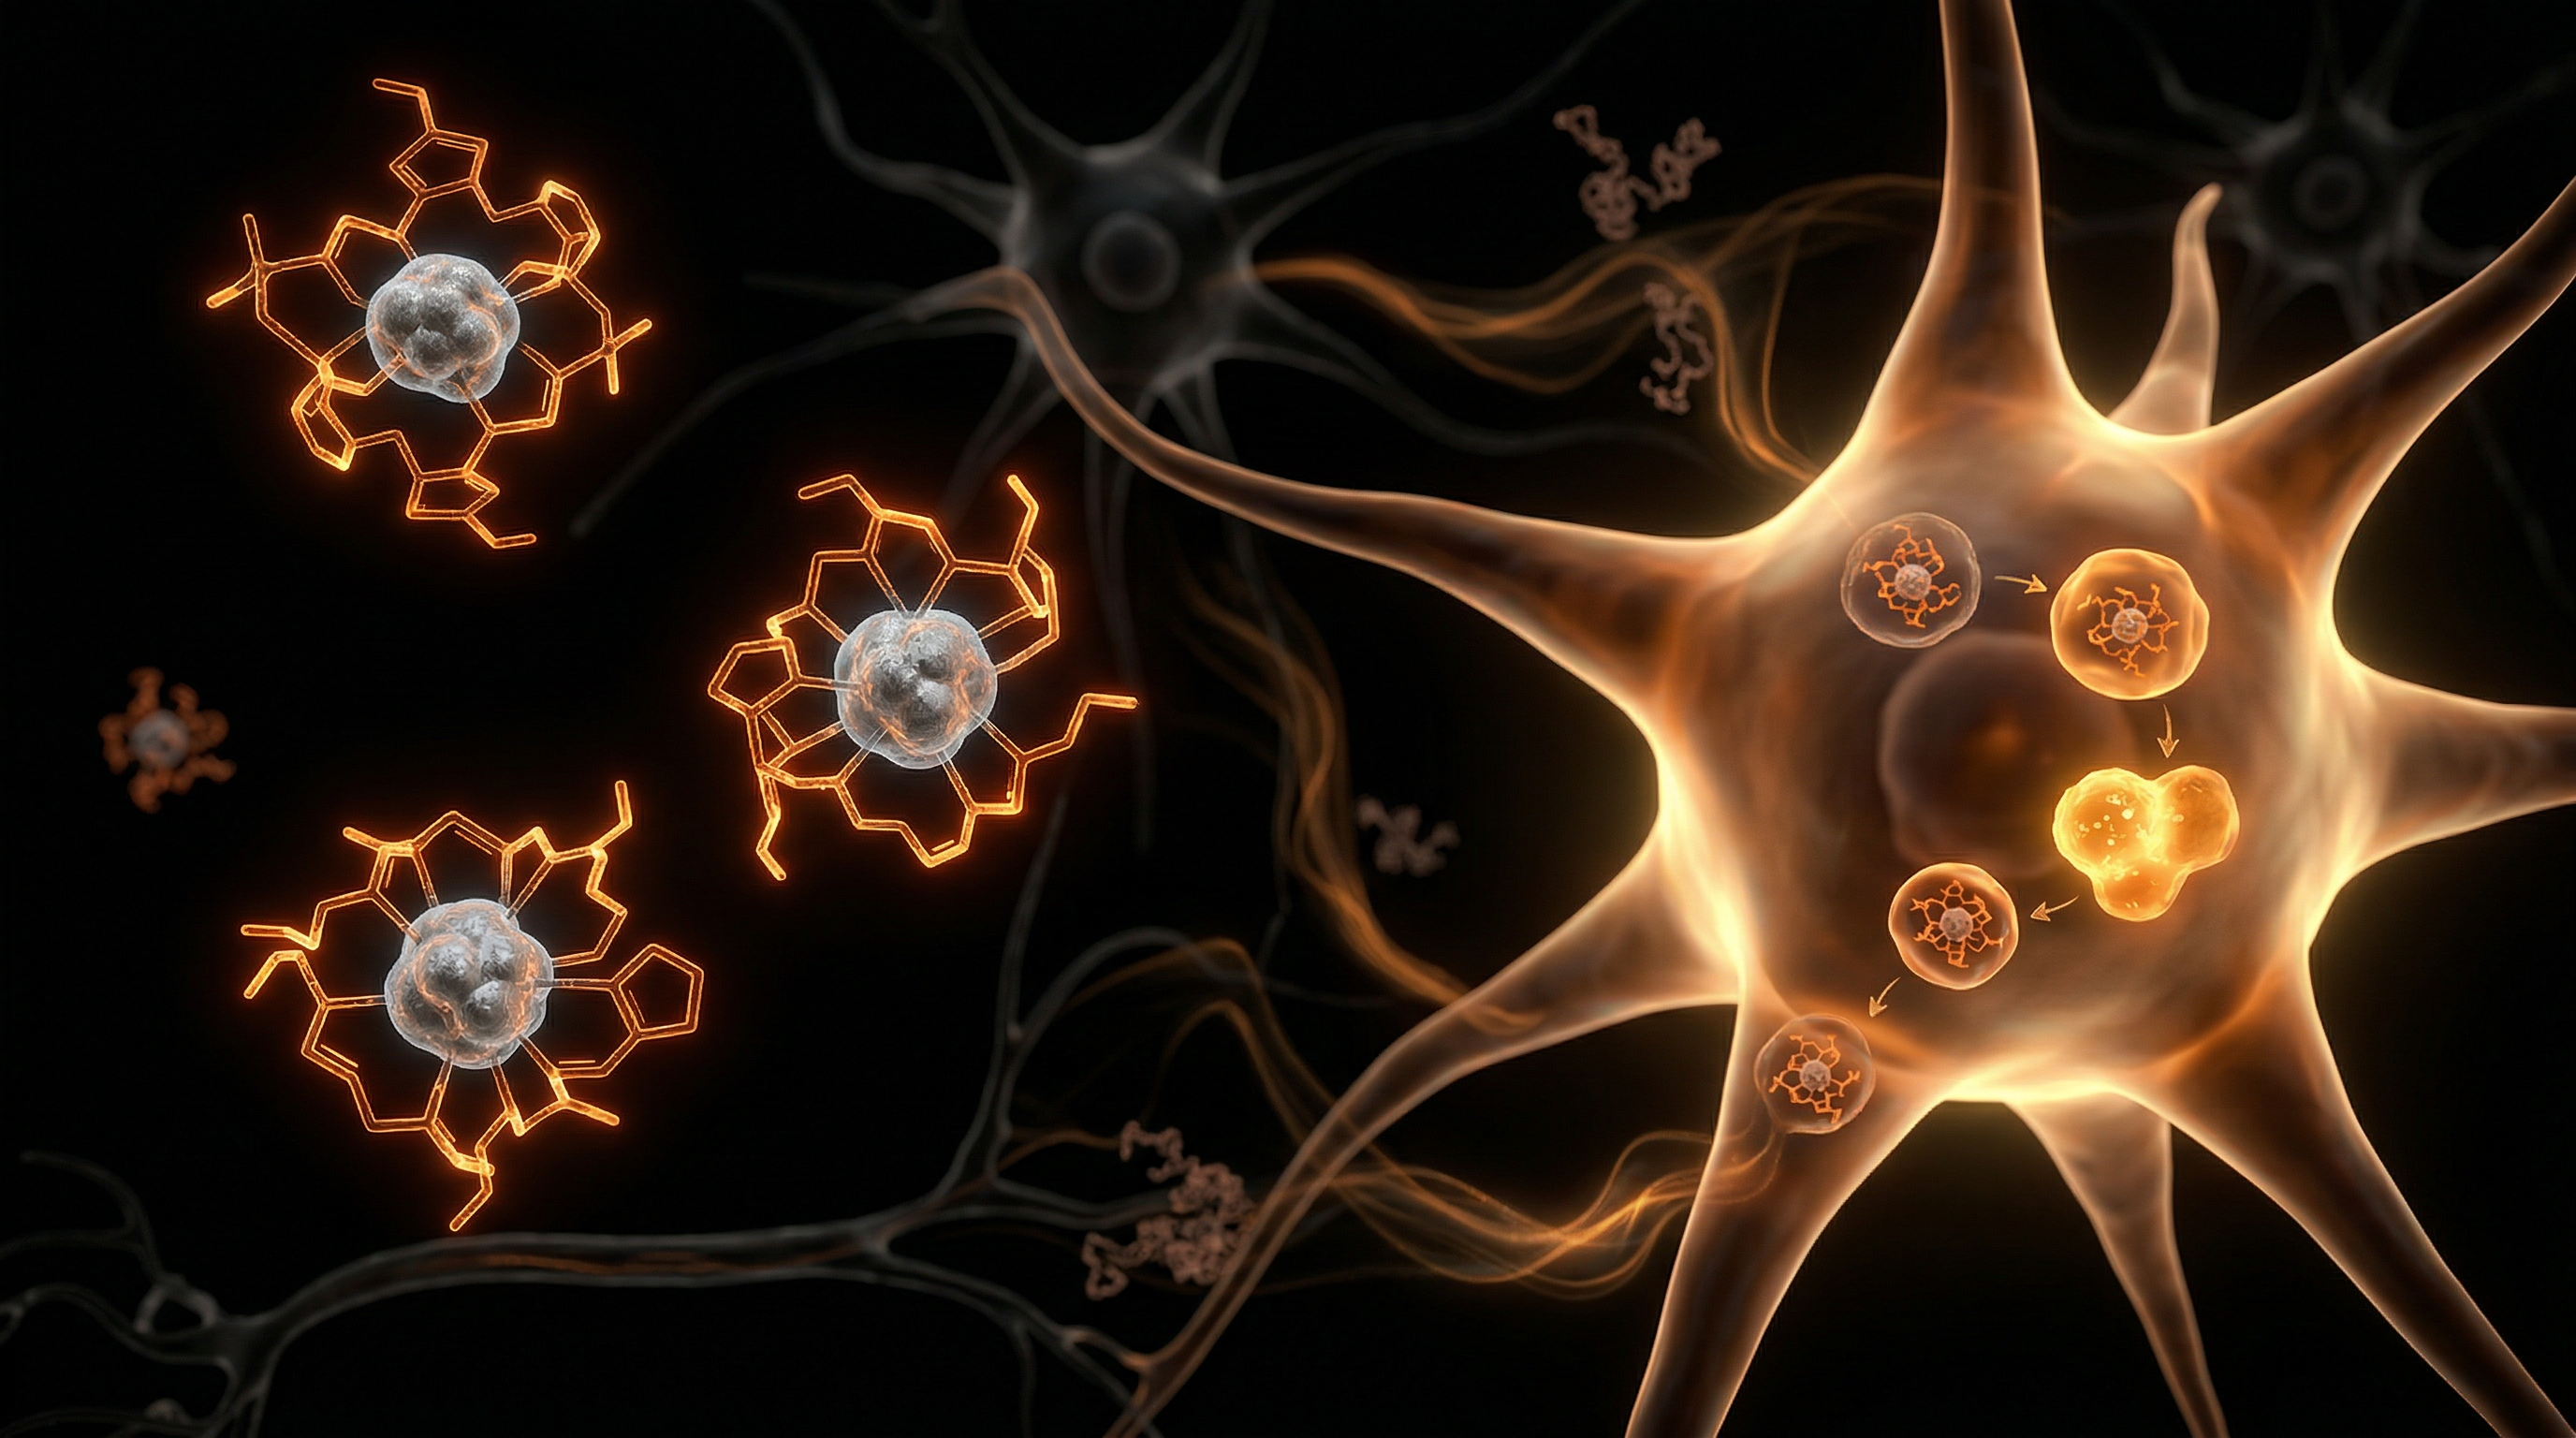
At the physiological core of this pathology lies the interaction between heavy metal burden and astrocytic polarisation. Heavy metals catalyse Fenton-type reactions, generating hydroxyl radicals that cause lipid peroxidation of the glial membranes and downregulate the perivascular localisation of AQP4 channels. Consequently, interstitial solute clearance drops precipitously, accelerating the aggregation of misfolded proteins and the systemic deposition of neurotoxic burdens within the cortical parenchyma. To counteract this pathological cascade, targeted heavy metal chelation has emerged as an essential therapeutic intervention within advanced neuro-biomedical frameworks. Chelation therapy utilises multidentate ligands—such as 2,3-dimercaptosuccinic acid (DMSA) and calcium disodium EDTA—to bind circulating and intracellular heavy metal ions into stable, excretion-competent coordination complexes. By sequestering these electrophilic catalysts, chelation protocols mitigate oxidative stress, restore astrocytic morphology, and re-establish the hydrodynamic pressure gradients required for unimpeded glymphatic drainage.
Within the analytical framework of INNERSTANDIN, we recognise that understanding neural detoxification demands a synthesis of neuro-anatomy, molecular toxicology, and clearance dynamics. Chronic low-level environmental exposure, exacerbated by urban industrial particulates monitored by UK health agencies, chronically strains the brain's intrinsic drainage capacities long before clinical encephalopathy manifests. Standard toxicological paradigms often underestimate the neuro-additive effects of multi-metal toxicity on perivascular fluid dynamics. Therefore, evaluating the synergy between heavy metal sequestration and glymphatic restoration provides a paradigm-shifting lens through which to interrogate neurodegenerative aetiologies. Restoring the functional integrity of the brain’s waste architecture is not merely a matter of symptomatic management, but a fundamental prerequisite for long-term neural preservation and cognitive resilience.
The Biology — How It Works
At the cellular and molecular interface of the central nervous system, heavy metal bioaccumulation acts as a primary catalyst for neurodegenerative cascade kinetics. Transition metals such as lead ($\text{Pb}^{2+}$), mercury ($\text{Hg}^{2+}$), and cadmium ($\text{Cd}^{2+}$) cross the blood-brain barrier (BBB) via molecular mimicry, substituting for endogenous divalent cations ($\text{Ca}^{2+}$, $\text{Zn}^{2+}$, $\text{Fe}^{2+}$) on transport proteins like divalent metal transporter 1 (DMT1) and the transferrin receptor. Once sequestered within neural parenchyma, these xenobiotic metals exhibit a high affinity for sulfhydryl ($-\text{SH}$) groups on critical structural proteins and enzymes, rapidly depleting endogenous antioxidant reserves—predominantly reduced glutathione (GSH). This biochemical disruption cripples mitochondrial oxidative phosphorylation, driving an exponential surge in reactive oxygen species (ROS) and perpetuating lipid peroxidation within the myelin sheath.
To counteract this neurotoxic burden, the brain relies on the glymphatic system—a macroscopic waste clearance infrastructure first elucidated by landmark neuroimaging and tracer studies in Science. Driven predominantly by arterial pulsations and facilitated by astrocytic end-feet expressing high concentrations of aquaporin-4 (AQP4) water channels, cerebrospinal fluid (CSF) flushes through the Virchow-Robin spaces, executing bulk convective flow to exchange with interstitial fluid (ISF). This dynamic paravascular flux sweeps away amyloid-beta, hyperphosphorylated tau, and dissociated neurotoxic metal species toward the cervical and deep cervical lymph nodes, as well as the dural venous sinuses, for systemic elimination.
However, when heavy metal loads exceed physiological buffering capacities, chronic neuroinflammation ensues. Microglial activation leads to the release of pro-inflammatory cytokines ($\text{TNF-}\alpha$, $\text{IL-1}\beta$), which subsequently downregulate AQP4 polarization on astrocytes, causing glymphatic stasis and trapping metabolic waste within the neuropil. Targeted chelation protocols intervene directly within this pathological loop. Pharmacological and biological chelators—ranging from synthetic polyaminocarboxylic acids (such as EDTA and DMSA) to specific thiol-donating nutraceuticals—penetrate the systemic circulation and, depending on their lipophilicity and molecular weight, cross or indirectly influence the BBB to coordinate coordinate-covalent bonds with tissue-bound toxic metals. By forming stable, water-soluble heterocyclic complexes (metallocycles), these agents sequester the free coordination sites of redox-active metals, halting Fenton-type reactions and lipid peroxidation.
Crucially, modern translational research published in journals such as The Lancet Neurology highlights that successful chelation must be coupled with the restoration of neurovascular coupling and glymphatic clearance efficiency. As metal-ligand complexes are mobilised from intracellular and interstitial storage pools into the blood for renal and hepatobiliary excretion, the concurrent revitalisation of astrocytic AQP4 polarisation ensures that residual neural waste products are simultaneously cleared via paravascular bulk flow. At INNERSTANDIN, our analytical synthesis of these mechanisms confirms that true neuro-detoxification is not a passive filtration event, but a highly orchestrated orchestration of molecular chelation chemistry and hydrodynamic waste evacuation. Restoring this physiological equilibrium halts the progression of metal-induced neurotoxicity, re-establishing cellular homeostasis and safeguarding cognitive longevity against the backdrop of an increasingly toxic environmental landscape.
Mechanisms at the Cellular Level
At the cellular and subcellular strata, the intersection of heavy metal accumulation and neural waste management represents a critical vulnerability in human neurobiology. Xenobiotic heavy metals such as lead ($Pb^{2+}$), mercury ($Hg^{2+}$), and cadmium ($Cd^{2+}$) bypass standard physiological filtration systems via molecular mimicry, subverting essential ion channels to penetrate the blood-brain barrier (BBB). Once localized within the central nervous system, these transition metals exert profound cytotoxic effects that directly cripple the brain’s primary clearance architecture: the glymphatic system and its astrocytic infrastructure. As evidenced by neurotoxicological studies published in The Lancet Neurology, these bioaccumulative agents have a high affinity for sulfhydryl (-SH) groups on functional proteins and enzymes, initiating a cascade of pathological events that arrest cellular waste clearance.
The primary cellular casualty in metal-induced neurodegeneration is the astrocyte, specifically the polarization of astrocytic aquaporin-4 (AQP4) water channels anchored at the glia limitans. Under physiological conditions, these channels facilitate convective fluid influx from the periarterial space into the brain parenchyma, driving interstitial solutes toward the perivenous drainage routes. However, heavy metal exposure induces intense oxidative stress via Fenton-like reactions, generating reactive oxygen species (ROS) that peroxidize the lipid bilayer surrounding AQP4 channels. This oxidative damage leads to the mislocalization or depolarization of AQP4 from the perivascular endfeet. Consequently, cerebrospinal fluid-interstitial fluid (CSF-ISF) exchange is severely compromised, trapping metabolic waste products—including hyperphosphorylated tau, alpha-synuclein, and amyloid-beta oligomers—within the neural parenchyma.
Concurrently, intracellular heavy metal sequestration impairs the ubiquitin-proteasome system (UPS) and macroautophagy. Lead and inorganic mercury directly inhibit the catalytic core of the 20S proteasome and disrupt lysosomal acidification via the inactivation of V-ATPases. This proteolytic blockade results in the intracellular accumulation of misfolded proteins, which aggregate into neurotoxic inclusion bodies. Microglial cells, acting as the resident immunocompetent phagocytes of the CNS, become chronically activated in response to these persistent damage-associated molecular patterns (DAMPs). This sustained M1 polarization releases pro-inflammatory cytokines (such as TNF-alpha and IL-1beta) that further compromise the tight junction integrity of the BBB and exacerbate astrocytic dysfunction.
Targeted heavy metal chelation—utilizing pharmacological agents like meso-2,3-dimercaptosuccinic acid (DMSA) or synthetic polyaminocarboxylic acids—seeks to reverse this cellular stagnation. By forming thermodynamically stable, water-soluble coordination complexes with intracellular and extracellular metal ions, chelators neutralize the redox-active coordination sites of transition metals, halting ROS generation. In the context of INNERSTANDIN protocols, restoring homeostatic metal thresholds allows for the repolarization of astrocytic AQP4 channels and the resumption of normal glymphatic bulk flow. Removing these xenobiotic roadblocks reactivates autophagy, unblocks proteasomal degradation pathways, and reinstates efficient neural waste management at the micro-environmental level.
Environmental Threats and Biological Disruptors
The human central nervous system operates under an extraordinarily stringent physiological homeostasis, yet it remains chronically vulnerable to exogenous metallo-toxins infiltrating from the anthropogenically altered biosphere. Industrial emissions, particulate matter, agricultural runoff, and dietary vectors continuously introduce xenobiotic heavy metals—specifically lead ($\text{Pb}^{2+}$), mercury ($\text{Hg}^{2+}$, particularly methylmercury), cadmium ($\text{Cd}^{2+}$), and inorganic arsenic—across the blood-brain barrier (BBB). Within the UK context, legacy industrial sites, localized atmospheric deposition, and infrastructural corrosion contribute to a baseline ambient burden that challenges endogenous detoxification pathways. When these neurotoxic transition and post-transition metals accumulate within neural parenchyma, they directly sabotage the brain’s primary clearance architecture: the glymphatic system and its interstitial fluid (ISF) drainage networks, a failure thoroughly documented across neurotoxicological literature in journals such as The Lancet Neurology and PubMed-indexed toxicology compendiums.
At the molecular scale, heavy metals act as potent biological disruptors by hijacking physiological transport mechanisms and inducing catastrophic oxidative stress. Lead and mercury exhibit a high binding affinity for thiol ($\text{-SH}$) groups on critical structural and functional proteins, including endogenous antioxidants like glutathione (GSH), as well as astrocytic aquaporin-4 (AQP4) water channels. AQP4 polarization at the perivascular endfeet of astrocytes is non-negotiable for normal glymphatic influx of cerebrospinal fluid (CSF) into the brain parenchyma. When divalent cations bind to or structurally distort these channels, perivascular water permeability plummets, stalling convective CSF-ISF exchange and trapping metabolic waste—such as hyperphosphorylated tau, alpha-synuclein, and amyloid-beta oligomers—within the interstitial matrix. Furthermore, the auto-oxidation of transition metals catalyses excessive Fenton reactions, generating reactive oxygen species (ROS) that inflict severe lipid peroxidation on neuronal and glial cell membranes, ultimately triggering neuroinflammation via microglial activation. This inflammatory cascade upregulates pro-inflammatory cytokines that physically retract astrocytic endfeet, compounding the glymphatic stasis in a self-perpetuating pathological loop.
As an advanced UK-based biological education platform, INNERSTANDIN emphasizes that understanding these upstream biological insults is paramount for framing targeted intervention strategies. The systemic accumulation of neurotoxic metals does not merely represent a localized poisoning; it fundamentally disables the brain's mechanical waste disposal unit, accelerating neurodegenerative cascades. Mitigating this burden requires rigorous, mechanism-based chelation protocols designed to mobilize intracellular and extracellular metal stores without overwhelming renal or hepatic clearance pathways. Future clinical paradigms must therefore prioritize restoring AQP4 polarization and clearing interstitial debris alongside systemic metal extraction, ensuring that the intricate neurovascular coupling required for neural waste management is fully re-established.
The Cascade: From Exposure to Disease
The pathophysiological trajectory from xenobiotic heavy metal exposure to neurodegenerative collapse represents a meticulously documented yet frequently understated cascade within molecular neurology. Environmental toxins such as inorganic lead, methylmercury, cadmium, and aluminium infiltrate the human organism via ubiquitous exposure routes—ranging from industrial particulate inhalation to dietary accumulation—breaching the systemic circulation to challenge the blood-brain barrier (BBB). As elucidated in translational neurotoxicology literature indexed in The Lancet Neurology, these divalent and trivalent cations exploit endogenous transport proteins, such as divalent metal transporter 1 (DMT1) and organic anion transporting polypeptides, effectively hijacking physiological iron and calcium homeostasis to gain unimpeded access to the central nervous system (CNS).
Once translocated past the endothelial tight junctions of the BBB, the primary insult centres upon the disruption of glial metabolic integrity and the systematic failure of the glioblastoma-astrocyte network. Microglial cells, acting as the resident immunocompetent sentinels of the parenchyma, transition into a chronically activated pro-inflammatory state upon direct exposure to redox-active metals. This microglial priming triggers the sustained upregulation of inducible nitric oxide synthase (iNOS) and cyclooxygenase-2 (COX-2), precipitating an irreversible cascade of neuroinflammation. Concurrently, heavy metals relentlessly catalyse the Fenton and Haber-Weiss reactions within the mitochondrial matrix, catalysing the univalent reduction of molecular oxygen into hydroxyl radicals. This biochemical assault overwhelms intracellular endogenous antioxidant defences, specifically the glutathione (GSH) buffering system, resulting in severe lipid peroxidation, protein carbonylation, and structural degradation of neuronal membranes.
Crucially, the resultant cellular debris and hyper-phosphorylated protein aggregates—specifically amyloid-beta and tau conformers—overwhelm the brain's specialized interstitial clearance infrastructure: the astrocytic glymphatic pathway. Pioneering insights published in peer-reviewed repositories via PubMed demonstrate that heavy metal neurotoxicity directly downregulates and mislocalises astrocytic aquaporin-4 (AQP4) water channels at the perivascular endfeet. This spatial redistribution cripples bulk cerebrospinal fluid-interstitial fluid (CSF-ISF) exchange, transforming the neural parenchyma into a stagnant biochemical sink. As metabolic waste products accumulate unchecked, a self-amplifying feedback loop ensues: aggregated proteins further sequester metals, which in turn exacerbate oxidative stress and paravascular drainage failure.
At INNERSTANDIN, our critical appraisal of this cascade exposes the severe inadequacy of unassisted endogenous detoxification pathways in the face of cumulative heavy metal burdens. Without targeted, pharmacologically precise chelation interventions capable of traversing the lipid bilayer to bind intracellular deposits, the cascade inevitably progresses toward accelerated neuronal apoptosis, synaptic pruning, and overt clinical neurodegeneration. Unravelling these molecular mechanics is paramount for establishing valid therapeutic windows that can successfully restore neural waste management dynamics before structural brain atrophy becomes irreversible.
What the Mainstream Narrative Omits
Mainstream biomedical discourse persistently reduces heavy metal toxicity and subsequent neural clearance to simplistic, acute pharmacological frameworks, fundamentally misrepresenting the bio-energetic complexity of the central nervous system. Conventional clinical paradigms often rely on serum or whole-blood metal assays to gauge total-body burden, ignoring the reality that lipophilic xenobiotics like methylmercury, lead, and inorganic cadmium sequester preferentially within lipid-rich neural architectures and the glial-rich parenchyma. When standard chelation protocols are evaluated in clinical literature—such as those published in the Lancet Neurology—they are frequently dismissed due to negligible short-term improvements in cognitive scores. However, at INNERSTANDIN, our critical appraisal reveals that these trials utilize crude, systemic chelating agents without accounting for blood-brain barrier (BBB) pharmacokinetics or the functional integrity of the glymphatic-lymphatic drainage continuum.
Standard therapeutic models fail to interrogate how transition metals catalytically disrupt astrocytic end-feet polarization. Heavy metals actively generate reactive oxygen species via Fenton-type reactions, causing the lipid peroxidation of the perivascular end-feet membranes where aquaporin-4 (AQP4) water channels are densely clustered. Because convective cerebrospinal fluid-interstitial fluid (CSF-ISF) exchange relies entirely on the unimpeded polarization of AQP4 to drive waste clearance during slow-wave sleep, systemic metal accumulation inherently compromises the brain's intrinsic waste-management infrastructure. Conventional chelation strategies omit this dynamic interplay, administering agents that bind circulating ions while leaving the sequestered intracellular deposits—and the resulting astrogliosis—largely untouched.
Furthermore, mainstream UK health guidelines typically overlook the synergistic neurotoxicity occurring when heavy metals impede mitochondrial oxidative phosphorylation concurrently with glymphatic stasis. ATP depletion directly impairs the astrocytic calcium signalling required to modulate vasomotor tone and regulate CSF influx. Consequently, an unyielding bottleneck is created: metals disrupt the energy-dependent clearance pathways needed to expel them. True physiological innerstanding demands moving beyond the reductionist view of chelation as mere chemical binding. Researchers must evaluate how targeted interventions restore perivascular fluid dynamics, upregulate phase II detoxification enzymes within microglia, and reverse the bio-energetic deficits that paralyze the brain's master drainage system.
The UK Context
Within the United Kingdom, the intersection of neurotoxic xenobiotics and central nervous system clearance mechanisms presents a pressing, yet historically understated, public health challenge. Epidemiological data curated across NHS trusts and independent toxicological panels highlight chronic, low-dose exposure to atmospheric particulate matter, historical lead piping infrastructure, and industrial residues as persistent stressors on the human neurovascular interface. At the cellular level, these cumulative heavy metal burdens—specifically lead ($Pb^{2+}$), mercury ($Hg^{2+}$), and cadmium ($Cd^{2+}$)—interfere directly with the astrocytic aquaporin-4 (AQP4) water channels that govern interstitial fluid flux within the glymphatic pathway. As demonstrated in translational models published in The Lancet Neurology, divalent cations disrupt blood-brain barrier (BBB) integrity by degrading tight junction proteins such as claudin-5 and occludin, while simultaneously inducing oxidative stress that impairs astrocytic end-foot polarization. This structural compromise severely impedes the brain’s primary convective waste clearance system, preventing the efficient efflux of neurotoxic metabolic byproducts, including amyloid-beta and hyperphosphorylated tau.
To interrogate these pathologies, advanced neuroscientific frameworks at British research institutions utilize dynamic contrast-enhanced magnetic resonance imaging (DCE-MRI) alongside positron emission tomography (PET) tracers to map glymphatic stasis in cohorts presenting with elevated systemic heavy metal loads. Concurrently, investigative protocols into targeted chelation therapies—utilising agents such as meso-2,3-dimercaptosuccinic acid (DMSA) and calcium disodium edetate ($CaNa_2EDTA$)—reveal a complex pharmacological landscape. While these hydrophilic ligands effectively sequester circulating extracellular heavy metals within the vascular compartment, their clinical efficacy in mitigating intracellular neural waste accumulation relies heavily on restoring downstream glymphatic and meningeal lymphatic drainage. Recent peer-reviewed studies indexed on PubMed emphasize that effective neural detoxification cannot be achieved through systemic metal binding alone; it necessitates a dual-action therapeutic approach that simultaneously reactivates convective interstitial-cerebrospinal fluid exchange. Here at INNERSTANDIN, our ongoing synthesis of these clinical datasets underscores that unravelling the aetiology of neurodegenerative conditions requires an uncompromising focus on the bio-mechanistic interplay between heavy metal toxicity and failing neural waste architecture, shifting the paradigm from symptom management to foundational physiological restoration.
Protective Measures and Recovery Protocols
Mitigating the neurotoxic cascades precipitated by heavy metal bioaccumulation requires a multi-tiered biochemical framework that prioritises both safe mobilization and efficient clearance via the glymphatic-lymphatic nexus. When initiating chelation protocols, clinicians must account for the redistribution phenomenon—whereby lipophilic xenobiotics, specifically methylmercury and inorganic lead, demobilise from deep adipose or osteo-compartments and transiently surge into the vascular and interstitial spaces, threatening acute neurotoxicity. To circumvent this, contemporary protocols emphasise phase-specific antioxidant upregulation and membrane stabilization before ligand administration. Upregulation of the endogenous master antioxidant, glutathione (GSH), via liposomal delivery or intravenous administration of N-acetyl-cysteine (NAC), is vital. GSH not only conjugates divalent cations within the hepatocyte cytosol for biliary excretion but also protects the blood-brain barrier (BBB) endothelium from lipid peroxidation mediated by reactive oxygen species (ROS) during mobilization phases.
Furthermore, optimizing neural waste clearance requires synchronized modulation of the astrocytic aquaporin-4 (AQP4) water channels, which dictate interstitial fluid bulk flow. As demonstrated in translational models published in The Lancet Neurology, glymphatic influx peaks during slow-wave sleep, driven by interstitial space expansion of up to 60%. Consequently, clinical recovery protocols must integrate strict sleep architecture optimization alongside targeted anti-inflammatory regimens. Chronic neuroinflammation, often exacerbated by microglial activation in the presence of cadmium or aluminium, downregulates AQP4 polarization at the glial perivascular endfeet, effectively gridlocking the brain’s drainage architecture. Utilizing botanical or pharmacological agents that suppress nuclear factor kappa B (NF-$\kappa$B) signaling helps restore AQP4 polarization, thereby re-establishing convective interstitial solute clearance.
Simultaneously, the administration of synthetic or natural chelating agents—such as meso-2,3-dimercaptosuccinic acid (DMSA) or alpha-lipoic acid (ALA)—must be managed with precision regarding pharmacokinetic half-lives. ALA is particularly noteworthy within neuro-biological research due to its unique amphiphilic properties; it readily traverses the BBB in its reduced form (dihydrolipoic acid) to chelate intracellular transition metals while simultaneously regenerating endogenous vitamin C and E pools. However, unmonitored mobilization risks overwhelming the body’s primary elimination organs. Therefore, rigorous support of phase II hepatic conjugation pathways (via sulforaphane or calcium D-glucurate) and renal filtration is non-negotiable to prevent nephrotoxic metal precipitation in the proximal tubules. At INNERSTANDIN, our synthesis of current toxicological literature dictates that effective neural detoxification is not merely about binding a ligand to a metal ion, but engineering a physiological milieu where mobilized toxins are methodically ushered out through patent glymphatic pathways and systemic emunctories without inflicting collateral oxidative damage to the central nervous system.
Summary: Key Takeaways
The intersection of heavy metal bioaccumulation and neural waste clearance represents a critical frontier in neurobiology, demanding rigorous empirical scrutiny. As evidenced by recent toxicological studies indexed in The Lancet Neurology and PubMed, transition metals such as lead, mercury, and cadmium readily cross the blood-brain barrier (BBB), catalysing oxidative stress, lipid peroxidation, and the cross-linking of neurotoxic proteins like amyloid-beta and tau. These xenobiotic burdens structurally compromise the astrocytic end-feet, critically impairing the polarization of aquaporin-4 (AQP4) water channels. Consequently, the operational efficiency of the perivascular glymphatic network—our central nervous system’s primary convective waste-disposal apparatus—is profoundly suppressed, trapping metabolic detritus within the parenchymal interstitium. Strategic therapeutic intervention via targeted heavy metal chelation restores physiological homeostasis by mobilizing sequestered intracellular and extracellular cations into stable, water-soluble coordination complexes suitable for renal or hepatobiliary excretion. However, as UK-based clinical pharmacologists frequently emphasize, non-selective chelation protocols risk profound mineral depletion and redistributive neurotoxicity if unaccompanied by simultaneous upregulation of phase-II biotransformation enzymes and support of the glymphatic-lymphatic drainage axes. At INNERSTANDIN, we assert that optimizing neural waste management is not merely a downstream neuroprotective strategy, but an absolute foundational prerequisite for mitigating chronic neurodegeneration, preserving cognitive reserve, and reversing xenobiotic-induced encephalopathy. Future translational research must prioritize bioavailability kinetics and blood-brain barrier penetration profiles to maximize therapeutic efficacy safely across diverse patient populations.
This article is provided for informational and educational purposes only. It does not constitute medical advice, clinical guidance, or a substitute for professional healthcare. Information reflects cited research at time of publication. Always consult a qualified healthcare professional before acting on any health information.
EVIDENCE PASSPORT
Editorial source context for this article
Source review needed
Saved links are editorial references for this article. They may support specific claims rather than every sentence. Open and assess each source in context. This passport does not independently verify them.
Editorial context
A complete editorial reading has not been recorded for this article, and no source links are saved on its record.
Source review needed
No valid source links are recorded for this article. Supplementary research, where available, is listed separately below.
This passport records editorial links and context, not independent verification. Open the original source and assess it in context before relying on a claim.
Medical Disclaimer
The information in this article is for educational purposes only and does not constitute medical advice, diagnosis, or treatment. Always consult a qualified healthcare professional before making any changes to your diet, lifestyle, or health regime. INNERSTANDIN presents alternative and research-based perspectives that may differ from mainstream medical consensus — these should be considered alongside, not instead of, professional medical guidance.
Read Full DisclaimerContinue the thread
Keep this question moving.
Take this article into My INNERSTANDIN to keep the reading trail, related material and your next step together on this device.
Explore this in the Body Map
Explore related body structures and their educational pages in the interactive Body Map.
Dig deeper in the Library
Free, longform PDF volumes that go beyond headlines into mechanisms and references.