Iodine: The Thyroid Mineral Being Systematically Depleted in Modern Diets
Discuss this resourceUpdated October 2026
Iodine is essential for thyroid hormone synthesis, breast tissue health, cognitive development and detoxification of halogens (fluoride, chloride, bromide). The UK population is among the most iodine-deficient in Europe, with serious consequences for metabolic and reproductive health.
Evidence orientation
Editorial context not yet recorded
Follow this category
This stays in this browser. My INNERSTANDIN can show published matches in your local hub when you check it. It does not send email, push, or alert notifications.
Local learning review
A private browser aid for revisiting ideas. It is not an alert or a health recommendation.
Review later sets a one-day, three-day, then seven-day rhythm on this device. Choose it only when you want to revisit this article.

Overview
Iodine ($I^-$), a primordial halogen with an atomic weight of 126.90, functions as an indispensable trace element dictating mammalian bioenergetics, neurodevelopment, and systemic metabolic homeostasis. At the physiological core of human endocrinology is its absolute requirement for the synthesis of thyroid hormones—thyroxine ($T4$) and triiodothyronine ($T3$). However, contemporary populations across the United Kingdom and industrialized nations face a stealthy, systemic depletion of this critical micronutrient. Driven by shifting agricultural paradigms, the displacement of iodised salt by unrefined alternatives, and the widespread dietary proliferation of goitrogens, modern nutrition has inadvertently engineered an iodine deficit. This deficit undermines fundamental cellular respiration across virtually every organ system.
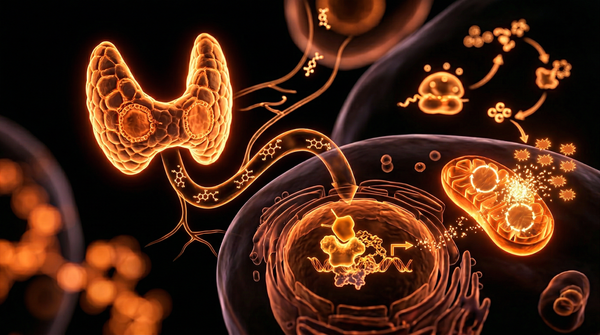
From a mechanistic standpoint, inorganic iodide is actively transported into the basolateral membrane of the thyroid follicular cell via the sodium-iodide symporter (NIS), an intrinsic transmembrane glycoprotein. Driven by the $Na^+/K^+-ATPase$ electrochemical gradient, this transport system concentrates $I^-$ intracellularly before it undergoes apical efflux into the follicular lumen via pendrin. Once luminal, thyroid peroxidase (TPO) catalyses the hydrogen peroxide-dependent oxidation of iodide and the subsequent iodination of tyrosyl residues on thyroglobulin. This intricate enzymatic orchestration produces monoiodotyrosine (MIT) and diiodotyrosine (DIT), which couple to form the prohormone $T4$ and the biologically active $T3$.
Crucially, the biological footprint of iodine extends far beyond the thyroid gland. Extra-thyroidal tissues—including the mammary glands, gastric mucosa, salivary glands, choroid plexus, and the vascular endothelium—express high-affinity NIS channels, highlighting an evolutionarily conserved demand for iodide for non-hormonal purposes. Within these peripheral tissues, molecular iodine ($I_2$) acts as a potent antioxidant, neutralizing reactive oxygen species (ROS) and modulating apoptotic pathways. Furthermore, adequate intracellular iodine status regulates apoptosis and maintains antiproliferative states in estrogen-sensitive tissues, providing a biological safeguard against hyperplastic transformations.
Despite its foundational role in human physiology, modern dietary shifts have systematically compromised iodine intake. Comprehensive urinary iodine concentration (UIC) surveys, alongside data published in The Lancet and various PubMed-indexed epidemiological reviews, underscore a concerning resurgence of mild-to-moderate iodine deficiency within the UK. The cessation of traditional industrial practices, such as the use of iodine-containing sterilising agents in the dairy industry, coupled with public health mandates to reduce sodium chloride consumption without a parallel shift toward mandatory universal salt iodisation, has precipitated a population-wide nutritional vulnerability.
At INNERSTANDIN, our rigorous biochemical analysis reveals that sub-optimal iodine status is not merely a localized thyroid concern; it represents a systemic deceleration of human cellular kinetics. When the availability of $I^-$ drops, mitochondrial oxidative phosphorylation falters, neurocognitive processing speeds decline due to impaired myelination, and the body’s innate detoxification mechanisms are severely compromised. Addressing this quiet depletion requires a paradigm shift in how clinical researchers and nutritional scientists view trace mineral sufficiency, moving beyond mere deficiency prevention toward the optimisation of human bioenergetic potential.
The Biology — How It Works
At the cellular level, iodine ($\text{I}^-$) functions as an essential biochemical cornerstone, far exceeding its classical characterisation as a mere substrate for thyroid hormonogenesis. The human body’s utilization of this halogen is mediated through sophisticated active transport mechanisms, most notably the sodium-iodide symporter (NIS)—an intrinsic basolateral membrane glycoprotein predominantly expressed in the thyroid follicular cells, but crucially distributed across extra-thyroidal tissues including the gastric mucosa, lactating mammary glands, salivary glands, choroid plexus, and renal tubules. As documented in seminal physiological literature published in journals such as The Lancet and Endocrine Reviews, the NIS utilises the electrochemical sodium gradient established by $\text{Na}^+/\text{K}^+$-ATPase to actively concentrate iodide against a steep concentration gradient. In the euthyroid thyroid gland, this concentrating capacity is monumental, maintaining intracellular concentrations orders of magnitude higher than ambient plasma levels.
Once internalized into the thyrocyte, iodide is translocated across the apical membrane into the follicular lumen via pendrin—an anion exchanger. Here, it undergoes rapid enzymatic oxidation catalysed by thyroid peroxidase (TPO), utilizing hydrogen peroxide ($\text{H}2\text{O}2$) generated by dual oxidases (DUOX1 and DUOX2). This oxidation converts $\text{I}^-$ into a reactive iodine species capable of the immediate electrophilic iodination of tyrosyl residues within thyroglobulin (Tg), a large glycoprotein matrix. Subsequent oxidative coupling of adjacent iodotyrosines (mono- and di-iodotyrosine) yields the definitive pro-hormones thyroxine ($\text{T}4$) and the biologically hyper-potent triiodothyronine ($\text{T}3$).
Beyond the hypothalamus-pituitary-thyroid (HPT) axis, the systemic biology of iodine encompasses profound autocrine, paracrine, and antioxidant functions. As established by extensive PubMed-indexed molecular research, molecular iodine ($\text{I}_2$) exhibits potent antioxidant properties, acting as an electron donor that scavenges reactive oxygen species (ROS) and protects macromolecular structures—particularly in tissues possessing high iodinating capacity, such as the mammary epithelium. Furthermore, un-iodinated iodine complexes with endogenous lipids to form iodolipids (such as 6-iodolactone), which act as critical physiological regulators of apoptosis and cell cycle arrest in rapidly proliferating tissues. Disruption of this pathway via iodine insufficiency removes natural apoptotic brakes, a mechanism increasingly implicated in the pathogenesis of benign and malignant proliferative disorders within the UK demographic.
The modern attenuation of dietary iodine—exacerbated by shifting agricultural practices, the reduction of iodine-based sanitisers in the dairy industry, and the ubiquitous replacement of iodised salt with non-iodised alternatives in processed foods—directly impairs these multi-systemic pathways. When circulating iodide levels fall below the threshold required for optimal NIS saturation, the biochemical cascade stutters. Intracellular oxidative stress rises, extrathyroidal tissues are deprived of their required halide, and the thyroid gland undergoes compensatory hypertrophy, shifting the delicate physiological equilibrium towards sub-clinical hypometabolism. At INNERSTANDIN, we recognise that understanding this foundational biochemistry is paramount to addressing the silent depletion currently compromising human physiological resilience across populations.
Mechanisms at the Cellular Level
At the subcellular level, iodine’s biological mandate extends far beyond the simplistic paradigm of thyroid hormone synthesis. While thyroglobulin iodination within the follicular lumen of the thyroid gland remains its most canonical role, molecular physiology reveals iodine as an essential pleiotropic regulator operating across diverse extrathyroidal tissues. Transported primarily via the sodium-iodide symporter (NIS)—an intrinsic basolateral membrane glycoprotein—iodide is actively internalized against an electrochemical gradient in cells as disparate as gastric mucosa, lactating mammary glands, salivary acini, and the choroid plexus. This ubiquitous expression underscores a fundamental evolutionary dependence on the halogen that contemporary dietary shifts have systematically compromised.
Intracellularly, iodine exerts profound antioxidant and apoptotic governance. Research indexed in major biomedical repositories demonstrates that molecular iodine ($I_2$) acts as a potent electron donor, directly scavenging reactive oxygen species (ROS) and neutralizing lipid peroxidation cascades within cellular membranes. In mammary architecture, for instance, iodine undergoes intracellular peroxidation and binds to specific long-chain fatty acids, forming iodolipids such as 6-iodo-5-hydroxy-eicosatrienoic acid. These endogenous ligands are high-affinity agonists for peroxisome proliferator-activated receptors (PPARs), specifically PPAR-$\gamma$. Activation of the PPAR-$\gamma$ pathway initiates apoptosis in dysplastic cell lines while preserving normal epithelial architecture, elucidating a critical oncostatic mechanism that is heavily impaired under conditions of systemic halide deficiency.
Simultaneously, the endocrine machinery relies on precise intracellular iodothyronine deiodinase enzyme kinetics (Types 1, 2, and 3). These selenoproteins govern the bioactivation and inactivation of pro-hormone thyroxine ($T4$) to the transcriptionally active triiodothyronine ($T3$). Within the nuclear envelope of target cells, $T3$ binds to nuclear thyroid hormone receptors ($\text{TR}\alpha$ and $\text{TR}\beta$), heterodimerizing with the retinoid X receptor (RXR) to modulate the transcription of thousands of genes critical for mitochondrial oxidative phosphorylation, thermogenesis, and cellular respiration. When iodine availability plummets—exacerbated in the UK by declining iodine concentrations in dairy and a lack of mandatory fortification policies—intracellular $T3$ signaling stutters. Mitochondrial ATP production drops, the efficiency of the electron transport chain falters, and cellular senescence accelerates.
Furthermore, modern dietary antagonists systematically subvert these delicate cellular pathways. Halide competition at the NIS receptor site by xenobiotic environmental toxins—specifically perchlorate, thiocyanate, and fluorides—actively inhibits cellular iodine uptake. These anions possess a charge-to-radius ratio that fools the symporter, competitively blocking iodide influx and starving dependent tissues of the halogen. At INNERSTANDIN, our interrogation of the literature reveals that this chronic competitive inhibition, paired with falling nutritional intake, creates an intracellular famine state. This is characterized by diminished antioxidant capacity, dysregulated apoptotic signaling, and compromised metabolic throughput. Restoring cellular homeostasis therefore requires looking past rudimentary dietary baselines and addressing the biochemical realities of halogen antagonism at the membrane interface.
Environmental Threats and Biological Disruptors
Modern anthropogenic disruption of the human iodine axis extends far beyond the well-documented shift away from iodised table salt and the reduction of dairy-derived residues in industrial baking. At the molecular level, the human body's physiological uptake of iodine ($I^-$) is under continuous siege from a triad of environmental xenobiotics that share structural homology with halide ions. Perchlorate ($ClO4^-$), thiocyanate ($SCN^-$), and nitrate ($NO3^-$) act as potent, competitive inhibitors of the sodium-iodide symporter (NIS)—the transmembrane glycoprotein situated on the basolateral membrane of thyroid follicular cells responsible for active iodine accumulation.
According to toxicological profiling published in environmental health literature, perchlorate contamination—widespread in agricultural runoff, rocket propellant residue, and improperly treated municipal water supplies—exhibits a binding affinity for the NIS that outcompetes physiological iodide. By competitively blocking this symporter, environmental perchlorate effectively throttles intracellular iodide concentration, starving thyroglobulin of the requisite substrate for monoiodotyrosine (MIT) and diiodotyrosine (DIT) coupling. This is compounded by widespread dietary and industrial exposure to thiocyanates, found abundantly in cruciferous vegetables grown in sulphur-laden soils, but more insidiously introduced via cigarette smoke and industrial air pollution. Thiocyanate not only competitively inhibits the NIS but also directly discharges accumulated iodide from the thyroid gland, accelerating systemic iodine wasting.
Concurrently, the British population faces a chronic, low-level toxicological burden from organohalogen pollutants, specifically polybrominated diphenyl ethers (PBDEs) and polychlorinated biphenyls (PCBs), alongside widespread environmental fluoride exposure. These lipophilic disruptors accumulate in adipose tissue and exert profound anti-thyroid actions. Research indexed in PubMed demonstrates that brominated and chlorinated compounds structurally mimic thyroid hormones (thyroxine, $T4$, and triiodothyronine, $T3$), competitively binding to transthyretin and serum thyroid-binding globulin. This competitive displacement artificially elevates free hormone levels in transient assays, triggering a negative feedback loop at the level of the hypothalamus-pituitary-thyroid (HPT) axis. The resulting downregulation of thyroid-stimulating hormone (TSH) synthesis masks the underlying tissue-level iodine starvation, leading to insidious, sub-clinical hypothyroidism that routinely evades standard endocrinological screening protocols in UK clinical practice.
Furthermore, the ubiquity of plasticisers such as bisphenol A (BPA) and phthalates—potent endocrine-disrupting chemicals (EDCs) heavily documented in European Food Safety Authority (EFSA) evaluations—further impairs thyroid hormone receptor transcription and hepatic glucuronidation pathways. These EDCs upregulate UDP-glucuronosyltransferase activity, accelerating the clearance of active thyroid hormones from serum while simultaneously impairing iodine organification within the thyrocyte lumen.
At INNERSTANDIN, our synthesis of these converging toxicological vectors reveals a critical paradigm shift: iodine deficiency in the contemporary UK populace is rarely a simple matter of inadequate dietary intake. Rather, it represents a state of functional, toxicant-induced blockade. The systemic saturation of biological space with goitrogenic halide analogues and endocrine-disrupting xenobiotics ensures that even individuals meeting historical dietary reference values for iodine experience cellular-level starvation. Restoring homeostatic thyroid function therefore necessitates not merely micronutrient repletion, but a rigorous, mechanism-led strategy to mitigate environmental halide exposure and upregulate Phase II hepatic detoxification pathways capable of clearing these persistent biological disruptors.
The Cascade: From Exposure to Disease
The depletion of iodine within the contemporary UK food matrix initiates a predictable, highly pathogenic physiological cascade that extends far beyond simple thyroid dysfunction. As documented in epidemiological surveys such as the National Diet and Nutrition Survey (NDNS), declining dietary iodine—exacerbated by the displacement of traditional dairy and iodised salt with ultra-processed alternatives—establishes a state of chronic subclinical deficiency. At the cellular level, this deficit disrupts the exquisitely balanced hypothalamic-pituitary-thyroid (HPT) axis, fundamentally compromising metabolic homeostasis and accelerating systemic pathology.
The primary disruption occurs within the thyrocyte. Iodine, predominantly absorbed as iodide ($I^-$), is actively transported across the basolateral membrane via the sodium-iodide symporter (NIS), a process driven by the $Na^+/K^+$-ATPase gradient. In states of chronic depletion, insufficient intracellular iodide concentrations impair the organification of thyroglobulin by thyroid peroxidase (TPO), directly suppressing the synthesis of prohormone thyroxine ($T4$) and the bioactive triiodothyronine ($T3$). To compensate for this biochemical bottleneck, elevated circulating levels of thyroid-stimulating hormone (TSH) signal via the G-protein-coupled TSH receptor, driving thyrocyte hyperlasia, hypertrophy, and increased vascularity. As demonstrated in histopathological evaluations published in The Lancet, persistent TSH stimulation transforms normal thyroid architecture into a heterogenous, multinodular goitre, characterised by focal areas of cellular exhaustion and fibrosis.
However, restricting the systemic consequences of iodine deficiency solely to thyroid morphology ignores the ubiquitous distribution of the NIS across non-thyroidal tissues. As extensively detailed in peer-reviewed literature indexed on PubMed, extra-thyroidal sodium-iodide symporters are densely expressed in the mammary glands, gastric mucosa, salivary glands, choroid plexus, and thymic stroma. In the mammary epithelium, iodine is essential for normal ductal morphogenesis and the antioxidant neutralisation of lipid peroxides. Iodine depletion in these tissues removes a critical protective mechanism, predisposing ductal cells to oestrogen-driven atypia and increasing the relative risk of fibrocystic breast disease and carcinogenesis. Concurrently, gastric parietal cells, which rely on adequate iodide accumulation for optimal functioning, experience disrupted acid-base regulation and compromised mucosal immunity.
Furthermore, the systemic cascade impacts neurodevelopment and systemic oxidative stress. T3 is non-negotiable for mammalian central nervous system myelination, dendritic branching, and synaptic plasticity during critical developmental windows. Even mild maternal hypothyroxinaemia, induced by subclinical iodine deficiency, correlates measurably with lowered offspring intelligence quotients and executive function deficits—a public health reality substantiated by cohorts across the British Isles. Simultaneously, systemic iodine deprivation impairs the generation of nascent iodolipids (such as 6-iodolactone), which act as endogenous ligands regulating apoptosis and proliferation in various epithelial tissues. When these local regulatory brakes fail, uncontrolled cellular proliferation and systemic low-grade inflammation ensue, linking outright nutritional iodine depletion to a broad spectrum of modern degenerative pathologies.
What the Mainstream Narrative Omits
Public health discourse in the United Kingdom continues to operate on a reductive paradigm, framing iodine solely through the narrow lens of endemic goitre prevention and neonatal cretinism. This orthodox framework relies on outdated epidemiological assumptions, asserting that the universal salt iodisation programmes of the twentieth century successfully resolved population-level iodine deficiency. However, clinical investigations and urinary biomonitoring data published in journals such as The Lancet and the British Journal of Nutrition reveal a starkly different biochemical reality. Mainstream dietary guidelines persistently omit the profound shift in human exposure to competitive halogen analogues over the past half-century, a phenomenon that has functionally rendered standard recommended nutrient intakes (RNIs) inadequate for maintaining optimal systemic homeostasis.
The contemporary British diet is characterised by a heavy burden of endocrine disruptors—specifically bromine, fluorine, and chlorine—which share identical chemical properties and ionic charge with iodine. Because the sodium-iodide symporter (NIS), a glycoprotein located primarily in the basolateral membrane of the thyroid follicular cell, exhibits competitive kinetics, these xenobiotic halides act as potent competitive inhibitors. When an individual consumes a diet rich in brominated flame retardants (found in modern agriculture and upholstery), fluoridated municipal water, and chlorinated compounds, these elements competitively displace iodine at the cellular receptor level. Consequently, even individuals whose urinary iodine concentrations technically clear the outdated threshold of sufficiency may still experience functional cellular deficiency. The mainstream narrative systematically ignores this biochemical antagonism, failing to recognise that the mere presence of iodine in the serum does not equate to intracellular bioavailability or adequate saturation of target tissues.
Furthermore, official dietary advisories remain anchored to a single biological target: the thyroid gland's synthesis of thyroxine ($T4$) and triiodothyronine ($T3$). This ignores a vast body of physiological literature demonstrating that the NIS is expressed across a wide array of extrathyroidal tissues, including the mammary glands, gastric mucosa, choroid plexus, thymus, and salivary glands. Each of these systems maintains distinct, high-volume requirements for iodine that far exceed the threshold needed to merely prevent overt hypothyroidism. For instance, mammary gland iodine uptake is essential for targeted antioxidant defense and the modulation of apoptosis in ductal epithelial cells, a mechanism extensively documented in oncological and endocrinological research. By evaluating iodine sufficiency solely through the narrow metric of thyroid-stimulating hormone (TSH) serum assays, institutional medicine overlooks the systemic desaturation of these secondary reservoirs. At INNERSTANDIN, our synthesis of modern biological data underscores that true nutritional optimisation requires an appreciation of these multi-system kinetics, moving far beyond the simplistic dogma of historical deficiency models.
The UK Context
The contemporary British population faces a quiet yet profound micronutrient crisis, one that is systematically eroding endocrine homeostasis across generations. Historically, the United Kingdom was designated as iodine-sufficient, but over the past three decades, epidemiological shifts have reclassified the nation as mildly to moderately iodine-deficient. Landmark studies, including the UK Iodine Group surveys and data published in The Lancet, have consistently revealed that schoolgirls and women of childbearing age in the UK exhibit urinary iodine concentrations that sit below the World Health Organization's optimal thresholds. This insidious depletion is not driven by acute starvation, but by profound shifts in modern British dietary patterns, industrial food processing, and evolving agricultural paradigms.
At the physiological level, this chronic inadequacy compromises the biosynthesis of thyroxine ($\text{T}4$) and triiodothyronine ($\text{T}3$), forcing the thyroid gland into compensatory hyperplastic states. The molecular mechanism relies on the sodium-iodide symporter (NIS) located on the basolateral membrane of thyrocytes, which actively transports iodide into the follicular lumen. In an iodine-depleted milieu, the intrathyroidal pool diminishes, impairing the organification of thyroglobulin by thyroid peroxidase (TPO). For the UK populace, this biochemical bottleneck yields subclinical hypothyroidism, characterised by sluggish basal metabolic rates, impaired neurocognitive development in neonates, and widespread systemic fatigue.
The aetiology of this depletion is multifaceted and deeply entrenched in modern food culture. Unlike many industrialised nations, the UK lacks a mandatory national salt iodisation programme, leaving public iodine status vulnerable to commercial shifts. Compounding this, the British diet has seen a marked reduction in dairy consumption—traditionally the primary vector for dietary iodine in the UK, attributable to iodine-containing sanitisers used in the dairy industry and winter feed supplements. Concurrently, the pervasive rise of plant-based milk alternatives, which are rarely fortified with adequate bioavailable iodine, accelerates this deficit. Furthermore, the modern British diet is laden with dietary goitrogens, such as perchlorate, thiocyanate, and isothiocyanates found in processed foods and certain cruciferous vegetables, which competitively inhibit the NIS and exacerbate systemic iodine wasting.
Here at INNERSTANDIN, we recognise that addressing this systemic depletion requires looking beyond outdated RDA metrics. Without urgent public health interventions and a paradigm shift in how we monitor trace mineral status, the UK population will continue to navigate an invisible wave of neurodevelopmental and metabolic compromise, driven entirely by the systematic erosion of our nutritional foundation.
Protective Measures and Recovery Protocols
Reversing systemic iodine depletion requires moving beyond rudimentary RDA targets and addressing the biochemical complexities of cellular uptake, enzymatic activation, and halogen antagonism. In the UK, where iodine status has declined markedly due to shifting dietary patterns—specifically the reduction in dairy consumption and the widespread replacement of iodine-based steriliers with chlorine and peracetic acid in the commercial dairy industry—restoration protocols demand a rigorous, multi-tiered biological strategy.
The primary clinical objective is not merely saturating the thyroid gland, but mitigating competitive inhibition at the sodium-iodide symporter (NIS). Bromide, fluoride, and perchlorate share structural homology with iodide and act as potent competitive antagonists at the basolateral membrane of thyrocytes, as well as at extrathyroidal NIS-expressing tissues such as gastric mucosa, salivary glands, and lactating mammary tissue. Therefore, recovery protocols must first prioritise the clearance of these goitrogenic halides. Hydration strategies combined with adequate magnesium and selenium status facilitate renal excretion of displaced halides. Selenium is particularly critical; it serves as an essential cofactor for glutathione peroxidase and iodothyronine deiodinases (Types I, II, and III). Unchecked iodine repletion in the presence of selenium deficiency can exacerbate autoimmune thyroiditis by increasing oxidative stress within the thyrocyte via uncoupled hydrogen peroxide generation. Clinical data from PubMed-indexed endocrinology literature underscores that glutathione homeostasis must be established prior to, or concurrently with, aggressive iodine loading.
For targeted recovery, physiological repletion should utilise balanced molecular matrices rather than supratherapeutic inorganic boluses, which can trigger the acute Wolff-Chaikoff effect—a transient inhibition of organification. Gradual titration using multi-compound formulas containing both molecular iodine ($I2$) and iodide ($I^-$) mirrors evolutionary dietary exposure and satisfies the distinct tissue-specific preferences of the human body. While the thyroid gland preferentially utilises iodide for thyroxine ($T4$) and triiodothyronine ($T_3$) synthesis, breast tissue, prostate epithelium, and gastric mucosa exhibit a higher affinity for molecular iodine, which exerts localized apoptotic and antioxidant regulatory effects via iodolipid formation.
Furthermore, co-factor optimisation must include vitamin A, zinc, and iron, all of which modulate thyroid transcription factors and receptor sensitivity. Iron deficiency directly impairs thyroid peroxidase (TPO) hemoprotein activity, rendering iodine supplementation futile if anemia or subclinical iron depletion remains unaddressed. At INNERSTANDIN, our synthesis of contemporary nutritional toxicology indicates that true biological recovery from modern iodine depletion necessitates an integrated systems-biology approach: clearing halide competitors, supporting antioxidant defense systems via selenium and glutathione, and supplying bioavailable, multi-speciated iodine to restore systemic saturation across all NIS-dependent tissues.
Summary: Key Takeaways
Iodine homeostasis remains a foundational yet critically compromised pillar of human endocrinology, directly dictating basal metabolic rate, neurodevelopmental trajectory, and systemic oxidoreductase balance. As evidenced by recent biomonitoring data from the UK, including the rolling National Diet and Nutrition Survey (NDNS), covert iodine insufficiency has re-emerged as a silent public health crisis. This systemic depletion is driven by the displacement of traditional iodised salt, the widespread adoption of industrial processed foods lacking marine minerals, and the escalating ingestion of environmental halogen antagonists like fluoride, bromide, and perchlorate—all of which competitively inhibit the sodium-iodide symporter (NIS). At the cellular level, inadequate intrathyroidal iodine impairs thyroglobulin iodination, severely suppressing the synthesis of bioactive triiodothyronine ($\text{T}3$) and thyroxine ($\text{T}4$). Beyond thyroidal tissue, extra-thyroidal NIS expression in gastric mucosa, lactating mammary glands, and the central nervous system underscores the broader physiological fallout of deficiency, precipitating mitochondrial dysfunction, heightened systemic inflammation, and cognitive blunting. Through the rigorous lens of peer-reviewed nutritional science, INNERSTANDIN asserts that restoring optimal iodine status is not merely a strategy for euthyroidism, but an essential clinical intervention required to counteract modern environmental toxicity and metabolic downregulation.
This article is provided for informational and educational purposes only. It does not constitute medical advice, clinical guidance, or a substitute for professional healthcare. Information reflects cited research at time of publication. Always consult a qualified healthcare professional before acting on any health information.
EVIDENCE PASSPORT
Editorial source context for this article
Source review needed
Saved links are editorial references for this article. They may support specific claims rather than every sentence. Open and assess each source in context. This passport does not independently verify them.
Editorial context
A complete editorial reading has not been recorded for this article, and no source links are saved on its record.
Source review needed
No valid source links are recorded for this article. Supplementary research, where available, is listed separately below.
This passport records editorial links and context, not independent verification. Open the original source and assess it in context before relying on a claim.
Medical Disclaimer
The information in this article is for educational purposes only and does not constitute medical advice, diagnosis, or treatment. Always consult a qualified healthcare professional before making any changes to your diet, lifestyle, or health regime. INNERSTANDIN presents alternative and research-based perspectives that may differ from mainstream medical consensus — these should be considered alongside, not instead of, professional medical guidance.
Read Full DisclaimerContinue the thread
Keep this question moving.
Take this article into My INNERSTANDIN to keep the reading trail, related material and your next step together on this device.
Explore this in the Body Map
Explore related body structures and their educational pages in the interactive Body Map.
Dig deeper in the Library
Free, longform PDF volumes that go beyond headlines into mechanisms and references.
RABBIT HOLE
Follow the biological thread deeper