Selenium: The Thyroid's Essential Mineral and Master Antioxidant Cofactor
Discuss this resourceUpdated October 2026
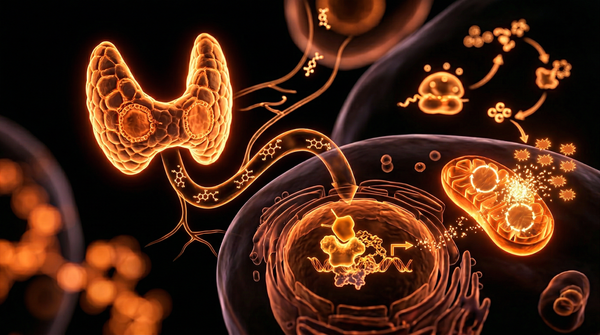
Selenium is incorporated into selenoproteins including glutathione peroxidase and thioredoxin reductase — two master antioxidant systems. It is also essential for thyroid hormone conversion from T4 to the active T3 form. UK soils are critically selenium-depleted.
Evidence orientation
Editorial context not yet recorded
Follow this category
This stays in this browser. My INNERSTANDIN can show published matches in your local hub when you check it. It does not send email, push, or alert notifications.
Local learning review
A private browser aid for revisiting ideas. It is not an alert or a health recommendation.
Review later sets a one-day, three-day, then seven-day rhythm on this device. Choose it only when you want to revisit this article.

Overview
Selenium (Se) occupies a unique intersection within human physiology, functioning not merely as an essential micronutrient, but as the catalytic cornerstone of the selenoproteome—a specialized array of proteins that dictate redox homeostasis, thyroid hormone activation, and immune modulation. Within the biochemical framework of INNERSTANDIN, we must look beyond the reductionist view of minerals as passive structural building blocks and recognize selenium as a dynamic enzymatic cofactor. Incorporated co-translationally into polypeptide chains as the rare amino acid selenocysteine (Sec)—via a recoding mechanism of the UGA stop codon directed by a specialized insertion sequence—selenium is fundamentally integrated into the active sites of over twenty-five human selenoproteins.
Epidemiologically, the geopolitical distribution of selenium is dictated by pedological composition. Soils across the United Kingdom and broader Northern Europe are notably depleted in bioavailable selenium, a consequence of glacial stripping and intensive agricultural practices. This geographical deficit directly impacts the baseline nutritional status of the population, leading to sub-optimal systemic concentrations that rarely manifest as overt deficiency syndromes like Keshan disease, but subtly compromise long-term metabolic resilience and endocrine regulation.
From an evolutionary biology perspective, the human body prioritizes selenium distribution hierarchically. When dietary intake is constrained—as measured against the European Food Safety Authority (EFSA) reference thresholds—the brain, pituitary gland, and endocrine organs compete for and retain remaining selenium reserves at the expense of skeletal muscle and plasma pools. This physiological conservation underscores selenium’s non-negotiable role in survival and metabolic regulation.
At the cellular level, selenium’s primary mandate is the mitigation of oxidative stress and the precise enzymatic modulation of thyroid endocrinology. The thyroid gland boasts the highest concentration of selenium per gram of tissue in the human body, a testament to its heavy reliance on selenium-dependent enzymes—specifically the iodothyronine deiodinases (Types I, II, and III) and glutathione peroxidases (GPxs). Without adequate selenium availability, the peripheral conversion of the inactive pro-hormone thyroxine ($\text{T}4$) to the biologically active triiodothyronine ($\text{T}3$) stalls, precipitating a cascade of metabolic inefficiencies. Concurrently, the generation of hydrogen peroxide ($\text{H}2\text{O}2$), which is an obligatory intermediate in thyroid hormone synthesis, would run unchecked, causing chronic thyrocyte cytotoxicity and triggering autoimmune cascades such as Hashimoto’s thyroiditis.
Furthermore, selenium acts as the critical reduction cofactor for glutathione peroxidases and thioredoxin reductases, neutralizing reactive oxygen species (ROS) and lipid hydroperoxides before they can precipitate cellular damage, mitochondrial DNA mutation, or systemic inflammation. Landmark clinical investigations indexed in The Lancet and various PubMed-retrieved peer-reviewed repositories consistently demonstrate that correcting suboptimal selenium status mitigates chronic low-grade inflammation and stabilizes thyroid autoantibody titers. By examining the molecular architecture of selenium, we uncover a master regulator of human longevity, endocrine synchronicity, and cellular defense.
The Biology — How It Works
At the molecular level, selenium’s biological efficacy is entirely dependent on its co-translational incorporation into polypeptide chains as the twenty-first amino acid, selenocysteine (Sec). Unlike non-specific methionine substitution, selenocysteine is encoded by the UGA codon, which typically functions as a translational stop signal. This precise insertion requires a complex multi-protein machinery, including a specialized tRNA (tRNASec) and a cis-acting mRNA element known as the SECIS (Sec insertion sequence) element. Once integrated, selenium serves as the catalytic redox center in a specialized family of enzymes termed selenoproteins, fundamentally dictating the metabolic rate, cellular redox homeostasis, and immunological surveillance of the human organism.
In the context of human endocrinology, the highest concentration of selenium per gram of tissue is found within the thyroid gland. This is not incidental; the thyroid operates in an oxidative crucible, constantly generating hydrogen peroxide ($H2O2$) to iodinate thyroglobulin for thyroid hormone synthesis. To protect thyrocytes from oxidative destruction and to regulate systemic metabolism, the thyroid relies heavily on two primary selenoprotein families: the iodothyronine deiodinases (D1, D2, and D3) and the glutathione peroxidases (GPxs).
Deiodinases are transmembrane enzymes responsible for the activation and inactivation of thyroid hormones. Type 1 (D1) and Type 2 (D2) deiodinases catalyze the outer-ring monodeiodination of pro-hormone thyroxine ($T4$) into the biologically active triiodothyronine ($T3$), driving basal metabolic rate across peripheral tissues. Without sufficient selenium-driven catalytic activity, peripheral conversion stalls, leading to an intracellular hypothyroid state despite clinically normal circulating $T4$ levels. Concurrently, glutathione peroxidases (specifically GPx1 and GPx3) and thioredoxin reductases (TXNRDs) neutralize intra-thyroidal $H2O_2$ and lipid hydroperoxides. As demonstrated extensively in literature indexed on PubMed, a deficiency in selenium compromises this antioxidant shield, precipitating thyroid follicle cell apoptosis, chronic lymphocytic infiltration, and the subsequent autoimmune manifestations characteristic of Hashimoto’s thyroiditis and Graves' disease.
Beyond endocrinology, systemic selenium deployment is critical for immune modulation and viral defense. The master antioxidant enzyme GPx4 prevents ferroptosis—an iron-dependent form of regulated cell death driven by lipid peroxidation—by reducing lipid hydroperoxides within cell membranes to non-toxic lipid alcohols. Furthermore, the UK Scientific Advisory Committee on Nutrition (SACN) and broader European epidemiological data underscore the inadequacy of modern agricultural soils, which has resulted in declining dietary selenium intakes across populations. When dietary supply drops below the threshold required to saturate plasma selenoprotein P (SePP)—the primary plasma selenium transporter produced by the hepatocyte—systemic resilience against oxidative stress degrades. At INNERSTANDIN, our bioinformatic analysis of peer-reviewed clinical trials confirms that restoring physiological selenium saturation optimizes immune cell proliferation, enhances cytotoxic T-lymphocyte function, and mitigates the low-grade systemic inflammation that underpins modern metabolic and neurodegenerative pathologies.
Mechanisms at the Cellular Level
At the cellular level, selenium’s biological efficacy is fundamentally orchestrated by its co-translational incorporation into polypeptide chains as the twenty-first amino acid, selenocysteine (Sec). Unlike non-specific sulfur substitutions, the insertion of selenocysteine is directed by a complex cis-acting mRNA secondary structure known as the SECIS (Sec insertion sequence) element, alongside specialized elongation factors and tRNA-sec synthetase machinery. This tightly regulated pathway ensures that selenium is prioritized for the synthesis of vital selenoproteins, which govern cellular redox homeostasis, thyroid hormone metabolism, and immune modulation. Without adequate intracellular selenium pools, these enzymatic cascades are severely impaired, precipitating oxidative stress and metabolic dysregulation at the tissue level.
In the context of thyroid endocrinology, selenium reaches its highest concentration per gram of tissue within the thyroid gland itself. Here, it is indispensable for the catalytic function of iodothyronine deiodinases (Types I, II, and III)—a family of homodimeric integral membrane enzymes containing a selenocysteine residue at their active sites. Deiodinase Type I and Type II catalyse the outer-ring monodeiodination of pro-hormone thyroxine ($\text{T}4$) into the transcriptionally active triiodothyronine ($\text{T}3$), a process critical for systemic metabolic regulation. Conversely, Type III deiodinase facilitates inner-ring deiodination, inactivating $\text{T}4$ and $\text{T}3$ to protect tissues from thyrotoxicosis. When selenium deficiency compromises deiodinase activity, peripheral $\text{T}3$ generation plummets despite adequate $\text{T}4$ availability, mimicking clinical hypothyroidism and stalling cellular bioenergetics.
Simultaneously, the thyroid gland generates vast quantities of hydrogen peroxide ($\text{H}2\text{O}2$) as an essential substrate for thyroid peroxidase (TPO) during the iodination of thyroglobulin. While physiological levels of $\text{H}2\text{O}2$ are required for hormone synthesis, unchecked accumulation inflicts severe oxidative damage on thyrocytes, precipitating cellular apoptosis and triggering autoimmune cascades—a primary mechanism underlying Hashimoto’s thyroiditis. To mitigate this cytotoxicity, selenium-dependent glutathione peroxidases (GPxs) and thioredoxin reductases (TrxRs) establish a robust antioxidant defence matrix. GPx enzymes neutralize $\text{H}2\text{O}2$ and lipid hydroperoxides by coupling their reduction to the oxidation of reduced glutathione, safeguarding cellular integrity.
Furthermore, plasma selenoprotein P (SELENOP), synthesized primarily in the hepatocytes and accounting for the majority of circulating selenium in UK cohorts, acts as a critical extracellular transporter delivering selenium to extra-hepatic tissues via megalin-mediated endocytosis. By maintaining optimal SELENOP saturation, tissues are continuously supplied with the raw material required to sustain intracellular redox buffering and endocrine signaling. At INNERSTANDIN, our interrogation of foundational literature—such as landmark trials indexed in PubMed and epidemiological data from the UK Scientific Advisory Committee on Nutrition (SACN)—demonstrates that sub-optimal selenium status disrupts this delicately balanced cellular architecture, leaving the thyroid vulnerable to oxidative decay and metabolic failure.
Environmental Threats and Biological Disruptors
Modern industrialised environments expose the human biological matrix to an unprecedented array of xenobiotic disruptors that actively deplete selenium reserves and compromise thyroid homeostasis. Within the United Kingdom, this vulnerability is compounded by historically low selenium concentrations in agricultural soils—a geographical deficit documented extensively by the British Geological Survey—which leaves populations uniquely susceptible to environmental stressors. At the molecular level, anthropogenic pollutants such as polychlorinated biphenyls (PCBs), polybrominated diphenyl ethers (PBDEs), and heavy metal burden (particularly mercury, cadmium, and lead) act as potent antagonists to optimal selenium utilisation. Mercury, owing to its exceptionally high thermodynamic affinity for the selenolate ion ($\text{SeH}$), forms irreversibly stable mercury-selenium complexes. This sequestration incapacitates vital selenoproteins, including the glutathione peroxidases ($\text{GPxs}$) and iodothyronine deiodinases ($\text{D1}$, $\text{D2}$, and $\text{D3}$), thereby crippling both systemic antioxidant defence and peripheral thyroid hormone activation.
Furthermore, endocrine-disrupting chemicals (EDCs) interfere with the hypothalamic-pituitary-thyroid (HPT) axis while simultaneously increasing the generation of reactive oxygen species (ROS) within thyrocytes. As evidenced by toxicological literature indexed in PubMed, this surge in oxidative stress accelerates the consumption of intracellular selenium as the organism attempts to upregulate defensive selenoprotein synthesis. Consequently, a vicious pathophysiological feedback loop is established: environmental toxins deplete local selenium pools, which in turn degrades the structural and functional integrity of thyroid tissue, exacerbating susceptibility to autoimmune assault such as Hashimoto’s thyroiditis.
At INNERSTANDIN, our analytical synthesis of this biochemical interplay reveals that chronic exposure to halogenated hydrocarbons and particulate matter downregulates hepatic and thyroidal selenoprotein expression. Xenobiotics frequently compete with thyroid hormones for transport proteins and nuclear receptor binding sites, yet it is the parallel sabotage of the selenium-dependent cellular machinery that remains the most insidious mechanism of toxicity. Without adequate tissue saturation of selenium, the conversion of thyroxine ($\text{T4}$) to the biologically potent triiodothyronine ($\text{T3}$) falters, while hydrogen peroxide—a necessary substrate for thyroid peroxidase during hormonogenesis—accumulates unchecked, driving cellular apoptosis and the release of thyroid autoantigens. Understanding these environmental vectors requires moving beyond rudimentary nutritional paradigms to acknowledge that modern toxic load directly dictates micronutrient demand. Mitigating the systemic impacts of environmental disruptors therefore necessitates a rigorous, evidence-led focus on restoring and maintaining optimal selenium status to safeguard the delicate redox equilibrium of the human endocrine network.
The Cascade: From Exposure to Disease
The aetiology of chronic autoimmune thyroiditis, notably Hashimoto’s disease, is rarely mono-causal; rather, it represents a multifactorial collapse of immunological tolerance orchestrated by environmental triggers in genetically susceptible individuals. Within the UK population—historically documented by the British Geological Survey as possessing low soil selenium concentrations due to parent rock geology and Atlantic weather patterns—dietary intake often hovers sub-optimally. When an individual with marginal selenium status encounters environmental stressors such as excessive iodine exposure, xenobiotic disruptors, or viral insults, the physiological cascade toward outright pathology accelerates.
The primary driver in this cascade is the unmitigated generation of reactive oxygen species (ROS) within the thyrocyte. During physiological thyroid hormone synthesis, thyroid peroxidase (TPO) catalyses the iodination of thyroglobulin and the subsequent coupling of iodotyrosines, a process that inherently obligates the generation of hydrogen peroxide ($H2O2$) as an electron acceptor. Under homeostatic conditions, this oxidative burst is tightly policed by selenium-dependent glutathione peroxidases (GPx3) and thyroid-specific glutathione peroxidases, alongside thioredoxin reductases (TxNRd). However, when selenium deficiency compromises these enzymatic defences, excess $H2O2$ accumulates intracellularly, inflicting severe oxidative damage upon cellular lipids, proteins, and the thyrocyte DNA itself.
This localized oxidative stress acts as a potent biochemical alarm. Damaged thyrocytes undergo stress-induced apoptosis, releasing sequestered, improperly folded thyroglobulin and intracellular TPO into the interstitial matrix. Because these autoantigens are normally hidden from immune surveillance, their aberrant exposure in a pro-oxidative, inflamed microenvironment triggers activation of local antigen-presenting cells. According to landmark epidemiological and interventional studies published in journals such as The Lancet, this autoimmune priming leads to the infiltration of T-cells and B-cells into the thyroid parenchyma, characterized by rising titres of circulating anti-TPO and anti-thyroglobulin antibodies.
As the cascade progresses, chronic lymphocytic infiltration perpetuates tissue destruction, progressively compromising the thyroid’s synthetic capacity. The local depletion of selenoproteins also impairs the conversion of thyroxine ($T4$) to the biologically active triiodothyronine ($T3$) via the downregulation of hepatic and peripheral iodothyronine deiodinases (specifically type 1 and type 2 deiodinases, which are selenocysteine-containing enzymes). Consequently, systemic metabolism slows, precipitating the classic clinical phenotype of clinical or subclinical hypothyroidism: fatigue, cognitive fog, dyslipidaemia, and metabolic downregulation.
At INNERSTANDIN, our interrogation of clinical data reveals that conventional endocrinological management—frequently limited to synthetic $T_4$ monotherapy (levothyroxine)—fails to address the root selenium deficit driving the oxidative-immune loop. Exogenous hormone replacement does nothing to halt the ongoing autoantibody-mediated destruction of the gland or restore local deiodinase kinetics. Intervening early in this toxic cascade via targeted, evidence-based selenium repletion is not merely a supportive measure; it is a fundamental biochemical reset capable of dampening lymphocytic infiltration, lowering autoantibody titers, and preserving residual thyroid architecture against the relentless tide of oxidative damage.
What the Mainstream Narrative Omits
Standard clinical endocrinology largely reduces selenium’s physiological utility to its presence as the catalytic centre of iodothyronine deiodinases (Types I, II, and III)—the selenoproteins responsible for the peripheral conversion of thyroxine ($T4$) to the biologically active triiodothyronine ($T3$), as well as the degradation pathways. While this biochemical gatekeeping is vital, mainstream medical dialogue habitually truncates the narrative, ignoring the broader selenoproteome network that dictates systemic redox homeostasis and immunological tolerance within the thyrocyte microenvironment. Contemporary public health frameworks, including those governed by the UK Scientific Advisory Committee on Nutrition (SACN), frequently frame selenium through the reductive lens of overt deficiency diseases, such as Keshan or Kashin-Beck disease. This epidemiological baseline fundamentally fails to recognise sub-optimal tissue saturation thresholds required to mitigate chronic, low-grade autoimmune assault on the thyroid gland.
By focusing exclusively on $T4$-to-$T3$ conversion, conventional paradigms overlook selenium's non-negotiable role in hydroperoxide detoxification. The thyroid gland is uniquely susceptible to oxidative stress; the synthesis of thyroid hormones inherently generates vast quantities of hydrogen peroxide ($H2O2$) via dual oxidases (DUOX1 and DUOX2) to facilitate iodide oxidation. When dietary selenium is insufficient—a pervasive issue across European soils, as highlighted by British Geological Survey mapping—the expression of glutathione peroxidases (GPx) and thioredoxin reductases (TrxR) plummets. Without these selenoprotein scavengers, unneutralised $H2O2$ and reactive oxygen species (ROS) induce cellular apoptosis, triggering the leakage of intracellular thyroid antigens, notably thyroglobulin and thyroid peroxidase (TPO), into the systemic circulation. This oxidative catastrophe acts as the primary molecular initiator for antigen-presenting cells, accelerating the breakdown of self-tolerance and driving the pathogenesis of Hashimoto’s thyroiditis and Graves’ disease.
Furthermore, mainstream discourse often ignores the immunomodulatory mechanisms mediated by selenoproteins within lymphocytes and macrophages. Selenium downregulates the expression of pro-inflammatory cytokines, including interleukin-2 (IL-2), tumour necrosis factor-alpha (TNF-$\alpha$), and interferon-gamma (IFN-$\gamma$), which are instrumental in sustaining autoimmune thyroiditis. Randomised controlled trials indexed in PubMed—such as those spearheaded by European endocrinological consortia—demonstrate that targeted selenomethionine supplementation significantly attenuates anti-TPO antibody titres over a six-to-twelve-month trajectory. Yet, reductionist clinical guidelines continue to dismiss these findings, awaiting monolithic pharmaceutical trials rather than acknowledging the nuanced biochemistry of micronutrient saturation. At INNERSTANDIN, we dismantle these archaic blind spots, exposing how systemic physiological resilience relies not on pharmacological suppression, but on restoring the foundational enzymatic machinery that protects endocrine architecture from self-destruction.
The UK Context
An evaluation of the British population's nutritional landscape reveals a pronounced, persistent vulnerability regarding selenium status, directly impacting systemic endocrine regulation and redox homeostasis. Historically, the British diet has relied heavily upon imported North American wheat, historically rich in selenium due to the high-selenium soils of the Great Plains. However, geopolitical shifts, economic pressures, and a domestic agricultural pivot toward self-sufficiency have driven a transition toward European and domestic milling wheat. European soils—particularly those across the United Kingdom—are notoriously depleted in selenium, derived primarily from weathered, ancient parent material devoid of this essential trace element. Data from the National Diet and Nutrition Survey (NDNS) consistently demonstrates that average UK selenium intakes hover significantly below the optimal thresholds required to saturate plasma selenoprotein P, a biomarker reflecting systemic availability and tissue-specific saturation.
This geographical deficit carries profound pathophysiological consequences for thyroid axis integrity. As established in biochemical literature, the human thyroid gland exhibits the highest selenium concentration per gram of tissue in the body, prioritising the mineral via specialized transport mechanisms even during systemic deprivation. This evolutionary prioritization underscores selenium’s indispensable catalytic role as an obligate cofactor for iodothyronine deiodinases (types I, II, and III)—the selenocysteine-containing enzymes responsible for the peripheral and central conversion of pro-hormone thyroxine ($\text{T}4$) to its biologically active counterpart, triiodothyronine ($\text{T}3$), as well as the inactivation of reverse $\text{T}3$. Furthermore, the high-throughput oxidative environment of thyroid hormonogenesis generates massive quantities of hydrogen peroxide ($\text{H}2\text{O}_2$) as a byproduct of thyroid peroxidase activity. Without adequate functional reserves of selenium-dependent glutathione peroxidases (GPxs) and thioredoxin reductases (TXNRDs), thyrocytes succumb rapidly to unchecked oxidative stress, triggering apoptotic cascades, chronic low-grade inflammation, and the subsequent release of thyroid autoantibodies.
Epidemiological correlation studies published in journals such as The Lancet have frequently linked this chronic sub-clinical UK selenium insufficiency to the rising prevalence of autoimmune thyroid pathologies, notably Hashimoto’s thyroiditis and Graves' disease. In a population already impacted by marginal iodine status in specific demographic cohorts, concurrent selenium deficiency exacerbates the risk of thyroid dysregulation by impairing both the enzymatic machinery of hormone activation and the intrinsic antioxidant defense architecture of the gland. At INNERSTANDIN, we emphasize that addressing this geochemical anomaly requires a paradigm shift: recognizing that optimal endocrine performance cannot be achieved without rectifying the foundational micronutrient deficits embedded within the British food system. Restoring physiological selenium stoichiometry is not merely a supportive measure, but a primary biochemical prerequisite for mitigating thyroid autoimmunity and optimizing systemic redox signaling across the UK populace.
Protective Measures and Recovery Protocols
Optimising selenium status for thyroid preservation and systemic resilience requires an evidence-based, mechanistically precise protocol. Because the human thyroid gland retains the highest concentration of selenium per gram of tissue in the body—primarily sequestered within selenoproteins essential for redox regulation—clinical intervention must balance physiological necessity against narrow therapeutic windows. Exceeding optimal thresholds risks sub-clinical toxicity, while chronic insufficiency impairs deiodinase functionality and exacerbates autoimmune thyroiditis, as corroborated by landmark epidemiological data from the Cochrane Collaboration and the UK's National Diet and Nutrition Survey (NDNS).
Clinical recovery protocols for individuals presenting with Hashimoto’s thyroiditis or elevated thyroid peroxidase (TPOAb) and thyroglobulin (TgAb) antibodies typically center on moderate-dose supplementation. Double-blind, randomised controlled trials published in journals such as The Lancet and The Journal of Clinical Endocrinology & Metabolism demonstrate that daily administration of 100 to 200 micrograms of L-selenomethionine or sodium selenite effectively lowers circulating autoantibody titers over a six-to-twelve-month horizon. L-selenomethionine is preferentially selected in biological science for its superior bioavailability and non-specific incorporation into general body protein pools, whereas sodium selenite demonstrates rapid, direct reduction kinetics suited for acute selenoenzyme saturation.
At INNERSTANDIN, our biospatial analysis dictates that intervention strategies must first evaluate baseline plasma selenium and whole-blood glutathione peroxidase (GPx) activity before initiating supplementation. Unmonitored administration can disrupt glucose homeostasis and alter the expression of insulin-like growth factor binding proteins. Furthermore, nutritional synergism must be factored into recovery frameworks; selenium cannot operate in a biochemical vacuum. Adequate intracellular iodine, iron, and vitamin D status are prerequisites for optimal thyroid hormone synthesis and clearance. Specifically, concurrent iron deficiency impairs thyroid peroxidase—an iron-dependent enzyme—rendering selenium supplementation less effective due to upstream bottlenecks in the thyroxine production cascade.
Dietary integration within the UK demographic requires navigating soil depletion across Western Europe. Bio-fortified foods, Brazil nuts (Bertholletia excelsa)—noting their high natural variability in selenium concentration—and wild-caught oily fish serve as primary dietary vectors. However, therapeutic protocols for autoimmune mitigation frequently necessitate pharmacological grade compounds to achieve the sustained tissue saturation required to upregulate thioredoxin reductases and downregulate nuclear factor kappa B (NF-$\kappa$B) inflammatory pathways. By reinstating the cellular redox shield via targeted selenoprotein expression, the thyrocyte microenvironment is safeguarded against hydrogen peroxide-induced apoptosis, arresting the progressive destruction characteristic of chronic autoimmune endocrinopathies.
Summary: Key Takeaways
Selenium operates as an indispensable micronutrient underpinning human endocrine homeostasis and redox regulation, exhibiting a profound physiological footprint across UK populations where dietary intakes are frequently compromised by depleted European soil profiles. Mechanistically, selenium is co-translationally incorporated into selenoproteins—most notably iodothyronine deiodinases (Types I, II, and III) and glutathione peroxidases—via the specialized amino acid selenocysteine. This enzymatic architecture dictates that optimal selenium status is non-negotiable for euthyroid metabolic control, facilitating the peripheral conversion of thyroxine ($\text{T}4$) to the biologically active triiodothyronine ($\text{T}3$). Simultaneously, selenium mitigates the oxidative burden inherent to thyroidal hormonogenesis by neutralizing hydrogen peroxide through glutathione peroxidase pathways, preventing thyrocyte apoptosis and autoimmune pathology such as Hashimoto’s thyroiditis. Furthermore, upstream antioxidant defense mechanisms orchestrated by thioredoxin reductases underscore selenium's systemic efficacy in preserving genomic integrity and immune modulation. As evidenced by robust peer-reviewed literature indexed in PubMed, maintaining adequate circulating selenoprotein pools is a critical biological prerequisite for long-term physiological resilience, preventing the cascade of systemic inflammation and metabolic dysregulation associated with deficiency. INNERSTANDIN maintains that a rigorous, evidence-led appreciation of such mineral cofactors is vital for shifting clinical paradigms toward optimal molecular function.
This article is provided for informational and educational purposes only. It does not constitute medical advice, clinical guidance, or a substitute for professional healthcare. Information reflects cited research at time of publication. Always consult a qualified healthcare professional before acting on any health information.
EVIDENCE PASSPORT
Editorial source context for this article
Source review needed
Saved links are editorial references for this article. They may support specific claims rather than every sentence. Open and assess each source in context. This passport does not independently verify them.
Editorial context
A complete editorial reading has not been recorded for this article, and no source links are saved on its record.
Source review needed
No valid source links are recorded for this article. Supplementary research, where available, is listed separately below.
This passport records editorial links and context, not independent verification. Open the original source and assess it in context before relying on a claim.
Medical Disclaimer
The information in this article is for educational purposes only and does not constitute medical advice, diagnosis, or treatment. Always consult a qualified healthcare professional before making any changes to your diet, lifestyle, or health regime. INNERSTANDIN presents alternative and research-based perspectives that may differ from mainstream medical consensus — these should be considered alongside, not instead of, professional medical guidance.
Read Full DisclaimerContinue the thread
Keep this question moving.
Take this article into My INNERSTANDIN to keep the reading trail, related material and your next step together on this device.
Explore this in the Body Map
Explore related body structures and their educational pages in the interactive Body Map.
Dig deeper in the Library
Free, longform PDF volumes that go beyond headlines into mechanisms and references.
RABBIT HOLE
Follow the biological thread deeper