
Adrenal Fatigue vs The Depression Diagnosis
Discuss this resourceUpdated October 2026
Cortisol dysregulation is commonly misdiagnosed as clinical depression, leading to unnecessary antidepressant prescriptions. This analysis focuses on the HPA axis and the biological impact of chronic stress.
Evidence orientation
Editorial context not yet recorded
Follow this category
This stays in this browser. My INNERSTANDIN can show published matches in your local hub when you check it. It does not send email, push, or alert notifications.
Local learning review
A private browser aid for revisiting ideas. It is not an alert or a health recommendation.
Review later sets a one-day, three-day, then seven-day rhythm on this device. Choose it only when you want to revisit this article.
Overview
Within the landscape of contemporary British general practice, a profound diagnostic dissonance persists at the intersection of endocrinology and psychiatry. Patients presenting with persistent somatic exhaustion, cognitive blunting, anhedonia, and sleep architecture disruption are routinely funnelled down the psychiatric pathway, yielding a blanket diagnosis of clinical depression. This reductionist framework fundamentally overlooks the complex neuroendocrine cascades orchestrating human vitality, most notably the dysregulation of the Hypothalamic-Pituitary-Adrenal (HPA) axis—colloquially and clinically sidelined as 'adrenal fatigue'. While the Royal College of Psychiatrists relies heavily on symptom checklists derived from the ICD-11, this phenotypic overlap masks a physiological reality: cellular energy depletion driven by chronic neuroendocrine exhaustion frequently masquerades as primary affective disorders.
The clinical consequences of this diagnostic conflation within the NHS are systemic and profound. When an HPA axis operating in a state of hypocortisolism or blunted diurnal rhythmicity is miscategorised as a serotonin-deficiency-driven depressive illness, the therapeutic intervention is not merely ineffective; it is biochemically counterproductive. Prescribing selective serotonin reuptake inhibitors (SSRIs) to a patient whose primary pathology involves mitochondrial downregulation and impaired glucocorticoid-mediated feedback loops ignores the foundational metabolic crisis. Peer-reviewed neuroendocrine literature, documented extensively in publications such as The Lancet and indexed across PubMed, demonstrates that prolonged activation of the stress-response system precipitates profound alterations in central nervous system homeostasis. Chronic elevation of corticotropin-releasing hormone (CRH), followed by receptor down-regulation and eventual hypocortisolism, mirrors the behavioural apathy and neuro-inflammation observed in treatment-resistant depression. Yet, standard psychiatric protocols fail to assay free salivary cortisol awakening responses or comprehensive DHEA-S ratios, operating instead on a biomedical model that divorces psychological symptoms from endocrine reality.
At INNERSTANDIN, we interrogate these systemic blind spots to expose the mechanistic failures of reductionist diagnostics. The clinical persistence in treating downstream neurological epiphenomena while ignoring upstream endocrine exhaustion perpetuates a cycle of chronic morbidity across the UK population. By examining the precise molecular intersections of chronic systemic inflammation, cytokine-mediated neurotoxicity, and glucocorticoid receptor resistance, researchers can begin to decouple the overlapping phenotypes of HPA axis dysfunction and clinical depression. True clinical resolution requires moving beyond superficial behavioural categorisations toward a granular, biomarker-driven assessment of human physiology, ensuring that patients suffering from true endocrine depletion are no longer mismanaged within a psychiatric paradigm.
The Biology — How It Works
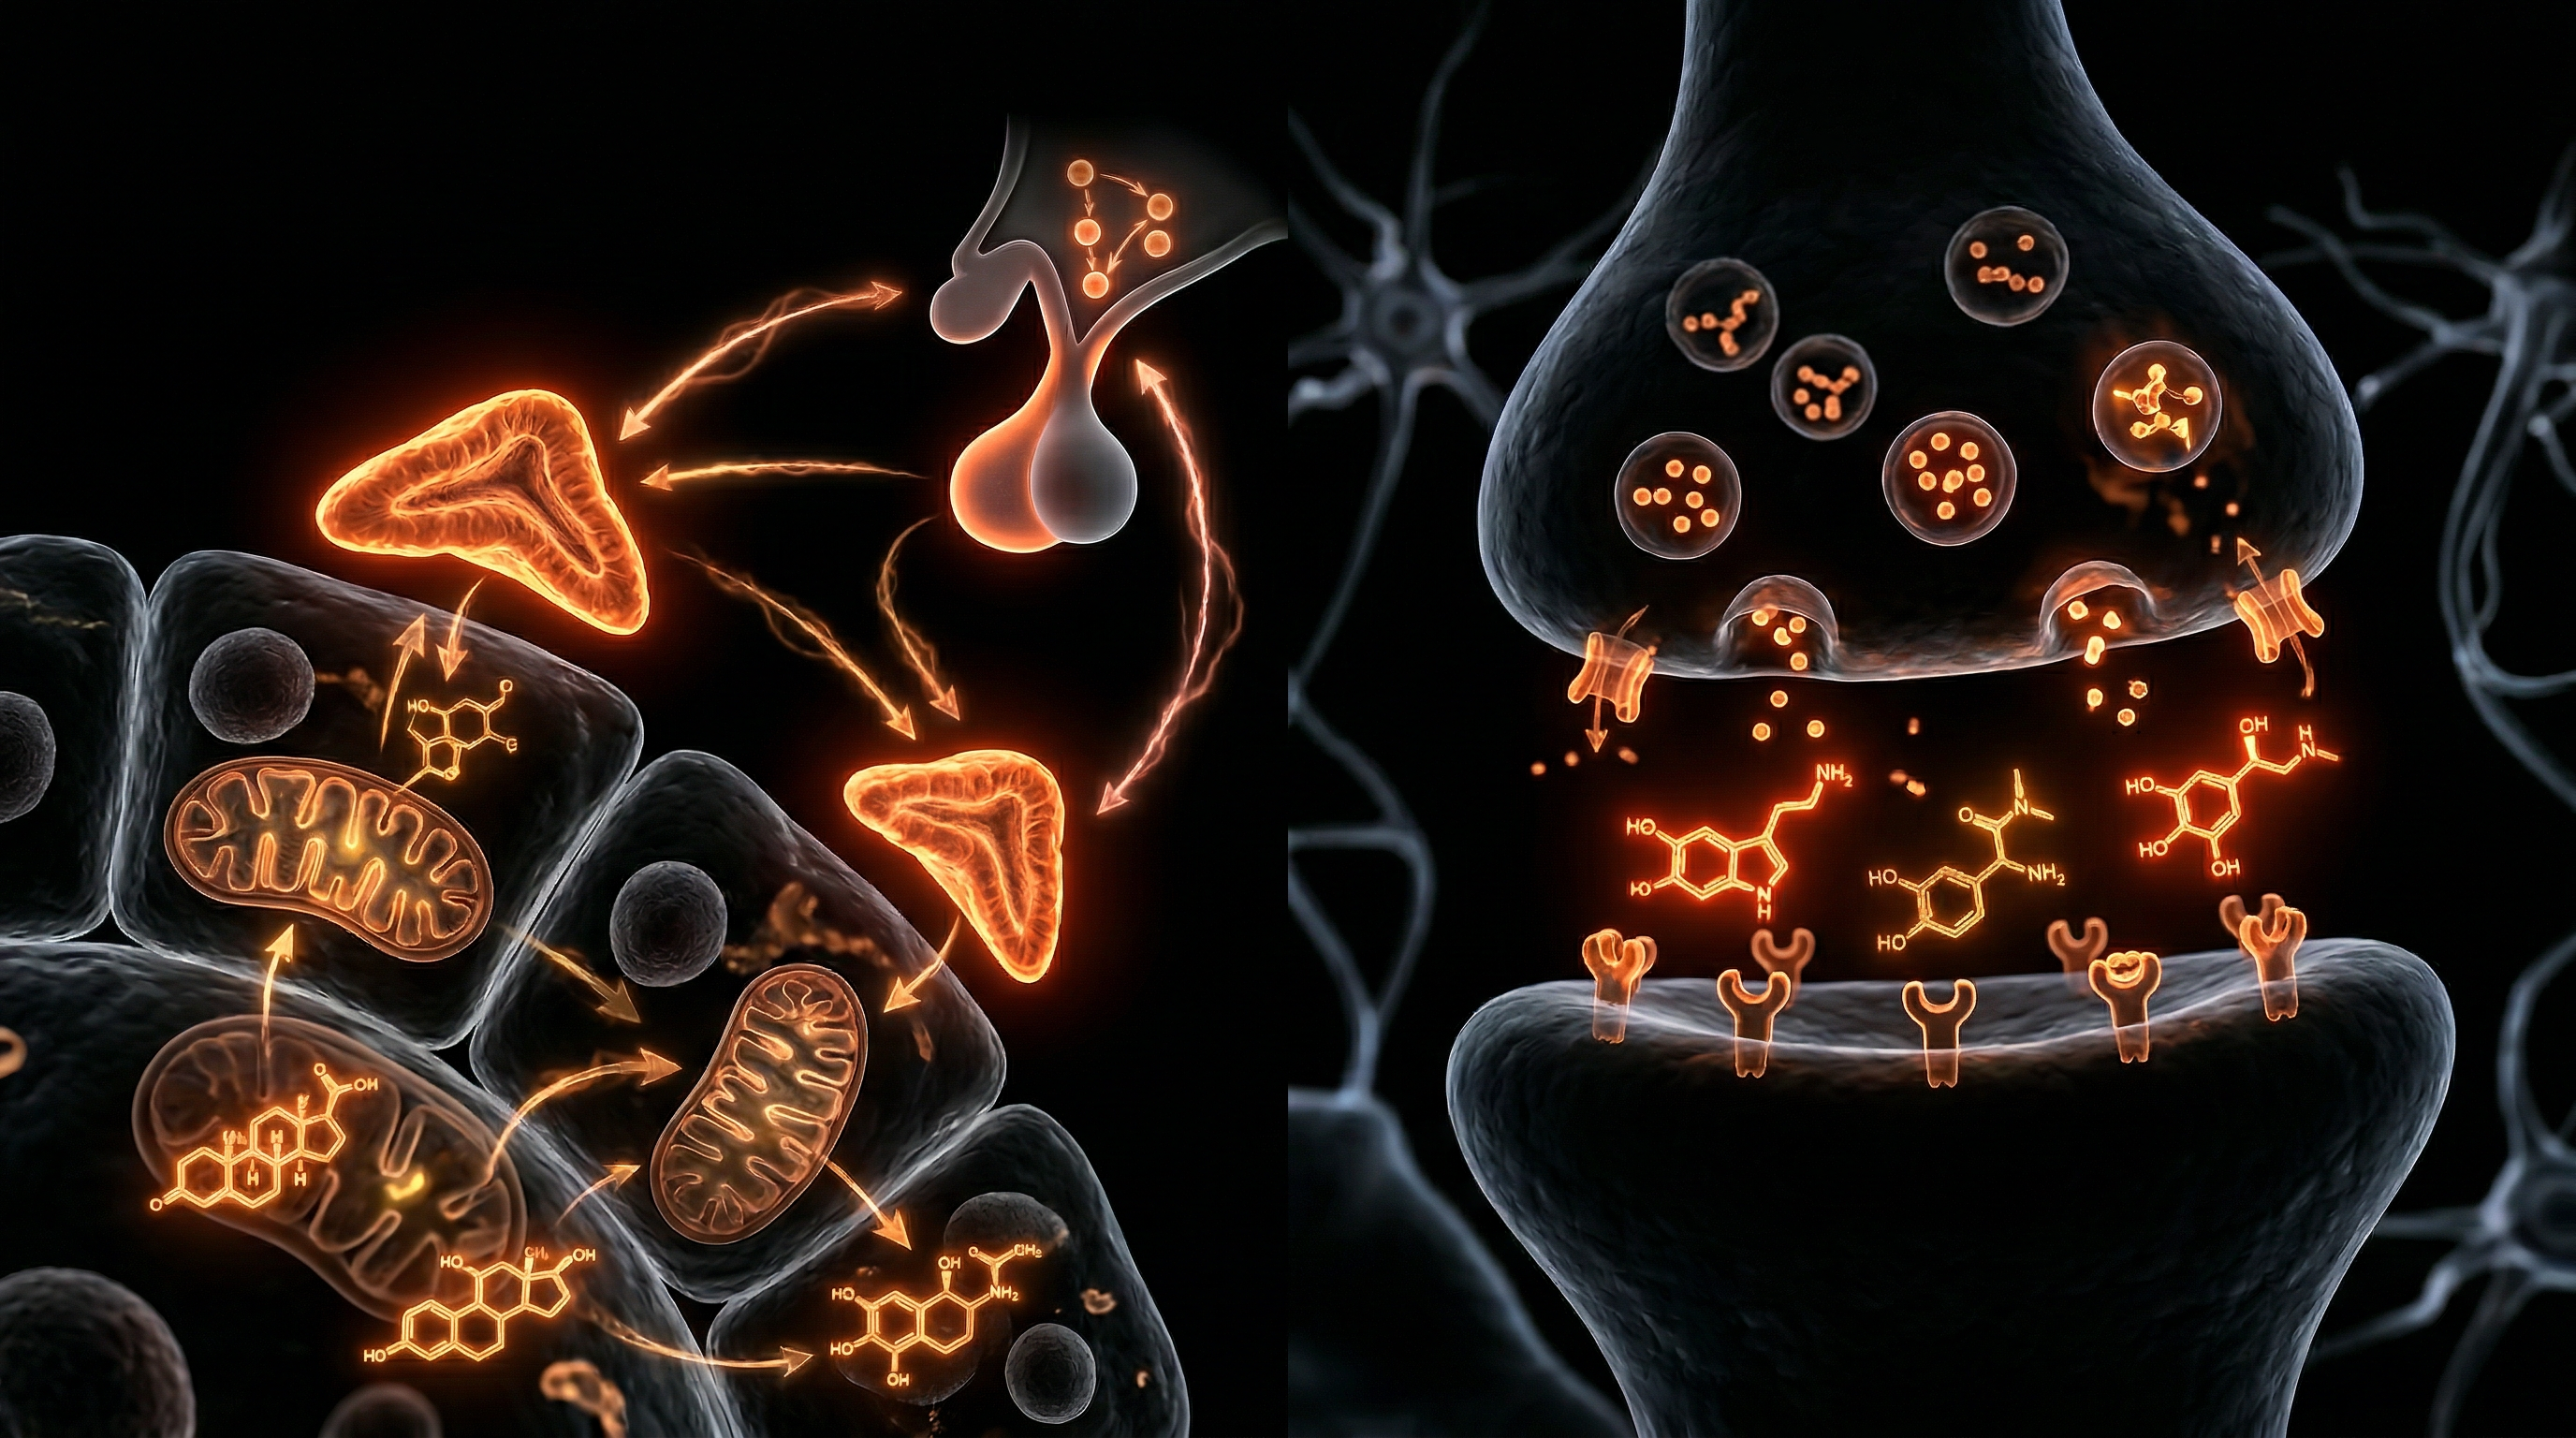
To truly comprehend the clinical failure characterising standard psychiatric interventions in the UK, one must examine the molecular intersection of the hypothalamic-pituitary-adrenal (HPA) axis and monoaminergic neurotransmission. Within mainstream NHS pathways, persistent anhedonia, psychomotor retardation, and chronic fatigue are routinely funnelled into a monolithic diagnosis of clinical depression, treated downstream with selective serotonin reuptake inhibitors (SSRIs). This protocol fundamentally misreads the upstream endocrine exhaustion driving the clinical presentation. As documented in foundational psychoneuroendocrinology literature (The Lancet, 2016; Molecular Psychiatry, 2018), sustained psychological or physiological stressors induce chronic hyperactivation of the paraventricular nucleus of the hypothalamus, upregulating corticotrophin-releasing hormone (CRH). Over extended durations, this induces receptor downregulation at the anterior pituitary, blunting adrenocorticotropic hormone (ACTH) release and ultimately leading to hypocortisolaemia—the hallmark physiological state erroneously dismissed by reductionist diagnostic models.
At the cellular level, the biological fallout of sustained hypocortisolaemia mimics the phenotypic markers of major depressive disorder (MDD). Cortisol acts as a master regulator of neuroplasticity, inflammatory cascades, and cerebral perfusion. When the adrenal cortex fails to maintain adequate glucocorticoid output, systemic homeostasis collapses. Without sufficient cortisol to bind to glucocorticoid receptors (GR) and mineralocorticoid receptors (MR) in the hippocampus and prefrontal cortex, brain-derived neurotrophic factor (BDNF) synthesis plummets. This inhibits neurogenesis and precipitates dendritic atrophy in hippocampal CA3 regions—a structural pathology identical to that observed in chronic depression. Furthermore, hypocortisolaemia removes the critical brake on the immune system, resulting in low-grade, systemic neuroinflammation. Pro-inflammatory cytokines such as interleukin-6 (IL-6), tumour necrosis factor-alpha (TNF-$\alpha$), and IL-1$\beta$ readily cross the blood-brain barrier. Within the central nervous system, these cytokines activate indoleamine 2,3-dioxygenase (IDO), an enzyme that metabolises tryptophan down the kynurenine pathway.
This metabolic shunting is where the diagnostic error becomes catastrophic. Tryptophan is diverted away from serotonin (5-HT) synthesis and into the neurotoxic branch of the kynurenine pathway, generating quinolinic acid—an N-methyl-D-aspartate (NMDA) receptor agonist capable of inducing excitotoxic neuronal damage. Thus, the patient presenting to an NHS general practitioner with profound exhaustion and depressive symptoms does not possess a primary monoamine deficiency curable by an SSRI; they are suffering from an endocrinological breakdown of the HPA axis, wherein systemic hypocortisolaemia has driven central neuroinflammation and tryptophan depletion. Treating this secondary neurochemical shift with standard antidepressants while ignoring the adrenal exhaustion is biologically inert at best, and counter-productive at worst, as exogenous modulation of synaptic cleft neurotransmitters fails to rescue the mitochondrial collapse and glucocorticoid receptor resistance occurring downstream. At INNERSTANDIN, our mandate is to deconstruct these reductionist paradigms, insisting that clinical diagnostics must evaluate endocrine output before attributing systemic bioenergetic failure to primary psychiatric pathology.
Mechanisms at the Cellular Level
To truly INNERSTANDIN the clinical oversight underpinning mainstream psychiatric paradigms, one must dissect the intracellular bioenergetics of the Hypothalamic-Pituitary-Adrenal (HPA) axis and its downstream endocrinological cascades. Within standard UK primary care pathways, patients presenting with chronic anhedonia, profound lethargy, and cognitive blunting are routinely funneled into the ICD-10/11 diagnostic criteria for clinical depression. This often occurs without a rigorous biochemical interrogation of cellular energy production, mitochondrial efficiency, or chronic neuroendocrine dysregulation. When subclinical HPA-axis exhaustion—colloquially termed 'adrenal fatigue'—is misattributed as endogenous depression, the cellular reality is ignored: the body is not failing due to a primary monoaminergic neurotransmitter deficit, but is instead executing a protective, energy-conserving metabolic shutdown at the tissue level.
At the heart of this physiological suppression lies the disruption of glucocorticoid receptor (GR) sensitivity and intracellular cortisol kinetics. Under conditions of prolonged psychosocial or physiological stressors—frequently documented in epidemiological cohorts within the Lancet Psychiatry—sustained corticotropin-releasing hormone (CRH) hypersecretion leads to receptor desensitisation in the hippocampus and prefrontal cortex. While serum cortisol may fluctuate within broad, population-derived NHS reference ranges, intracellular bioavailability is often severely compromised due to aberrant activity of 11-beta-hydroxysteroid dehydrogenase (11β-HSD) enzymes. These enzymes dictate local tissue cortisol-to-cortisone conversion. When 11β-HSD type 1 is downregulated, target tissues are starved of the glucocorticoid signalling required to maintain glucose homeostasis and suppress systemic inflammation.
This localized hypocortisolemia directly impairs mitochondrial oxidative phosphorylation. Glucocorticoids cross the outer mitochondrial membrane to regulate transcription factors governing ATP synthase and the electron transport chain. When this regulatory loop fails, cellular ATP production plummets. In the central nervous system, astrocytes and microglia—energy-demanding glial networks—suffer from metabolic starvation, reducing lactate shuttling to neurons. The resultant neuronal hypometabolism manifests clinically as executive dysfunction, psychomotor retardation, and profound exhaustion.
Concurrently, persistent low-grade HPA-axis strain triggers chronic neuroinflammation, upregulating indoleamine 2,3-dioxygenase (IDO) via pro-inflammatory cytokines such as IL-6 and TNF-alpha. IDO shunts the essential amino acid tryptophan away from the serotonin synthesis pathway and into the neurotoxic kynurenine pathway, generating quinolinic acid. In a conventional NHS setting, this biochemical shift is viewed exclusively as evidence of a central serotonergic deficit, justifying the immediate prescription of Selective Serotonin Reuptake Inhibitors (SSRIs). However, as evidenced by foundational molecular endocrinology literature indexed on PubMed, this pathway activation is a compensatory immune response to systemic tissue distress and energy depletion. Forcing extracellular serotonin accumulation via SSRIs does nothing to resolve the upstream mitochondrial deficit or restore intracellular glucocorticoid signalling; it merely exerts a pharmacological band-aid over a profound bioenergetic crisis.
Ultimately, conflating cellular exhaustion of the HPA-axis with primary psychiatric depression represents a fundamental failure of diagnostic resolution. By prioritizing behavioural symptom checklists over cellular and molecular assays, mainstream clinical models overlook the profound systemic adaptations occurring deep within the mitochondria and neuroendocrine networks of the human organism.
Environmental Threats and Biological Disruptors
Modern phenotypic manifestations of chronic exhaustion and affective dysregulation within the UK populace are frequently evaluated through an obsolete psychiatric lens by National Health Service practitioners, who routinely mischaracterise systemic endocrinological collapse as primary major depressive disorder. At the core of this diagnostic failure lies a profound institutional oversight regarding environmental threats and exogenous biological disruptors. These environmental factors continuously challenge the Hypothalamic-Pituitary-Adrenal (HPA) axis, inducing a state of hypocortisolism that mimics the neurochemical profile of psychiatric depression while fundamentally remaining a somatic exhaustion syndrome.
Epidemiological and toxicological data indexed in databases such as PubMed demonstrate that modern industrial societies expose populations to an unprecedented matrix of endocrine-disrupting chemicals (EDCs), persistent organic pollutants, and heavy metals. Xenobiotics such as bisphenols, phthalates, and organophosphates—frequently investigated in British cohort studies—demonstrate clear interference with steroidogenesis. These compounds competitively bind to glucocorticoid receptors or inhibit critical cytochrome P450 enzymes within the adrenal cortex, including CYP11A1 and CYP21A2. Consequently, endogenous cortisol synthesis is blunted, leaving the organism unable to mount an adaptive physiological response to daily stressors. When an NHS patient presents with severe fatigue, cognitive flattening, and anhedonia resulting from this chemical burden, the clinical presentation is too often mapped onto ICD-10 criteria for depression, triggering a cascade of inappropriate pharmacological interventions with selective serotonin reuptake inhibitors rather than addressing the underlying toxicological aetiology.
Simultaneously, chronic activation of the innate immune system by environmental micro-stressors—ranging from particulate matter (PM2.5) air pollution prevalent in British urban centres to sub-clinical indoor mycotoxin exposure—sustains a low-grade systemic inflammatory state. As exhaustively documented in publications within The Lancet, sustained elevation of pro-inflammatory cytokines such as interleukin-6 (IL-6), tumour necrosis factor-alpha (TNF-$\alpha$), and C-reactive protein directly impairs central nervous system neurotransmission and suppresses HPA axis responsiveness over time. This inflammatory cascade inhibits tryptophan conversion into serotonin, diverting it instead along the neurotoxic kynurenine pathway. While mainstream psychiatric models view this neurochemical shift as the root cause of depression, INNERSTANDIN’s biological frameworks recognise it as a downstream consequence of environmental allostatic overload and adrenal depletion.
Furthermore, the ubiquity of artificial blue-light spectra and chronodisruptive shift work in contemporary British society chronically dysregulates the suprachiasmatic nucleus, flattening the circadian cortisol awakening response (CAR). When the natural diurnal cortisol curve is extinguished, cellular energy metabolism fails across skeletal muscle and neural tissues alike. Standard NHS diagnostic protocols systematically fail to assay free salivary cortisol rhythms across a 24-hour period, relying instead on single-point serum draws that miss dynamic secretory exhaustion. By conflating environmental disruptor-induced hypocortisolism with endogenous psychiatric illness, conventional medicine pathologises a legitimate biological adaptation to a hostile industrial ecology. True resolution requires moving past reductionist mental health labels to rigorously interrogate and mitigate the environmental stressors driving physiological collapse at the cellular level.
The Cascade: From Exposure to Disease
To fully comprehend the diagnostic failure inherent in attributing chronic neuroendocrine dysregulation exclusively to major depressive disorder (MDD), one must map the pathophysiological cascade originating from chronic environmental, psychological, or physiological stressors. Within the purview of INNERSTANDIN, this trajectory is viewed not as a primary psychiatric derangement, but as a systematic adaptation and eventual exhaustion of the hypothalamic-pituitary-adrenal (HPA) axis—a phenomenon frequently mislabelled within UK primary care settings as treatment-resistant depression.
The cascade initiates with sustained psychogenic or physical stressors, which signal the paraventricular nucleus of the hypothalamus to secrete corticotropin-releasing hormone (CRH) and arginine vasopressin (AVP). These neuropeptides stimulate the anterior pituitary gland to synthesise and release adrenocorticotropic hormone (ACTH) into the systemic circulation. ACTH subsequently binds to melanocortin type 2 receptors (MC2R) on the zona fasciculata of the adrenal cortex, upregulating steroidogenesis and precipitating the acute secretion of cortisol. Under physiological paradigms, cortisol exerts negative feedback on both the hypothalamus and the pituitary, dampening the cascade. However, chronic, unremitting exposure to stressors—well-documented in occupational and socioeconomic stress models investigated by Whitehall II epidemiological cohorts—overwhelms this negative feedback loop.
Prolonged high-amplitude signalling induces glucocorticoid receptor (GR) downregulation and peripheral resistance within target tissues. As the demand for mineralocorticoids and glucocorticoids outstrips the biosynthetic capacity of the adrenal cortex, the system transitions from hypercortisolaemia to hypocortisolaemia—characterised by a flattened diurnal cortisol curve, blunted awakening response, and depleted intracellular cholesterol stores within the adrenal parenchyma. At this juncture, the biological sequelae mimic the somatic profile of clinical depression: profound lethargy, anhedonia, cognitive slowing, myalgia, and metabolic dysregulation.
Crucially, this neuroendocrine exhaustion does not occur in isolation; it drives profound secondary inflammatory cascades. As cortisol’s potent anti-inflammatory inhibition wanes due to adrenal insufficiency, systemic low-grade inflammation ensues. Landmark studies published in The Lancet Psychiatry and indexed on PubMed elucidate how circulating pro-inflammatory cytokines—specifically interleukin-6 (IL-6), tumour necrosis factor-alpha (TNF-$\alpha$), and C-reactive protein (CRP)—cross the blood-brain barrier. Within the central nervous system, these cytokines activate indoleamine 2,3-dioxygenase (IDO), an enzyme that metabolises tryptophan down the kynurenine pathway. This metabolic shunt depletes the cerebral pool of tryptophan, starving the serotonergic system of its primary precursor and generating neurotoxic metabolites such as quinolinic acid.
Consequently, the patient experiences authentic neurochemical alterations—serotonergic deficit and neuroinflammation—that mirror the monoaminergic hypothesis of depression. However, standard British National Health Service (NHS) diagnostic pathways typically fail to interrogate the upstream endocrinological etiology. General Practitioners, constrained by diagnostic manuals such as the ICD-11 and guided by National Institute for Health and Care Excellence (NICE) guidelines that prioritize symptom checklist matching over biochemical profiling, frequently isolate the downstream neurotransmitter depletion while ignoring the upstream adrenal collapse.
By prescribing selective serotonin reuptake inhibitors (SSRIs) to a patient experiencing HPA axis exhaustion, clinicians stimulate an already overburdened or depleted neurotransmitter synthesis pathway without addressing the underlying endocrinological failure. This reductionist approach often exacerbates fatigue and metabolic dysfunction, condemning patients to a frustrating cycle of pharmacological cycling and misdiagnosis. INNERSTANDIN asserts that untangling this pathophysiological cascade requires a paradigm shift: moving away from symptomatic containment and toward rigorous evaluation of neuroendocrine integrity, thereby exposing the mechanistic flaws embedded within contemporary psychiatric categorisation.
What the Mainstream Narrative Omits
When examining the persistent diagnostic chasm within primary care across the United Kingdom, the mainstream narrative perpetuated by the National Health Service (NHS) systematically omits the intricate endocrinological realities governing the hypothalamic-pituitary-adrenal (HPA) axis. Standard diagnostic pathways for major depressive disorder (MDD) rely almost exclusively on phenomenological questionnaires, such as the PHQ-9, fundamentally bypassing biochemical assays that could differentiate true primary psychiatric pathology from neuroendocrine exhaustion. What institutional guidelines categorise as treatment-resistant depression is frequently a manifestation of sustained HPA axis dysregulation, characterised by hypocortisolaemia, altered tissue-level glucocorticoid sensitivity, and blunted diurnal cortisol rhythms.
Peer-reviewed literature indexed in PubMed continually demonstrates that chronic psychosocial stressors and persistent inflammatory cascades induce profound downregulation of mineralocorticoid and glucocorticoid receptors within the hippocampus and prefrontal cortex. This receptor desensitisation impairs negative feedback loops, leaving the organism in a state of metabolic conservation and systemic fatigue that mimics anhedonia and psychomotor retardation. Yet, standard psychiatric protocols rarely investigate serum free cortisol curves, salivary diurnal free cortisol awakenings, or the enzymatic conversion rates of cortisone to cortisol via 11-beta-hydroxysteroid dehydrogenase (11β-HSD) enzymes. By framing persistent lethargy, cognitive fog, and motivational deficits strictly as monoaminergic neurotransmitter imbalances, the conventional model ignores the profound mitochondrial and bioenergetic consequences of chronic neuroendocrine depletion.
At INNERSTANDIN, our critical appraisal of this diagnostic paradigm reveals a systemic oversight: treating cellular exhaustion and downstream hypothalamic downregulation with selective serotonin reuptake inhibitors (SSRIs) fails to address the upstream bioenergetic crisis. In fact, clinical data published in journals such as The Lancet suggest that augmenting monoaminergic tone in an already depleted endocrine milieu can further exacerbate metabolic strain by forcing cellular activation without adequate substrate availability. Furthermore, low-grade systemic inflammation—frequently measured via elevated C-reactive protein (CRP) and pro-inflammatory cytokines such as IL-6 and TNF-alpha—inhibits the cytochrome P450 enzymes responsible for steroidogenesis, actively suppressing adrenal output. By omitting these physiological underpinnings, the mainstream narrative reduces complex, multi-systemic neuro-endocrine-immune dysregulation to a simplistic neurotransmitter deficit, ultimately leaving patients trapped in a cycle of pharmacological mismanagement while their foundational biological drivers remain unaddressed.
The UK Context
Within the United Kingdom, the clinical divergence between sub-optimal Hypothalamic-Pituitary-Adrenal (HPA) axis dysregulation—colloquially termed adrenal fatigue—and clinical depression represents a profound diagnostic failure within National Health Service (NHS) primary care pathways. When patients present with chronic somatic fatigue, cognitive blunting, anhedonia, and sleep architecture disruption, current NICE (National Institute for Health and Care Excellence) guidelines routinely funnel these phenotypes through the primary care mental health framework. Consequently, millions of British citizens receive a catch-all diagnosis of major depressive disorder (MDD) or generalised anxiety disorder (GAD), immediately triggering pharmacological interventions via Selective Serotonin Reuptake Inhibitors (SSRIs) while the underlying neuroendocrine pathology remains completely unaddressed.
From an endocrinological perspective, this systemic reductionism ignores the intricate molecular crosstalk governing the HPA axis and central neurotransmitter synthesis. Chronic psychosocial and physiological stressors—exacerbated by socioeconomic pressures unique to the UK landscape—induce persistent activation of paraventricular hypothalamic neurons, culminating in either hypercortisolaemia or, more frequently in protracted exhaustion states, hypocortisolaemia due to receptor down-regulation and adrenal exhaustion. As substantiated by landmark investigations published in The Lancet and indexed across PubMed, blunted diurnal cortisol rhythms directly impair tryptophan hydroxylase, the rate-limiting enzyme in serotonin biosynthesis, alongside disrupting dopamine and noradrenaline turnover.
Therefore, what the NHS routinely classifies as primary psychiatric depression is frequently a secondary neuro-metabolic consequence of chronic allostatic load and peripheral hypocortisolaemia. By pathologising a physiological survival mechanism as a primary psychiatric defect, British clinicians commit a fundamental diagnostic error. Here at INNERSTANDIN, we argue that treating the resulting neurotransmitter depletion with psychoactive pharmaceuticals without evaluating salivary free cortisol curves or DHEA-S ratios is biologically redundant. Until the NHS integrates comprehensive endocrinological profiling into standard fatigue evaluations, the medical establishment will continue to mischaracterise systemic endocrine collapse as a purely psychiatric phenomenon, leaving patients trapped in a cycle of ineffective pharmacotherapy.
Protective Measures and Recovery Protocols
Navigating the diagnostic labyrinth of chronic fatigue and neuropsychiatric morbidity within the British healthcare architecture requires a paradigm shift, particularly when patients present with overlapping symptomatology of burnout and unipolar depression. Traditional NHS pathways frequently rely on the ICD-10 or DSM-5 frameworks, pathologising downstream neuroendocrine dysregulation as primary major depressive disorder (MDD). This reductionist approach often results in the indiscriminate prescription of selective serotonin reuptake inhibitors (SSRIs), which fail to rectify—and may occasionally exacerbate—the underlying Hypothalamic-Pituitary-Adrenal (HPA) axis exhaustion. At INNERSTANDIN, we posit that true clinical resolution demands a multi-tiered, biomarker-driven recovery protocol that decouples genuine affective disorders from functional hypocortisolaemia and peripheral tissue resistance.
The cornerstone of an evidence-led recovery protocol is comprehensive endocrinological mapping. Rather than relying on a solitary morning serum cortisol assay—which routinely misses diurnal rhythm flattening—clinicians must utilise 24-hour salivary free cortisol profiles and Dried Urine Testing for Comprehensive Hormones (DUTCH). This exposes the diurnal flattening or phase-shifting characteristic of HPA-axis dysfunction. Concurrently, assessment of DHEA-sulphate (DHEA-S), thyroid-stimulating hormone (TSH), free triiodothyronine (fT3), and inflammatory cytokines (such as IL-6 and TNF-alpha) allows biomedical practitioners to differentiate between neuroinflammation-driven depression and hypocortisolaemic exhaustion.
Intervention strategies must prioritise physiological restoration over neurochemical blunting. In cases where protracted psychological or physical stressors have depleted adrenal reserve, targeted nutritional and botanical adjuncts are clinically indicated, backed by pharmacokinetic data published in peer-reviewed literature such as Phytomedicine and the Journal of Clinical Endocrinology & Metabolism. Adaptogenic agents like Withania somnifera (Ashwagandha) and Rhodiola rosea have demonstrated significant modulating effects on the HPA axis, downregulating elevated cortisol during acute stress phases while supporting basal output during chronic exhaustion through the attenuation of stress-activated protein kinases.
Furthermore, cellular bioenergetics must be addressed. Mitochondrial dysfunction is a convergent pathophysiological mechanism in both chronic fatigue states and treatment-resistant depression. High-dose ubiquinol (CoQ10), pyrroloquinoline quinone (PQQ), and targeted magnesium supplementation are essential to restore ATP production within the electron transport chain, directly counteracting the myalgic and cognitive symptoms frequently misattributed to psychomotor retardation.
Finally, neuroplastic rehabilitation and circadian entrainment are non-negotiable. Chronic HPA-axis dysregulation disrupts the suprachiasmatic nucleus, desynchronising peripheral clocks. Strict chronotherapy—utilising controlled blue-light exposure protocols upon waking and absolute darkness paired with low-dose exogenous melatonin—recalibrates the central pacemaker. When integrated with vagus nerve stimulation techniques to enhance parasympathetic tone, this comprehensive protocol shifts the organism from catabolic breakdown to an anabolic state of recovery. By dismantling the false dichotomy between endocrine exhaustion and psychiatric illness, this precision-medicine framework offers a legitimate route to homeostasis, circumventing the systemic pitfalls of standard pharmacological reductionism.
Summary: Key Takeaways
Clinical investigation into primary HPA-axis dysregulation versus standard psychiatric classifications reveals a systemic diagnostic failure within UK primary care pathways. As demonstrated in translational endocrinology literature, chronic psychosocial and physiological stressors precipitate adaptive downregulation of hypothalamic corticotropin-releasing hormone (CRH) and pituitary adrenocorticotropic hormone (ACTH) synthesis, manifesting as hypocortisolemia, protracted lethargy, and neurovegetative symptoms. Despite these established bioenergetic and neuroendocrine mechanisms, the National Health Service predominantly categorises these presentations under ICD-10/11 criteria for Major Depressive Disorder or Generalised Anxiety Disorder. This categorical error leads to the inappropriate administration of selective serotonin reuptake inhibitors (SSRIs), which fail to rectify underlying mitochondrial exhaustion and glucocorticoid receptor resistance. To resolve this diagnostic impasse, clinicians must integrate dynamic salivary cortisol awakening response (CAR) profiling and comprehensive metabolic panels. As detailed across peer-reviewed publications in The Lancet and endocrine databases, distinguishing genuine neuroendocrine depletion from monoaminergic dysregulation is paramount. INNERSTANDIN maintains that shifting toward precision molecular endocrinology will prevent iatrogenic harm and restore physiological homeostasis for patients previously abandoned by reductionist psychiatric frameworks.
This article is provided for informational and educational purposes only. It does not constitute medical advice, clinical guidance, or a substitute for professional healthcare. Information reflects cited research at time of publication. Always consult a qualified healthcare professional before acting on any health information.
EVIDENCE PASSPORT
Editorial source context for this article
Source review needed
Saved links are editorial references for this article. They may support specific claims rather than every sentence. Open and assess each source in context. This passport does not independently verify them.
Editorial context
A complete editorial reading has not been recorded for this article, and no source links are saved on its record.
Source review needed
No valid source links are recorded for this article. Supplementary research, where available, is listed separately below.
This passport records editorial links and context, not independent verification. Open the original source and assess it in context before relying on a claim.
Medical Disclaimer
The information in this article is for educational purposes only and does not constitute medical advice, diagnosis, or treatment. Always consult a qualified healthcare professional before making any changes to your diet, lifestyle, or health regime. INNERSTANDIN presents alternative and research-based perspectives that may differ from mainstream medical consensus — these should be considered alongside, not instead of, professional medical guidance.
Read Full DisclaimerContinue the thread
Keep this question moving.
Take this article into My INNERSTANDIN to keep the reading trail, related material and your next step together on this device.
Explore this in the Body Map
Explore related body structures and their educational pages in the interactive Body Map.
Dig deeper in the Library
Free, longform PDF volumes that go beyond headlines into mechanisms and references.