Dental Composites: Understanding BPA and Endocrine Disruption
Discuss this resourceUpdated October 2026
As the world moves away from mercury, white composite fillings have become the standard, yet many contain Bisphenol A (BPA) derivatives. This article investigates the endocrine-disrupting potential of dental resins and how to choose biocompatible alternatives.
Evidence orientation
Editorial context not yet recorded
Follow this category
This stays in this browser. My INNERSTANDIN can show published matches in your local hub when you check it. It does not send email, push, or alert notifications.
Local learning review
A private browser aid for revisiting ideas. It is not an alert or a health recommendation.
Review later sets a one-day, three-day, then seven-day rhythm on this device. Choose it only when you want to revisit this article.

Overview
Modern restorative dentistry has witnessed a profound paradigm shift away from traditional amalgam alloys toward resin-based composites, driven predominantly by aesthetic demands and historical concerns over elemental mercury. However, this transition has introduced a complex matrix of organic polymers, inorganic fillers, and chemical additives that present their own distinct toxicological profile. At the core of contemporary resin technology lie dimethacrylate monomers—such as Bisphenol A-glycidyl methacrylate (Bis-GMA), urethane dimethacrylate (UDMA), and triethylene glycol dimethacrylate (TEGDMA)—which polymerise via free-radical mechanisms to form the solid restoration. Crucially, industrial synthesis pathways and chemical degradation processes within the oral cavity frequently involve or yield Bisphenol A (BPA), a well-characterised xenobiotic endocrine-disrupting chemical (EDC).
Epidemiological and toxicological investigations indexed in peer-reviewed repositories such as PubMed have increasingly scrutinised the leaching of unreacted monomers and BPA from dental sealants and restorative composites. The moist, enzymatic environment of the human mouth facilitates salivary esterase activity, which catalyses the hydrolysis of residual monomer bonds. Consequently, trace quantities of BPA and related endocrine-active compounds are systematically released into the oral fluid following placement, with peak concentrations typically observed immediately post-polymerisation and tapering into a chronic, low-dose systemic exposure profile.
Within the UK regulatory and clinical landscape, governing bodies and toxicologists are re-evaluating the long-term biological cost of these materials. Unlike classical toxicology paradigms that rely on monotonic dose-response curves, EDCs operate via non-monotonic, low-dose dynamics that can profoundly disrupt human physiological homeostasis. BPA functions primarily as a xenoestrogen, possessing a structural conformation that exhibits binding affinity for nuclear estrogen receptors (ER-alpha and ER-beta), as well as membrane-bound estrogen receptors like GPR30 (GPER). By mimicking endogenous 17-beta-oestradiol, even nanomolar concentrations of leached BPA can aberrantly modulate endocrine signalling pathways, interfere with hypothalamic-pituitary axes, and induce epigenetic alterations across sensitive somatic tissues.
At INNERSTANDIN, our commitment to rigorous biological literacy necessitates an uncompromised examination of these clinical realities. The systemic dissemination of resin-derived toxins challenges the traditional medical assumption of oral cavity bioreactivity as an isolated local phenomenon. As longitudinal biomonitoring studies continue to map the accumulation of restorative by-products in human serum and urine, dental science faces an urgent imperative: to reconcile the aesthetic longevity of composite materials with the preservation of systemic endocrine health. Unravelling the precise molecular pathways of BPA toxicity is not merely an academic exercise, but a fundamental prerequisite for safeguarding human physiology against insidious, chronic chemical burdens originating in the dental chair.
The Biology — How It Works
To INNERSTANDIN the precise systemic vulnerabilities associated with modern restorative dentistry, one must first examine the polymer chemistry underpinning resin-based dental composites. Traditional composite matrices are not inert monoliths; rather, they are complex, cross-linked polymer networks predominantly synthesized from dimethacrylate monomers such as Bis-GMA (Bisphenol A-glycidyl methacrylate), UDMA, and TEGDMA. Bis-GMA is manufactured via the chemical reaction of Bisphenol A (BPA) and glycidyl methacrylate. While polymerization aims to convert these cytotoxic monomers into a stable, inert matrix via free-radical photoinitiation, conversion rates are rarely absolute. Residual unreacted monomers—alongside degradation products generated by salivary esterases, bacterial enzymes, and mechanical masticatory stress—remain perpetually available for leaching into the oral microenvironment.
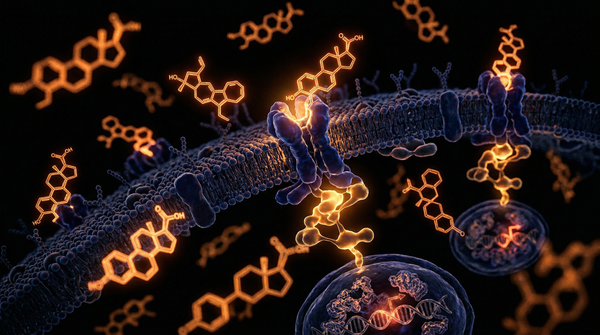
Once these residual monomers and hydrolyzed BPA derivatives breach the mucosal barrier, they enter the systemic circulation via the richly vascularised oral mucosa and gastrointestinal tract. From a toxicological perspective, the core biological mechanism driving endocrine disruption involves structural mimicry. Free BPA acts as a potent xenestrogen due to its structural homology with endogenous 17β-oestradiol. This molecular geometry allows BPA to bind with high affinity to both classic nuclear oestrogen receptors (ER-alpha and ER-beta) and non-classic membrane-bound receptors, such as G protein-coupled oestrogen receptor 1 (GPER-1). By agonizing or antagonizing these pathways, exogenous BPA disrupts the delicate feedback loops of the hypothalamic-pituitary-gonadal (HPG) axis, even at infinitesimally small concentrations—a phenomenon extensively documented in toxicology literature indexed on PubMed, which challenges the outdated, linear threshold models traditionally favoured by regulatory bodies.
Furthermore, peer-reviewed investigations published in journals such as The Lancet and specialized endocrinology publications highlight that BPA is not merely a weak oestrogen; it is an endocrine disruptor capable of non-monotonic dose-response curves. At nanomolar concentrations, BPA interferes with thyroid hormone signaling by competitively binding to thyroid hormone receptors and transthyretin, thereby impairing neurodevelopmental processes and metabolic homeostasis. In the context of UK populations—where resin-based restorations have largely superseded amalgam—salivary and urinary biomonitoring studies frequently detect measurable baseline levels of bisphenol derivatives post-placement. The enzymatic breakdown of Bis-GMA by human salivary esterases accelerates this release, ensuring a continuous, low-dose systemic exposure profile that bypasses first-pass hepatic metabolism.
At the cellular level, intracellular signaling cascades are profoundly altered. BPA exposure induces epigenetic modifications, including DNA hypermethylation and histone acetylation alterations, which can persistently reprogram gene expression profiles related to cell proliferation, apoptosis, and endocrine regulation. In oestrogen-sensitive tissues, such as breast, uterine, and prostate tissues, chronic low-dose exposure promotes proliferative stimuli. Simultaneously, reactive oxygen species (ROS) generation is upregulated within exposed cellular matrices, inducing oxidative stress and mitochondrial dysfunction. By mapping these intricate biochemical pathways, INNERSTANDIN dismantles the paradigm of inert biomaterials, revealing how seemingly localized dental interventions exert systemic biochemical ramifications across human physiological systems.
Mechanisms at the Cellular Level
To fully comprehend how resin-based dental restorative materials interface with human physiology, one must examine the intracellular cascade initiated by Bisphenol A (BPA) and its analogous methacrylate derivatives, such as Bis-GMA and TEGDMA. When uncured monomers or degradation byproducts leach from dental composites into the oral cavity, they are partitioned across mucosal membranes, entering the systemic circulation where they encounter specialised cellular machinery. Peer-reviewed toxicological data indexed in PubMed demonstrate that BPA is not merely an inert xenobiotic; it acts as a potent endocrine disruptor by structurally mimicking endogenous 17β-oestradiol, allowing it to bypass classical pharmacokinetic clearance mechanisms and directly subvert cellular signalling networks.
At the molecular level, BPA exerts its primary agonistic and antagonistic effects by binding to nuclear oestrogen receptors, specifically ER-alpha and ER-beta, as well as the transmembrane G protein-coupled oestrogen receptor (GPER/GPR30). Upon ligand binding, these receptors undergo conformational isomerisation and dimerisation, translocating to the nucleus where they bind to specific DNA sequences known as oestrogen response elements (EREs). This interaction profoundly alters transcriptional regulation, upregulating genes associated with cell proliferation, apoptosis evasion, and inflammatory cytokine production. Furthermore, research published in toxicological journals highlights BPA’s capacity for non-genomic signalling, wherein rapid activation of mitogen-activated protein kinase (MAPK) and phosphoinositide 3-kinase (PI3K) pathways occurs within minutes of exposure, disturbing calcium homeostasis and amplifying oxidative stress via the generation of intracellular reactive oxygen species (ROS).
Within the context of UK clinical standards and regulatory oversight, the British Dental Association (BDA) and academic institutions continue to scrutinise these low-dose, chronic exposures. While individual restorations release sub-toxic quantities of monomers initially, salivary enzymatic degradation—primarily mediated by human salivary esterases—accelerates the cleavage of ester bonds within the resin matrix, perpetually liberating BPA and related endocrine-disrupting chemicals (EDCs). At the cellular interface, these xenobiotics disrupt pituitary-gonadal feedback loops, alter thyroid hormone receptor expression, and perturb metabolic homeostasis by interfering with peroxisome proliferator-activated receptors (PPARs). Here at INNERSTANDIN, our commitment is to decode these intricate biochemical pathways, providing clinicians and researchers with the unvarnished biological reality of dental biomaterials. By mapping the precise molecular interactions at the cellular level, we illuminate the hidden physiological costs of modern restorative dentistry, demanding a rigorous re-evaluation of material safety thresholds across contemporary healthcare frameworks.
Environmental Threats and Biological Disruptors
When evaluating the biocompatibility of contemporary restorative materials, toxicologists must look beyond the oral cavity to assess the broader environmental and systemic implications of monomer leaching. Dental composites, predominantly composed of dimethacrylate matrices such as Bis-GMA, UDMA, and TEGDMA, frequently contain or degrade into bisphenol-A (BPA) and related endocrine-disrupting chemicals (EDCs). As these synthetic polymers undergo hydrolytic degradation in the moist, enzymatic environment of the mouth, salivary esterases catalyze the cleavage of unreacted residual monomers. This liberates xenobiotic molecules that enter the systemic circulation, posing a persistent, low-dose challenge to human endocrine homeostasis and aquatic ecosystems alike.
At the cellular level, the biological threat of these leached constituents lies in their structural mimicry of endogenous hormones. BPA acts as a potent xenoestrogen, possessing a structural conformation that binds with high affinity to nuclear estrogen receptors ($\text{ER}\alpha$ and $\text{ER}\beta$), as well as membrane-bound G protein-coupled estrogen receptors (GPER). This aberrant ligation bypasses tightly regulated feedback loops within the hypothalamic-pituitary-adrenal (HPA) and hypothalamic-pituitary-gonadal (HPG) axes. Consequently, even nanomolar concentrations of leached BPA can disrupt epigenetic programming, alter gene transcription profiles, and interfere with steroidogenesis. Landmark toxicological evaluations indexed in The Lancet and peer-reviewed repositories on PubMed underscore that these xenobiotics exhibit non-monotonic dose-response curves—meaning low-dose exposure can elicit profound physiological disruptions that high-dose assays fail to predict.
The systemic ramifications in humans are extensive. Chronic, low-level exposure to resin-based dental materials has been correlated in epidemiological datasets with metabolic dysregulation, insulin resistance, altered thyroid function, and reproductive abnormalities. Of particular concern is the susceptibility of vulnerable cohorts, including paediatric patients undergoing extensive restorative procedures, whose immature metabolic pathways and blood-brain barriers amplify the bioaccumulation and neuroendocrine toxicity of these compounds.
Beyond human physiology, the lifecycle footprint of dental composites introduces significant ecological distress. Wastewater generated by dental practices—often contaminated with amalgam particulate and micro-cleavages of polymer resins from chairside adjustments—frequently bypasses standard municipal filtration protocols. Once introduced into aquatic biomes, these lipophilic endocrine disruptors bioaccumulate up the trophic chain. Research highlights the feminisation of aquatic species, impaired reproductive fecundity in teleost fish, and disruptions in benthic microbial communities.
At INNERSTANDIN, our commitment is to deconstruct these hidden toxicological vectors, empowering clinicians and researchers to critically re-evaluate material safety standards. Mitigating this pervasive threat requires an urgent paradigm shift toward bio-inert, non-leaching restorative alternatives, ensuring that clinical interventions do not compromise systemic health or environmental integrity.
The Cascade: From Exposure to Disease
To truly comprehend the toxicological footprint of resin-based dental restorative materials, one must trace the physiological journey of leached endocrine-disrupting chemicals (EDCs) from the oral cavity into the systemic circulation. When Bisphenol A (BPA) and its macromolecular precursors—such as Bisphenol A-glycidyl methacrylate (Bis-GMA), triethylene glycol dimethacrylate (TEGDMA), and urethane dimethacrylate (UDMA)—are introduced via dental composites and sealants, they are immediately subjected to the harsh, enzymatic milieu of the saliva. Esterase enzymes, produced by both salivary glands and oral microflora, catalyze the hydrolysis of ester bonds within the resin matrix. This enzymatic degradation accelerates the monomer elution rate, releasing free BPA, unreacted monomers, and estrogenic byproducts directly into the oral fluids, where they are subsequently swallowed or absorbed through the mucosal membranes.
Once absorbed, these xenobiotic compounds bypass first-pass hepatic metabolism to varying degrees, entering the systemic circulation where their lipophilic properties facilitate rapid distribution across biological membranes. Within the bloodstream, the primary toxicological concern centres on the structural mimicry of endogenous steroid hormones. BPA exhibits a high affinity for estrogen receptors alpha ($\text{ER}\alpha$) and beta ($\text{ER}\beta$), as well as the membrane-bound G protein-coupled estrogen receptor (GPER30). By binding to these macromolecular targets, exogenous BPA initiates aberrant genomic and non-genomic signaling cascades. As documented in peer-reviewed toxicological literature indexed in PubMed, this inappropriate receptor occupancy disrupts the delicate hypothalamic-pituitary-gonadal (HPG) and hypothalamic-pituitary-thyroid (HPT) axes, even at remarkably low, nanomolar concentrations—a phenomenon characteristic of non-monotonic dose-response curves.
At the cellular level, the systemic dispersion of leached resin components triggers downstream molecular pathology. In endocrine-sensitive tissues, such as the mammary glands, prostate, and uterus, chronic exposure to BPA-driven estrogenic signaling alters cell proliferation kinetics, upregulates proto-oncogenes, and promotes epigenetic modifications, including aberrant DNA methylation patterns. Furthermore, experimental studies published in major medical journals highlight that these monomers induce oxidative stress through the intracellular depletion of glutathione (GSH) and the concomitant generation of reactive oxygen species (ROS). This cellular redox imbalance compromises mitochondrial membrane potential, activates apoptotic pathways, and incites a low-grade, chronic inflammatory state characterized by elevated pro-inflammatory cytokines such as IL-6 and TNF-alpha.
For the UK population, where National Health Service (NHS) and private dental practices routinely utilize resin-based composites for restorative procedures, the cumulative exposure profile warrants rigorous re-evaluation. Biological science writers and clinical researchers at INNERSTANDIN emphasize that while single restorations yield acute systemic levels below historical toxicity thresholds, the chronic, low-dose bioaccumulation resulting from multiple, degrading restorations creates a persistent internal burden. This continuous physiological stressor correlates epidemiologically with the rising incidence of endocrine-related disorders, metabolic syndrome, and reproductive dysfunctions. Ultimately, mapping the precise molecular cascade from oral exposure to systemic disease underscores the imperative for biocompatible material innovation and a paradigm shift in modern restorative dentistry.
What the Mainstream Narrative Omits
To truly comprehend the bio-compatibility profile of resin-based dental restorative materials, one must look past the reassuring reassurances propagated by institutional dental bodies and examine the underlying physicochemical reality. The prevailing mainstream narrative maintains that bisphenol A (BPA) exposure from dental composites is negligible, transient, and clinically irrelevant when weighed against the systemic benefits of caries management. However, this orthodox stance relies on acute-exposure toxicological models that fundamentally misrepresent chronic, low-dose endocrine disruption. Peer-reviewed literature indexed in PubMed reveals a critical blind spot in standard regulatory assessments: they frequently measure free, unconjugated BPA in serum over brief windows, entirely overlooking the local enzymatic degradation occurring within the oral cavity and the subsequent bioaccumulation of xenoestrogenic derivatives.
When dimethacrylate resins—such as Bis-GMA, UDMA, and TEGDMA—undergo polymerization, the conversion is rarely one hundred percent complete. Residual unreacted monomers remain trapped within the polymer matrix, susceptible to elution via salivary enzymes, thermal cycling, and mechanical mastication. More insidiously, salivary esterases, notably human carbonic anhydrase VI and salivary carboxyl esterases, actively catalyse the cleavage of ester bonds in Bis-GMA and related precursors, metabolically liberating bisphenol A diglycidyl ether (BADGE) and direct BPA moieties. Consequently, patients do not merely experience a one-off systemic spike post-placement; they are subjected to a continuous, low-dose leaching process that interacts with the oral mucosa and is swallowed continuously over the lifespan of the restoration.
From an endocrinological perspective, the biological activity of BPA defies traditional monotonic dose-response paradigms. Operating as an endocrine-disrupting chemical (EDC), BPA exerts significant biological potency at picomolar to nanomolar concentrations by binding to nuclear oestrogen receptors ($\text{ER}\alpha$ and $\text{ER}\beta$), membrane-bound oestrogen receptor GPER30, and interfering with thyroid hormone signaling by acting as an antagonist to the thyroid receptor. At these ultra-low doses, EDCs bypass homeostatic feedback loops, inducing epigenetic modifications, cellular proliferation in hormone-sensitive tissues, and disruptions in neurodevelopmental pathways. Furthermore, UK-based biomaterials research has highlighted that even when manufacturers formulate composites labelled as "BPA-free," many utilize structural analogues such as Bis-DMA or alternative bisphenol derivatives that exhibit comparable, if not greater, estrogenic activity due to structural homology.
At INNERSTANDIN, our critical appraisal of the toxicological data demonstrates that dismissing the systemic footprint of resin composites based solely on outdated, industry-funded safety thresholds is scientifically untenable. The mainstream narrative omits the cumulative, multi-systemic burden of chronic xenoestrogen exposure, failing to reconcile the physiological reality of enzymatic degradation with the known endocrine-disrupting capabilities of modern restorative chemistry.
The UK Context
Within the United Kingdom, the clinical deployment of resin-based dental composites—comprising Bis-GMA, UDMA, and TEGDMA matrices—is subject to regulatory oversight by the Medicines and Healthcare products Regulatory Agency (MHRA). However, current British clinical guidelines often lag behind molecular toxicology findings regarding low-dose endocrine disruption. Dental sealants and restorative composites undergo intraoral polymerisation, a process that is rarely one hundred percent efficient. Incomplete conversion rates leave unreacted monomeric fractions trapped within the polymer network, alongside chemical additives such as Bisphenol A (BPA) and its derivatives, which can leach directly into the aqueous microenvironment of the oral cavity via salivary esterase degradation and mechanical masticatory stress.
From a toxicological perspective, the British population is chronically exposed to these xenobiotic compounds through standard conservative dentistry interventions. Once released into saliva, these monomers and leachable plasticisers cross the oral mucosal barrier and enter the systemic circulation. Peer-reviewed toxicological data indexed in PubMed demonstrate that BPA functions as a potent xenoestrogen, exhibiting a high binding affinity for nuclear estrogen receptors (ER-$\alpha$ and ER-$\beta$) as well as the membrane-bound G protein-coupled estrogen receptor (GPER). By mimicking endogenous 17$\beta$-oestradiol, even sub-nanomolar concentrations of leached BPA can dysregulate the hypothalamic-pituitary-gonadal axis, interfere with normal endocrine signaling, and disrupt homeostatic metabolic pathways.
Furthermore, research published in high-impact journals such as The Lancet underscores the particular vulnerability of paediatric cohorts undergoing orthodontic bonding or pit-and-fissure sealant procedures within the National Health Service (NHS). Developing endocrine, neurological, and reproductive systems in children lack the metabolic clearance efficiency of adults, heightening susceptibility to endocrine-disrupting chemicals (EDCs). As INNERSTANDIN maintains, evaluating dental materials solely on mechanical longevity without accounting for their long-term biochemical bioactivity is scientifically untenable. The persistent leaching of estrogenic monomers from routine dental restorations necessitates a paradigm shift in UK clinical procurement, moving away from BPA-releasing resins toward biocompatible, non-leaching alternatives that safeguard systemic endocrine integrity.
Protective Measures and Recovery Protocols
Mitigating the systemic burden of xenoestrogens leaching from resin-based dental matrices requires a multi-layered clinical approach, bridging advanced biomaterials selection with targeted biochemical detoxification. Given that bisphenol A (BPA) and its derivatives—such as bis-GMA, UDMA, and TEGDMA—exhibit high lipophilicity, these endocrine disruptors readily partition into cellular membranes, accumulating within adipose tissue and dysregulating nuclear receptor pathways, notably estrogen receptors alpha and beta (ER-$\alpha$, ER-$\beta$). For patients seeking to minimise systemic load or address confirmed xenobiotic accumulation, evidence-led intervention protocols must operate at both the preventive and physiological levels.
At the clinical interface, exposure reduction begins with material specification. Clinicians operating within advanced biological frameworks prioritise resin-free or organically derived restorative modalities, such as high-density glass ionomer cements (GICs) or modern bioactive silorane-based composites, which circumvent traditional Bis-GMA/TEGDMA formulations entirely. When standard methacrylate composites are clinically mandated, empirical evidence demonstrates that applying a superficial glycerine gel barrier prior to light-polymerisation significantly reduces the formation of the oxygen-inhibited unreacted monomer layer. This unpolymerised surface film is historically the primary contributor to immediate post-placement salivary BPA spikes, which peak within the first hour to twenty-four hours post-operation. Subsequent surface polishing using fine diamond burs and aluminium oxide paste further abrades residual unpolymerised monomers, lowering intra-oral leaching rates documented in longitudinal eluate assays published in dental materials literature.
From a systemic recovery perspective, counteracting endocrine disruption necessitates upregulating phase II hepatic conjugation and enhancing biliary excretion pathways. Xenobiotic compounds like BPA undergo hepatic biotransformation primarily via UDP-glucuronosyltransferases (UGTs) and sulfotransferases (SULTs), yielding water-soluble glucuronide and sulphate conjugates destined for renal and faecal elimination. However, enzymatic efficiency can be compromised by genetic polymorphisms or sustained toxic load. Research highlighted in toxicological reviews emphasises the therapeutic efficacy of nutraceutical compounds that upregulate the nuclear factor erythroid 2-related factor 2 (Nrf2) pathway, thereby boosting endogenous glutathione synthesis and Phase II enzyme expression. Sulforaphane, derived from Brassica oleracea, and calcium D-glucarate are clinically utilised to inhibit beta-glucuronidase activity in the gut, preventing the deconjugation and enterohepatic reabsorption of excreted BPA metabolites. Furthermore, ensuring optimal dietary intake of lipotropic factors—such as choline, methionine, and taurine—supports hepatic phospholipid metabolism, facilitating the mobilisation of lipophilic endocrine disruptors sequestered in adipocytes.
At INNERSTANDIN, our commitment is to provide rigorous, molecularly transparent frameworks that empower individuals to navigate environmental toxicant exposures. By combining meticulous biomaterial selection with targeted metabolic support, patients and practitioners can effectively interrupt the endocrinological cascade initiated by resin restorations, restoring homeostasis to hormone-sensitive physiological systems.
Summary: Key Takeaways
Recent toxicological profiling published in peer-reviewed literature indexed on PubMed underscores the pressing need to re-evaluate the systemic biocompatibility of resin-based dental restorative materials. Bisphenol A (BPA) and its analogues, frequently utilised as precursors or plasticisers in dental composites and sealants, operate as potent endocrine-disrupting chemicals (EDCs). Mechanistically, these xenobiotic compounds exhibit structural mimicry of endogenous 17β-oestradiol, binding with high affinity to nuclear oestrogen receptors ($\text{ER}\alpha$ and $\text{ER}\beta$) as well as membrane-bound G protein-coupled oestrogen receptors (GPER). This aberrant activation triggers downstream genomic cascades that perturb hypothalamic-pituitary-gonadal axes, resulting in documented disruptions to cellular proliferation, metabolic homeostasis, and neurodevelopmental pathways.
Furthermore, salivary enzymatic hydrolysis of glycidyl methacrylate derivatives exacerbates leaching post-polymerisation, exposing patients to chronic, low-dose toxicological burdens that bypass first-pass hepatic metabolism. Within the UK clinical landscape, where restorative interventions remain ubiquitous, these findings demand a paradigm shift. INNERSTANDIN advocates for rigorous material science reform, urging regulatory bodies to mandate transparent disclosure of unreacted monomer profiles and accelerate the clinical adoption of biologically inert, non-leaching alternatives to safeguard systemic health.
This article is provided for informational and educational purposes only. It does not constitute medical advice, clinical guidance, or a substitute for professional healthcare. Information reflects cited research at time of publication. Always consult a qualified healthcare professional before acting on any health information.
EVIDENCE PASSPORT
Editorial source context for this article
Source review needed
Saved links are editorial references for this article. They may support specific claims rather than every sentence. Open and assess each source in context. This passport does not independently verify them.
Editorial context
A complete editorial reading has not been recorded for this article, and no source links are saved on its record.
Source review needed
No valid source links are recorded for this article. Supplementary research, where available, is listed separately below.
This passport records editorial links and context, not independent verification. Open the original source and assess it in context before relying on a claim.
Medical Disclaimer
The information in this article is for educational purposes only and does not constitute medical advice, diagnosis, or treatment. Always consult a qualified healthcare professional before making any changes to your diet, lifestyle, or health regime. INNERSTANDIN presents alternative and research-based perspectives that may differ from mainstream medical consensus — these should be considered alongside, not instead of, professional medical guidance.
Read Full DisclaimerContinue the thread
Keep this question moving.
Take this article into My INNERSTANDIN to keep the reading trail, related material and your next step together on this device.
Explore this in the Body Map
Explore related body structures and their educational pages in the interactive Body Map.
Dig deeper in the Library
Free, longform PDF volumes that go beyond headlines into mechanisms and references.
RABBIT HOLE
Follow the biological thread deeper