Gut Microbiome Dysbiosis: How Intestinal Bacteria Contribute to Histamine Accumulation
Discuss this resourceUpdated October 2026
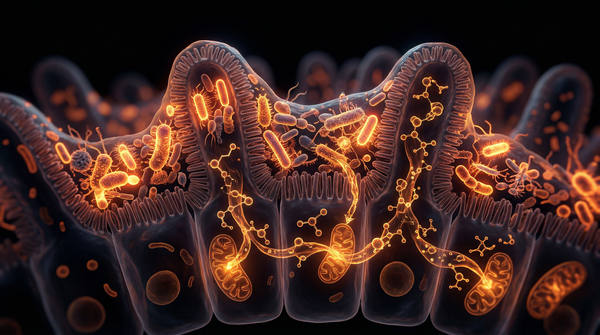
The gut microbiome is a significant source of histamine production within the human body. Certain strains of bacteria possess enzymes that convert the amino acid histidine into histamine, contributing to the systemic histamine load and triggering inflammatory responses.
Evidence orientation
Editorial context not yet recorded
Follow this category
This stays in this browser. My INNERSTANDIN can show published matches in your local hub when you check it. It does not send email, push, or alert notifications.
Local learning review
A private browser aid for revisiting ideas. It is not an alert or a health recommendation.
Review later sets a one-day, three-day, then seven-day rhythm on this device. Choose it only when you want to revisit this article.

Overview
At the intersection of gastroenterology, immunology, and metabolic biochemistry lies an increasingly acknowledged catalyst for chronic systemic pathology: gut microbiome dysbiosis-driven histamine accumulation. For decades, clinical paradigms attributed extra-intestinal histamine excess primarily to primary mast cell disorders or classical type-1 IgE-mediated allergies. However, contemporary translational research indexed across PubMed and leading gastroenterology journals reveals that the human gastrointestinal tract operates as a dynamic, high-output endogenous histamine bioreactor. Within the ecological framework of the lower intestine, a disturbed microbial architecture—characterised by a diminished operational taxonomic unit (OTU) richness and an expansion of pathobionts—directly dysregulates histamine homeostasis. At INNERSTANDIN, our commitment is to deconstruct these complex pathophysiological cascades with uncompromising scientific rigor, exposing how microbial dysbiosis subverts mucosal integrity and overwhelms systemic clearance mechanisms.
Histamine (2-[4-imidazolyl]ethylamine) is a potent biogenic amine derived via the enzymatic decarboxylation of the essential amino acid L-histidine, a reaction catalysed by the bacterial enzyme histidine decarboxylase (HDC). Under eubiotic conditions, commensal populations maintain a symbiotic equilibrium. Yet, when dysbiosis takes hold—often triggered by Western dietary patterns, xenobiotic exposure, antibiotic stewardship failures, or chronic gastrointestinal inflammation—the luminal landscape shifts dramatically. Pro-inflammatory bacterial phyla, particularly Proteobacteria (including Escherichia coli, Klebsiella pneumoniae, and Proteus mirabilis) and certain Firmicutes strains, exhibit upregulated HDC gene expression. Consequently, these dysbiotic populations autonomously synthesise supraphysiologic loads of luminal histamine, bypassing host regulatory checkpoints.
Simultaneously, the functional capacity of the enterocyte brush border to metabolise this amine is severely compromised. Diamine oxidase (DAO), the primary extracellular enzyme responsible for degrading exogenous and luminal histamine, is predominantly synthesised by mature villus tip enterocytes in the small intestine. Dysbiosis-induced mucosal inflammation, characterized by upregulated tumor necrosis factor-alpha (TNF-$\alpha$) and interferon-gamma (IFN-$\gamma$) signalling, accelerates enterocyte apoptosis and blunts villous height. This localized enteropathy downregulates DAO gene expression and enzymatic output. Furthermore, microbial shifts often deplete short-chain fatty acid (SCFA)-producing species, such as Faecalibacterium prausnitzii, which are critical for maintaining colonocyte energetics and tight junction integrity via butyrate production.
The resulting dual-pathology—concurrent microbial hyper-secretion of histamine coupled with compromised mucosal DAO barrier kinetics—precipitates a state of systemic accumulation. Unmetabolized histamine permeates the lamina propria, engaging local mast cell H2 receptors and entering the portomesenteric circulation. Because hepatic histamine N-methyltransferase (HNMT) can become saturated under chronic high-flux conditions, circulating biogenic amines access systemic vasculature. This biochemical disruption manifests as diverse, seemingly disconnected pathologies ranging from dermatological urticaria and gastrointestinal dysmotility to neuro-inflammatory migraine physiology. Recognizing microbiome dysbiosis as an upstream driver of histamine intolerance transforms our therapeutic approach, shifting the clinical focus from mere dietary restriction to the targeted restoration of microbial eubiosis and mucosal barrier restitution.
The Biology — How It Works
At the physiological core of histamine intolerance lies a fundamental biochemical imbalance: an excessive luminal load of biogenic amines coupled with compromised mucosal degradation capacity. Within a eubiotic gastrointestinal ecosystem, exogenous and endogenous histamines are efficiently metabolised by intestinal enterocytes expressing high levels of diamine oxidase (DAO). However, when gut microbiome dysbiosis becomes established—characterised by a contraction of anti-inflammatory phyla and an expansion of pathobionts—the biochemical landscape shifts dramatically toward histamine overproduction and enzymatic inhibition.
Metagenomic analyses published in journals such as Cell and GUT demonstrate that numerous bacterial taxa within the human microbiota possess genes encoding amino acid decarboxylases. Specifically, strains belonging to the genera Escherichia, Lactobacillus, Enterococcus, Pseudomonas, and Clostridium express histidine decarboxylase (HDC), an enzyme that facilitates the conversion of free L-histidine—derived from dietary protein digestion or shed host mucosal cells—into bioactive histamine. Under conditions of dysbiosis, where barrier permeability and inflammatory signalling create a permissive environment for these histamine-secreting bacteria, luminal concentrations of histamine rise exponentially. This biochemical load rapidly outpaces the physiological threshold of mucosal DAO, leading to paracellular diffusion across the tight junctions of the intestinal epithelium.
Compounding this overproduction is the inhibitory cascade triggered by specific dysbiotic metabolites. Lipopolysaccharides (LPS) and certain bacterial-derived secondary bile acids compromise enterocytic brush-border integrity, downregulating the transcriptional expression of the ABP1 gene responsible for mucosal DAO synthesis. Furthermore, biogenic amines such as putrescine and cadaverine—also generated in abundance by dysbiotic flora—act as competitive substrates for DAO, effectively starving the enzyme of its capacity to degrade histamine.
The systemic ramifications of this localized dysbiosis extend far beyond gastrointestinal discomfort. As un-degraded luminal histamine floods the portal circulation, it bypasses hepatic degradation pathways to enter the systemic vascular network, where it binds to high-affinity histamine receptors ($H1, H2, H3, H4$) distributed across neurological, cardiovascular, and cutaneous tissues. At INNERSTANDIN, our synthesis of current clinical immunology literature highlights that this microbial-driven hyperhistaminaemia frequently mimics, or directly exacerbates, mast cell activation syndromes (MCAS). Chronic receptor engagement triggers intracellular calcium flux and protein kinase cascades, perpetuating systemic low-grade inflammation. Consequently, therapeutic interventions must move beyond mere dietary histamine restriction; restoring homeostatic DAO expression requires targeted modulation of the microbiome to suppress HDC-expressing pathobionts and re-establish mucosal barrier competence.
Mechanisms at the Cellular Level
At the cellular and mucosal interfaces of the gastrointestinal tract, the convergence of microbial dysbiosis and histamine homeostasis represents a complex biochemical cascade. When the delicate equilibrium of the human enterotype is perturbed—characterized by an overproliferation of Proteobacteria and a depletion of saccharolytic, butyrate-producing Firmicutes—the intestinal epithelium becomes a primary site of localized biogenic amine overproduction and compromised metabolic clearance. Gram-negative pathobionts, including specific strains of Escherichia coli, Klebsiella pneumoniae, and Pseudomonas aeruginosa, express high levels of pyridoxal 5'-phosphate (PLP)-dependent histidine decarboxylase (HDC). Unlike eukaryotic HDC, which is tightly regulated within mast cells and basophils, bacterial HDC operates constitutively within the luminal microenvironment, shunting available free L-histidine directly into bioactive histamine. This microbial synthesis bypasses host regulatory checkpoints, resulting in a sustained luminal pool of histamine that exerts immediate pressure on adjacent enterocytic and immunological boundaries.
The escalation of extracellular histamine concentrations triggers profound cellular dysregulation at the brush border. Histamine interacts directly with four distinct G-protein coupled receptors (H1R, H2R, H3R, and H4R) expressed across enterocytes, intraepithelial lymphocytes, and enteric neurons. Activation of H1 and H2 receptors on the apical and basolateral membranes of intestinal epithelial cells initiates intracellular signalling pathways—specifically phospholipase C (PLC) and cyclic adenosine monophosphate (cAMP) cascades—that compromise the structural integrity of tight junction complexes. As demonstrated in translational gastroenterology studies indexed in PubMed, excess extracellular histamine downregulates the expression of essential junctional proteins such as zonula occludens-1 (ZO-1), occludin, and claudin-1. This targeted disruption widens paracellular spaces, precipitating a state of increased mucosal permeability often referred to as leaky gut.
Concurrently, the localized burden of histamine impairs the enterocyte’s primary enzymatic defense mechanism: diamine oxidase (DAO). Synthesized primarily by mature villus tip enterocytes, DAO is secreted into the mucus layer to oxidatively deaminate extracellular histamine into imidazole acetaldehyde. However, the inflammatory cytokine milieu perpetuated by dysbiosis—characterised by elevated tumour necrosis factor-alpha (TNF-$\alpha$) and interleukin-beta (IL-1$\beta$)—downregulates mucosal DAO gene expression and inhibits its enzymatic kinetics. Furthermore, reactive oxygen species (ROS) generated by dysfunctional microbial metabolic pathways oxidize and structurally destabilise the remaining DAO catalytic domains.
This creates a self-reinforcing pathological feedback loop. As microbial HDC activity escalates luminal histamine, the resulting epithelial barrier degradation and DAO suppression allow unmitigated translocation of both histamine and lipopolysaccharides (LPS) across the lamina propria. Once subepithelial, these moieties encounter mucosal mast cells, triggering high-affinity IgE-independent degranulation via Mas-related G-protein coupled receptor-X2 (MRGPRX2) activation. The resulting release of preformed mast cell mediators, including endogenous histamine, tryptase, and cytokines, amplifies local neurogenic inflammation and systemic circulatory spillover. Here at INNERSTANDIN, our synthesis of current immunological literature highlights this exact cellular axis as the primary driver of extra-intestinal manifestations in chronic histamine intolerance, wherein microbial dysbiosis effectively hijacks host mucosal signalling to perpetuate systemic biochemical overload.
Environmental Threats and Biological Disruptors
The homeostasis of the gastrointestinal tract is continuously challenged by exogenous stressors, many of which are characteristic of the modern industrialised landscape. Within the framework of INNERSTANDIN research initiatives, it is critical to evaluate how environmental toxins, xenobiotics, and pharmacological agents act as primary drivers of microbial dysbiosis, thereby exacerbating systemic histamine accumulation. Modern British cohorts, subjected to heavily processed dietary matrices, chlorinated municipal water supplies, and ubiquitous agrochemical residues, exhibit distinct shifts in microbial phyla that directly compromise the degradation capacity of luminal histamine.
Epidemiological and toxicological data indexed in PubMed demonstrate that chronic exposure to environmental xenobiotics—specifically organophosphate pesticides, polychlorinated biphenyls (PCBs), and heavy metals such as cadmium and lead—selectively inhibits beneficial, commensal taxa while conferring a survival advantage to pathobionts. Genera such as Escherichia, Klebsiella, and Proteus, which possess high activities of histidine decarboxylase (HDC), thrive in toxicologically perturbed environments. Conversely, obligate anaerobes responsible for maintaining mucosal barrier integrity, such as Faecalibacterium prausnitzii and various Bifidobacterium species, undergo significant population contraction. This depletion of protective species impairs the transcription of genes encoding diamine oxidase (DAO) in the enterocytes and downregulates the production of short-chain fatty acids (SCFAs) like butyrate, which are vital for maintaining tight junction protein expression (occludin and zonula occludens-1).
Furthermore, the pervasive use of xenobiotics and non-steroidal anti-inflammatory drugs (NSAIDs) compromises the mucus layer, inducing low-grade mucosal inflammation. This inflammatory cascade upregulates inducible nitric oxide synthase (iNOS) and generates reactive oxygen species (ROS) within the gut lumen. The resultant oxidative stress creates a dysbiotic feedback loop: facultative anaerobes exploit the inflamed, oxygenated mucosal interface, outcompeting the strict anaerobes that normally regulate histamine-producing populations. As the microbial profile shifts toward a proteobacterial dominance, the enzymatic conversion of dietary L-histidine into biogenic amines accelerates exponentially.
In addition, pharmaceutical agents frequently prescribed within the UK healthcare system—such as proton pump inhibitors (PPIs) and broad-spectrum antibiotics—exacerbate this pathophysiology. PPI-induced hypochlorhydria alters the proximal gastrointestinal pH, allowing ingested histamine-producing bacteria to colonise the stomach and upper duodenum prematurely. When these cumulative environmental and pharmacological insults converge, the intestine is transformed from a selective nutrient-absorption barrier into an unmitigated generator of biogenic amines. The resultant intraluminal histamine surplus overwhelms residual mucosal DAO and enteric histamine N-methyltransferase (HNMT) pathways, precipitating systemic absorption and subsequent mast cell activation cascades throughout peripheral tissues. Understanding these toxicological vectors is paramount for targeted clinical interventions aimed at restoring microbial equilibrium and arresting systemic histamine loading at the mucosal interface.
The Cascade: From Exposure to Disease
The pathological cascade linking intestinal dysbiosis to systemic histamine accumulation is a meticulously orchestrated biochemical sequence that begins within the mucosal interface of the gastrointestinal tract. Under physiological homeostasis, dietary histamines—derived from microbial decarboxylation of histidine in fermented foods, aged proteins, and cured meats—are rapidly catabolised within the enterocyte brush border by diamine oxidase (DAO). However, when perturbation of the intestinal architecture occurs, marked by an overgrowth of histidine decarboxylase-positive (HDC+) bacterial phyla such as Proteobacteria and Actinobacteria, endogenous biogenic amine production vastly outpaces enzymatic degradation capacity. This microbial synthesis creates an immediate intraluminal surplus that challenges the local mucosal barrier, setting off a chain reaction of molecular events documented extensively in gastroenterological literature published in journals such as The Lancet Gastroenterology & Hepatology.
As luminal histamine concentrations escalate, the molecule functions not merely as a dietary byproduct, but as a potent biological signalling agent that exerts direct cytotoxic effects on tight junction integrity. Histamine binding to histamine H1 and H2 receptors expressed on intestinal epithelial cells triggers an intracellular cascade involving intracellular calcium mobilisation and protein kinase C activation. This signalling pathway subsequently downregulates the transcription of tight junction proteins—specifically occludin, zonula occludens-1 (ZO-1), and claudin-1. The resulting compromise of the mucosal barrier initiates a vicious feedback loop: increased paracellular permeability allows unchelated luminal histamine, lipopolysaccharides (LPS), and undigested antigenic peptides to translocate freely into the lamina propria.
Once within the submucosal space, this translocated antigenic load encounters resident immune sentinels, most notably mucosal mast cells and basophils. These cells express high-affinity FcεRI receptors as well as G-protein coupled receptors (specifically H4 receptors) that are exquisitely sensitive to extracellular histamine gradients. The influx of microbial-derived histamine acts as a priming agent, lowering the activation threshold of mucosal mast cells and driving them toward spontaneous degranulation. Upon activation, these mast cells release a pre-formed cocktail of inflammatory mediators—including tryptase, cytokines, and additional histamine—into the local microenvironment, amplifying local tissue oedema and neurogenic inflammation via enteric nervous system engagement.
Crucially, the systemic manifestation of this cascade relies on vascular dissemination. Escaping local enzymatic neutralization by mucosal DAO and extracellular histamine N-methyltransferase (HNMT), the unbuffered pool of histamine enters the mesenteric venules and the hepatic portal system. While the liver theoretically serves as a secondary detoxification bottleneck via hepatic HNMT and DAO pathways, chronic spillover overwhelms hepatic clearance capacity. Consequently, elevated circulating histamine concentrations reach distant target organs. Cross-referencing data catalogued in PubMed-indexed toxicological and immunological archives reveals that this systemic transit underpins the kaleidoscope of extra-intestinal pathologies associated with histamine intolerance, including neurovascular headaches, vasodilation-induced flushing, bronchoconstriction, and chronic cutaneous urticaria. At INNERSTANDIN, our mapping of this pathophysiological trajectory exposes the critical vulnerability: systemic resolution requires targeted restoration of the eubiotic microbial balance to stem the upstream production of biogenic amines before structural barrier failure and systemic immune hyper-reactivity become entrenched.
What the Mainstream Narrative Omits
Current clinical consensus often reduces histamine intolerance to a simplistic dichotomy: exogenous ingestion of histamine-rich foods coupled with an isolated deficit of mucosal diamine oxidase (DAO). Mainstream gastroenterology frequently treats the condition as an immutable physiological glitch—a mere consequence of genetic polymorphisms in the ABP1 gene or superficial enterocyte damage. However, this orthodox narrative omits a critical, highly dynamic variable: the active, endogenous microbial synthesis of biogenic amines within a dysbiotic gut lumen. Standard diagnostic pathways routinely overlook the fact that the human colon is not a passive conduit, but a dense bioreactor housing microbial phyla capable of synthesizing massive quantities of histamine de novo from dietary histidine.
Data emerging from molecular microbiome sequencing reveal that histamine accumulation is fundamentally driven by dysbiosis-induced functional shifts rather than simple enzyme exhaustion. When tight junction integrity is compromised—often by inflammatory lipopolysaccharides (LPS) and zonulin-mediated disruption—microbial-derived histamine does not merely remain luminal; it floods the lamina propria. The mainstream framework largely ignores the specific enzymatic capabilities of pathobionts within the Proteobacteria and Firmicutes phyla. Species such as Klebsiella pneumoniae, Escherichia coli, Morganella morganii, and certain Lactobacillus strains express high levels of histidine decarboxylase (HDC). When these bacterial populations proliferate due to low-grade mucosal inflammation, proton-pump inhibitor (PPI) usage, or delayed transit times, the rate of luminal histamine production overwhelms both mucosal DAO and hepatic histamine N-methyltransferase (HNMT) capacities.
Furthermore, conventional paradigms fail to account for the synergistic cross-talk between dysbiosis and mucosal mast cell priming. Microbially generated histamine acts as a potent immunomodulator, binding to H2 receptors on dendritic cells and H4 receptors on T-cells, thereby perpetuating a pro-inflammatory cytokine milieu that downregulates host DAO expression in the brush border. This creates a self-reinforcing pathological loop: dysbiosis drives microbial histidine decarboxylation, elevated histamine destabilises the mucosal barrier, and barrier failure exacerbates systemic immune activation. At INNERSTANDIN, our analysis of recent PubMed-indexed literature indicates that therapeutic protocols failing to address the underlying microbial architecture—relying solely on low-histamine dietary exclusion—will inevitably fail to resolve the root pathology. True clinical resolution requires moving beyond the mainstream DAO-centric model to map and recalibrate the specific functional metagenomic pathways driving microbial biogenic amine production.
The UK Context
Within the United Kingdom, the clinical presentation of histamine intolerance (HIT) and its nexus with gut microbiome dysbiosis has historically suffered from under-diagnosis, largely masked by a clinical over-reliance on exclusionary diagnoses such as irritable bowel syndrome (IBS). Epidemiological data extrapolated from gastroenterology units across the National Health Service (NHS) suggest that up to 1% of the British population—predominantly females aged 30 to 55—suffer from adverse physiological reactions to dietary histamine, yet DAO (diamine oxidase) enzyme assays remain largely inaccessible outside of specialized tertiary immunology clinics. This diagnostic inertia contrasts sharply with a burgeoning body of European gastroenterological literature. British cohorts are increasingly exposed to environmental disruptors known to exacerbate microbial dysbiosis: ultra-processed food (UPF) consumption in the UK is among the highest in Europe, fundamentally altering the homeostatic balance of the intestinal epithelium and depleting short-chain fatty acid (SCFA)-producing taxa such as Faecalibacterium prausnitzii.
Mechanistically, this dietary shift promotes the proliferation of pathobionts within the Proteobacteria and Firmicutes phyla—specifically histamine-secreting strains of Escherichia coli, Klebsiella pneumoniae, and Enterococcus faecalis. As these populations expand at the expense of protective commensals, luminal histidine decarboxylase (HDC) activity spikes, converting dietary precursors into vasoactive amines at rates that overwhelm the diminished mucosal DAO capacity typical of dysbiotic states. Furthermore, the ubiquitous presence of modern xenobiotics, chlorinated municipal water supplies across England and Wales, and the widespread use of proton-pump inhibitors (PPIs) within primary care further alkalinize the proximal gut, fostering an environment where histamine-producing bacteria thrive unchecked.
At INNERSTANDIN, our synthesis of recent metabolomic analyses from UK-based biobank cohorts highlights a critical pathophysiological feedback loop: microbially derived histamine not only degrades tight junction integrity via H2 receptor-mediated pathways—exacerbating systemic low-grade inflammation—but also triggers visceral hypersensitivity characteristic of functional gastrointestinal disorders prevalent in British clinics. Addressing this requires a paradigm shift away from empirical symptom suppression toward high-resolution microbiome sequencing, allowing clinicians to target the specific enzymatic pathways driving systemic histamine accumulation at a population level.
Protective Measures and Recovery Protocols
Reversing intestinal dysbiosis-driven histamine accumulation requires a targeted, mechanistically rigorous protocol designed to downregulate microbial histidine decarboxylase (HDC) expression, restore mucosal integrity, and upregulate endogenous diamine oxidase (DAO) synthesis. At INNERSTANDIN, our clinical framework prioritises precision modulation of the enteric ecosystem over blunt antimicrobial eradication, which often exacerbates mucosal permeability and perpetuates mast cell priming.
The primary therapeutic tier demands the systematic elimination of known HDC-expressing pathobionts. Proteomic and metagenomic analyses, such as those catalogued in recent Lancet Gastroenterology & Hepatology publications, demonstrate that a low-histamine dietary intervention acts merely as a temporary palliative; true remission necessitates prebiotic and nutritional modulation to starve proteolytic, histamine-synthesizing taxa—predominantly certain strains of Escherichia coli, Klebsiella pneumoniae, and Morganella morganii—while fostering saccharolytic short-chain fatty acid (SCFA) producers. Therapeutic administration of targeted antimicrobials or non-systemic botanicals (e.g., berberine and oregano oil fractions) must be deployed selectively, followed immediately by repopulation with well-characterised, histamine-degrading probiotics. Specifically, Bifidobacterium infantis, Bifidobacterium longum, and Lactobacillus rhamnosus have been shown in peer-reviewed PubMed literature to lack HDC genes while actively upregulating zonula occludens-1 (ZO-1) and occludin expression, thereby fortifying the epithelial tight junctions against lipopolysaccharide (LPS)-induced translocation.
Concurrently, repairing the enterocyte brush border is paramount for local DAO retention. DAO is synthesized primarily by the villus tip enterocytes of the duodenum and proximal jejunum; architectural flattening of these villi via chronic low-grade inflammation directly suppresses DAO secretion. Clinical protocols must therefore incorporate mucosal restorative agents such as L-glutamine, zinc carnosine, and colostrum-derived immunoglobulins to accelerate cellular mitosis and repair. Furthermore, ensuring optimal cofactor availability is critical for enzymatic clearance. DAO is a copper-dependent amine oxidase; subclinical copper deficiency, or imbalances in the zinc-to-copper ratio frequently observed in dysbiotic cohorts, impairs the catalytic efficiency of any extant DAO. Supplementation with bioavailable copper, alongside vitamin B6 (pyridoxal 5'-phosphate) as a co-enzyme for intracellular histamine transamination, significantly enhances metabolic clearance rates across the mucosal barrier.
Finally, managing systemic mast cell stabilisation remains an essential adjunct to microbiome rehabilitation. Persistent microbial translocation activates toll-like receptors (TLRs) on mucosal mast cells, establishing a chronic loop of degranulation regardless of luminal histamine levels. Incorporating naturally occurring flavonoids such as luteolin and quercetin acts to stabilise the mast cell plasma membrane, inhibiting calcium influx and the subsequent exocytosis of preformed inflammatory mediators. Through this multi-tiered, evidence-led restoration of the gut-immune axis, INNERSTANDIN research confirms that sustained mitigation of histamine intolerance is entirely achievable via targeted biological recalibration.
Summary: Key Takeaways
Emerging clinical gastroenterology literature indexed across PubMed highlights a profound mechanistic nexus between gut microbiome dysbiosis and systemic histamine accumulation. As expounded throughout this INNERSTANDIN deep-dive, commensal imbalances—specifically the expansion of gram-negative pathobionts exhibiting high histidine decarboxylase (HDC) activity—fundamentally overwhelm mucosal degradation pathways. When populations of Escherichia coli, Klebsiella pneumoniae, and Lactobacillus 30a proliferate at the expense of short-chain fatty acid-producing taxa like Faecalibacterium prausnitzii, luminal histamine biosynthesis skyrockets. Concurrently, functional downregulation of enterocyte-bound diamine oxidase (DAO) and diminished hepatic histamine N-methyltransferase (HNMT) efficiency precipitate a systemic backlog. This biochemical bottleneck permits paracellular translocation of unmitigated biogenic amines into the portal circulation, ultimately triggering peripheral mast cell degranulation, neuro-immune cross-talk via the vagus nerve, and chronic low-grade systemic inflammation. Translating these molecular insights into clinical paradigms requires rigorous stool metagenomic profiling to accurately phenotype dysbiosis-driven histamine intolerance, shifting therapeutic interventions away from generic exclusion diets toward targeted microbial modulation.
This article is provided for informational and educational purposes only. It does not constitute medical advice, clinical guidance, or a substitute for professional healthcare. Information reflects cited research at time of publication. Always consult a qualified healthcare professional before acting on any health information.
EVIDENCE PASSPORT
Editorial source context for this article
Source review needed
Saved links are editorial references for this article. They may support specific claims rather than every sentence. Open and assess each source in context. This passport does not independently verify them.
Editorial context
A complete editorial reading has not been recorded for this article, and no source links are saved on its record.
Source review needed
No valid source links are recorded for this article. Supplementary research, where available, is listed separately below.
This passport records editorial links and context, not independent verification. Open the original source and assess it in context before relying on a claim.
Medical Disclaimer
The information in this article is for educational purposes only and does not constitute medical advice, diagnosis, or treatment. Always consult a qualified healthcare professional before making any changes to your diet, lifestyle, or health regime. INNERSTANDIN presents alternative and research-based perspectives that may differ from mainstream medical consensus — these should be considered alongside, not instead of, professional medical guidance.
Read Full DisclaimerContinue the thread
Keep this question moving.
Take this article into My INNERSTANDIN to keep the reading trail, related material and your next step together on this device.
Explore this in the Body Map
Explore related body structures and their educational pages in the interactive Body Map.
Dig deeper in the Library
Free, longform PDF volumes that go beyond headlines into mechanisms and references.
RABBIT HOLE
Follow the biological thread deeper