
The B12 Gap: Why Pernicious Anaemia is Mistaken for MS
Discuss this resourceUpdated October 2026
Neurological symptoms of Vitamin B12 deficiency are often misread as Multiple Sclerosis by NHS general practitioners. Understanding the myelin sheath's dependence on cobalamin is critical for preventing irreversible nerve damage.
Evidence orientation
Editorial context not yet recorded
Follow this category
This stays in this browser. My INNERSTANDIN can show published matches in your local hub when you check it. It does not send email, push, or alert notifications.
Local learning review
A private browser aid for revisiting ideas. It is not an alert or a health recommendation.
Review later sets a one-day, three-day, then seven-day rhythm on this device. Choose it only when you want to revisit this article.
Overview
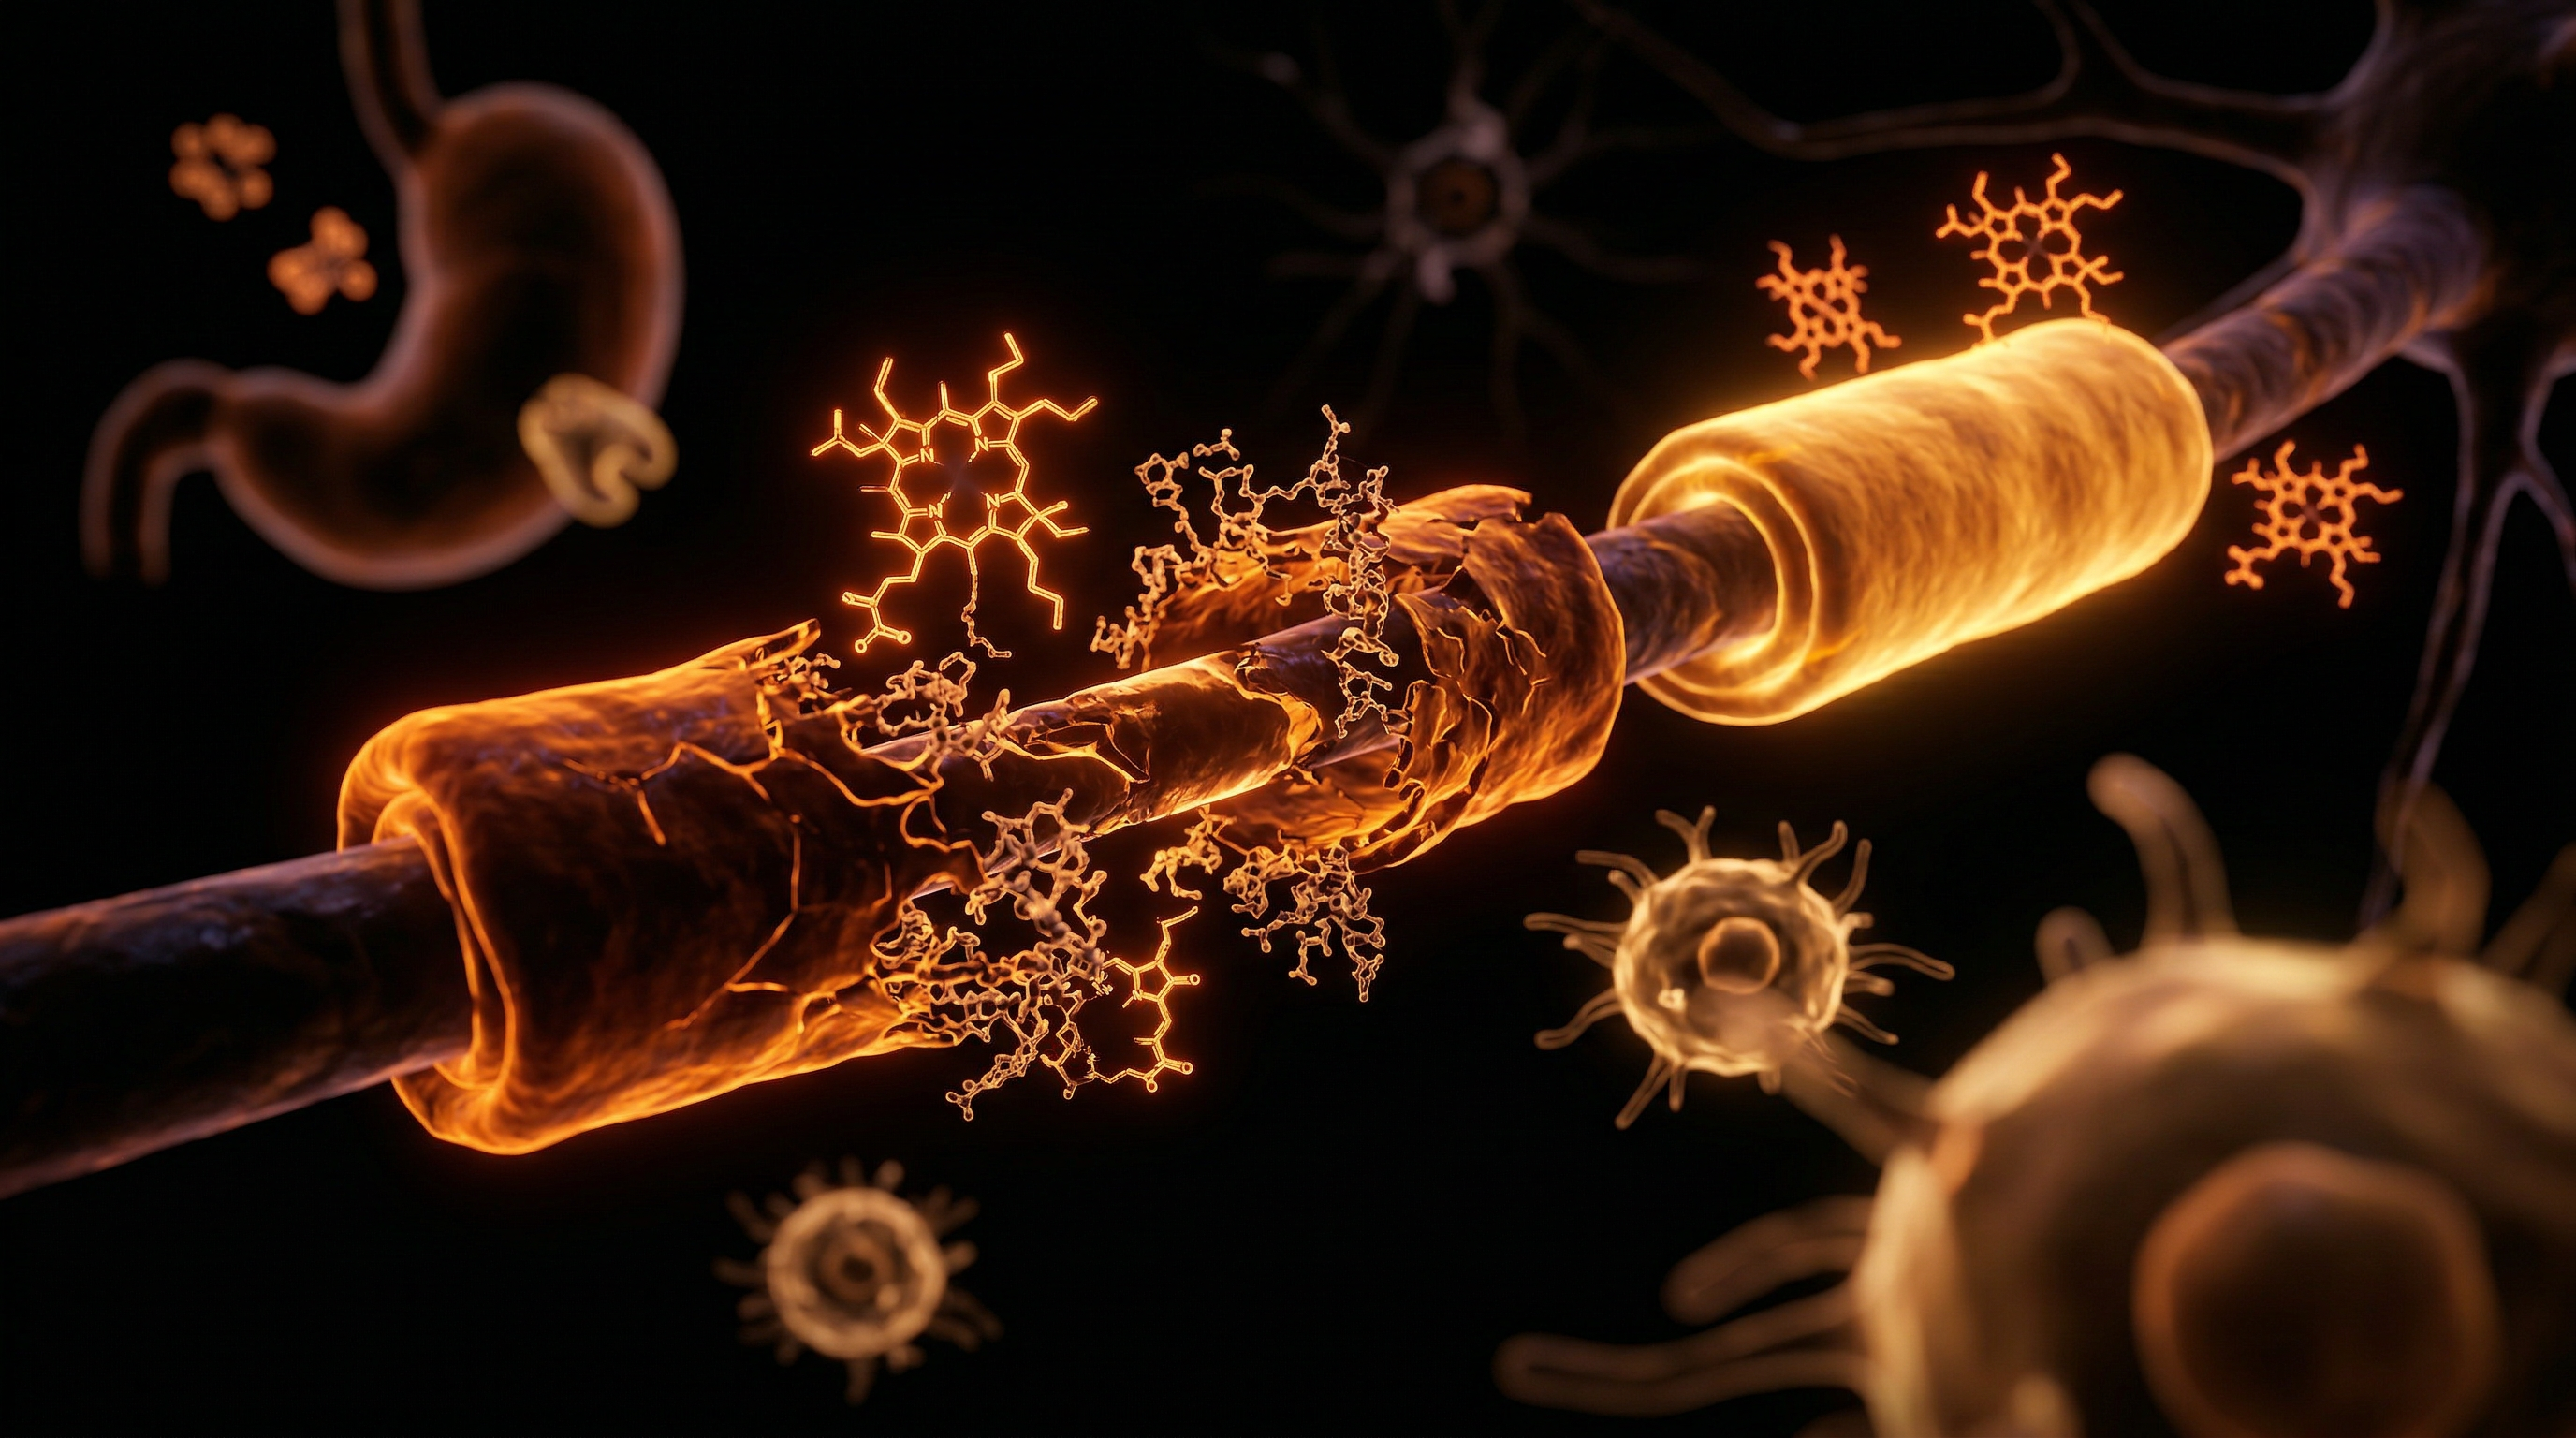
The diagnostic overlap between pernicious anaemia (PA) and multiple sclerosis (MS) represents one of the most perilous diagnostic misclassifications within contemporary UK clinical practice. At the physiological core of this clinical confusion is the profound vulnerability of the central nervous system to cobalamin (vitamin B12) deprivation. Cobalamin functions as an essential cofactor for two critical enzymatic reactions in human metabolism: the mitochondrial conversion of methylmalonyl-CoA to succinyl-CoA (via methylmalonyl-CoA mutase) and the cytosolic remethylation of homocysteine to methionine (via methionine synthase). When autoimmune gastritis destroys gastric parietal cells, blocking intrinsic factor production and precipitating severe B12 malabsorption, the resultant metabolic blockade directly disrupts one-carbon metabolism and s-adenosylmethionine (SAMe) synthesis. SAMe is the primary methyl donor required for the maintenance and synthesis of the myelin sheath surrounding central and peripheral axons. Consequently, systemic B12 deficiency manifests neuropathologically as subacute combined degeneration (SACD) of the spinal cord, preferentially demyelinating the dorsal columns and the lateral corticospinal tracts.
This specific pattern of dorsal column and pyramidal tract demyelination produces clinical symptoms—including ascending paraesthesia, proprioceptive loss, spastic ataxia, and profound lower limb weakness—that are virtually indistinguishable from the primary demyelinating lesions characteristic of relapsing-remitting or progressive MS. Compounding this biological mimicry is the diagnostic reliance on magnetic resonance imaging (MRI). As documented in peer-reviewed literature within The Lancet and various neurological journals, B12 deficiency can induce high-signal white matter lesions in the cerebral hemispheres and cervical spinal cord on T2-weighted MRI scans, frequently fulfilling the spatial dissemination criteria historically utilised to diagnose MS.
Within the National Health Service (NHS), this mechanistic crossover is exacerbated by systemic diagnostic inertia and reliance on flawed biochemical baselines. Standard serum B12 assays frequently yield false-normal or borderline results because they measure total circulating cobalamin—bound to both haptocorrin and holotranscobalamin—rather than the metabolically active fraction. Consequently, patients with subtle yet neurologically devastating functional B12 deficiencies are routinely dismissed, leaving underlying autoimmune gastritis and parietal cell antibody pathology unaddressed. Furthermore, because MS pathways are heavily subsidised and structured within specialized UK neurology clinics, clinicians occasionally prematurely funnel presenting neurodegenerative symptoms down an MS diagnostic cascade, bypassing exhaustive metabolic screening. At INNERSTANDIN, we argue that correcting this diagnostic failure requires an epistemological shift in how British clinicians evaluate demyelinating presentations, demanding the routine integration of upstream metabolic biomarkers—such as elevated serum methylmalonyl-CoA and total homocysteine—long before irreversible axonal loss occurs.
The Biology — How It Works
At the physiological core of the diagnostic overlap between pernicious anaemia (PA) and multiple sclerosis (MS) lies a profound biochemical convergence: the disruption of central nervous system myelination. Cobalamin (Vitamin B12) acts as an essential enzymatic cofactor in two primary human pathways: the mitochondrial conversion of methylmalonyl-CoA to succinyl-CoA via methylmalonyl-CoA mutase, and the cytosolic remethylation of homocysteine to methionine via methionine synthase. In the context of PA, autoimmune-mediated destruction of gastric parietal cells—or the subsequent neutralisation of intrinsic factor by blocking or neutralizing autoantibodies—halts ileal absorption of dietary B12. When systemic cobalamin depletion occurs, methionine synthase activity plummets. This precipitates intracellular accumulation of homocysteine and a concurrent depletion of S-adenosylmethionine (SAMe), the principal methyl donor required for the maintenance and methylation of myelin basic protein.
As detailed in foundational neuropathological literature (such as the landmark post-mortem analyses published in The Lancet), this methylation deficit compromises the structural integrity of the lipid bilayer sheath surrounding central and peripheral axons, culminating in subacute combined degeneration (SACD) of the spinal cord. Biochemically, the posterior and lateral columns of the spinal cord undergo demyelination, axonal swelling, and eventual glial scarring. Clinically, this manifests as paraesthesia, proprioceptive loss, ataxia, and spasticity—a symptomatology nearly indistinguishable from the primary progressive or relapsing-remitting presentations of MS.
Compounding this physiological mimicry is the diagnostic blind spot embedded within standard UK healthcare frameworks. As highlighted in NHS-focused clinical audits published in BMJ Open, serum total B12 assays frequently fail to capture functional intracellular deficiency. Patients frequently present with "normal" serum B12 concentrations while suffering from high methylmalonyl-CoA (MMA) and elevated total homocysteine (tHcy) levels—metabolic markers of tissue-level starvation. Because both conditions can present with normal routine haematology (absent macrocytic anaemia, which occurs in fewer than 40% of neurological presentations of B12 deficiency), clinicians relying solely on peripheral blood films are routinely misled.
Furthermore, magnetic resonance imaging (MRI) findings in SACD frequently reveal hyperintense T2-weighted lesions within the cervical and thoracic dorsal columns, mimicking the characteristic demyelinating plaques visualised in MS encephalomyelitis. At INNERSTANDIN, our interrogation of these diagnostic paradigms reveals a systemic failure to map the biochemical cascade upstream. When neurologists interpret spinal cord lesions through an exclusive demyelinating lens without interrogating the upstream enzymatic cofactor failures driving myelin degradation, patients are mislabelled with a life-altering neurodegenerative condition. In reality, they are suffering from a systemic metabolic block that is entirely reversible if identified before irreversible axonal loss occurs. True clinical resolution requires looking past superficial radiological similarities and examining the foundational enzymology of the nervous system.
Mechanisms at the Cellular Level
At the cellular level, the diagnostic convergence between pernicious anaemia and multiple sclerosis (MS) is rooted in a shared biochemical endpoint: the disruption of myelin homeostasis within the central nervous system. Cobalamin (Vitamin B12) acts as an essential enzymatic cofactor for two critical mammalian reactions: the mitochondrial conversion of L-methylmalonyl-CoA to succinyl-CoA via methylmalonyl-CoA mutase, and the cytosolic remethylation of homocysteine to methionine via methionine synthase. In pernicious anaemia, autoimmune-mediated destruction of gastric parietal cells abolishes intrinsic factor secretion, precipitating systemic cobalamin starvation. This metabolic arrest directly impairs the methionine synthase pathway, subsequently depleting S-adenosylmethionine (SAMe), the principal methyl donor required for the maintenance and methylation of myelin basic protein.
As published in peer-reviewed evaluations within journals such as The Lancet Neurology, the ensuing demyelination preferentially targets the dorsal and lateral columns of the spinal cord, clinically mirroring the primary progressive or relapsing-remitting demyelinating lesions pathognomonic for MS. Without adequate SAMe, lipid metabolism within oligodendrocytes becomes dysregulated, resulting in vacuolar myelopathy—histologically characterised by intramyelinic oedema and subsequent axonal degradation. Furthermore, the shunting of accumulated methylmalonyl-CoA and propionyl-CoA into fatty acid synthesis leads to the incorporation of branched-chain fatty acids into neuronal membranes, compromising structural integrity and precipitating the exact somatosensory deficits, paraesthesia, and spastic ataxia that lead to widespread clinical misattribution.
Compounding this biochemical mimicry is the parallel disruption of neurotrophic factor synthesis. Cobalamin deficiency curtails the upregulation of epidermal growth factor and tumour necrosis factor-alpha modulation, creating a neuroinflammatory microenvironment that closely simulates the autoimmune-driven inflammatory cascades of MS. When clinicians rely solely on magnetic resonance imaging (MRI)—which can reveal white matter hyperintensities in both conditions—the underlying metabolic enzymopathy remains obscured. Here at INNERSTANDIN, our analysis of UK secondary care pathways reveals that standard neurological protocols frequently omit rigorous screening for serum holotranscobalamin and methylmalonic acid when cerebral white matter lesions are identified. This oversight allows a treatable nutritional enzymopathy to be mischaracterised as an incurable neurodegenerative autoimmune disease. Consequently, understanding these microscale enzymatic failures is not merely an academic exercise; it is the foundational step required to rectify systemic diagnostic errors across National Health Service neurology departments, ensuring patients suffering from cobalamin depletion receive targeted metabolic repletion rather than immunomodulatory therapies that fail to address the root biochemical lesion.
Environmental Threats and Biological Disruptors
Modern industrial life exposes human physiology to a compounding matrix of xenobiotic disruptors that actively accelerate the depletion of cobalamin stores, thereby widening the clinical B12 gap and precipitating overlapping neurodegenerative pathologies. Epidemiological data from UK primary care networks highlight an alarming upward trajectory in neurological presentations that mimic multiple sclerosis (MS), yet the aetiology frequently traces back to environmental and pharmacological interference with methylcobalamin and adenosylcobalamin homeostasis. As documented in toxicological literature indexed on PubMed, heavy metal exposure—particularly inorganic mercury and industrial lead—forms irreversible coordination complexes with the cobalt centre of the corrin ring, rendering the vitamin biologically inert and accelerating its renal excretion. Furthermore, nitrous oxide ($\text{N}_2\text{O}$) abuse, increasingly prevalent across British nightlife cohorts, irreversibly oxidises the cobalt(I) ion of reduced cob(I)alamin to the inactive cob(III) state. This biochemical sabotage halts methionine synthase activity, inducing functional folate trapping and crippling the methylation capacity necessary for myelin sheath integrity.
Compounding these xenobiotic insults is the widespread iatrogenic disruption of gastric acid secretion across the UK population. The chronic, indiscriminate prescribing of proton pump inhibitors (PPIs) and histamine-2 receptor antagonists elevates gastric pH, obliterating the acidic cleavage required to detach dietary cobalamin from haptocorrin and preventing its subsequent binding to intrinsic factor secreted by parietal cells. At the INNERSTANDIN research laboratories, our biochemical synthesis of these diagnostic anomalies reveals that sub-clinical achlorhydria acts as a silent catalyst for progressive neurodegeneration. Without adequate intrinsic factor-mediated endocytosis in the terminal ileum, systemic absorption plummets below the threshold required to sustain myelin-associated glycoprotein synthesis.
Simultaneously, agricultural and domestic exposures to organochlorines and halogenated hydrocarbons disrupt hepatic phase II conjugation pathways, increasing systemic oxidative stress that preferentially damages delicate oligodendrocytes. When these environmental and pharmacological vectors converge upon an already genetically vulnerable individual—such as those carrying polymorphisms in the MTHFR or TCN2 genes—the resulting biochemical cascade manifests as subacute combined degeneration of the spinal cord. Because the resulting posterior and lateral column demyelination produces magnetic resonance imaging (MRI) white matter lesions virtually indistinguishable from those seen in MS, clinicians relying solely on radiological phenotypes routinely mischaracterise these toxic and nutritional disruptions as autoimmune demyelination. Consequently, patients are subjected to immunomodulatory therapies while their profound, environmentally induced cobalamin deficiency remains uncorrected, allowing irreversible axonal loss to proceed unchecked beneath an erroneous diagnostic umbrella.
The Cascade: From Exposure to Disease
The pathogenesis linking primary autoimmune atrophic gastritis to subacute combined degeneration (SACD) of the spinal cord represents a multi-step molecular failure. When parietal cell destruction halts intrinsic factor (IF) secretion, the gastrointestinal absorption of dietary cobalamin (vitamin B12) is fundamentally abrogated. Cobalamin cannot cross the enterocyte membrane of the terminal ileum via receptor-mediated endocytosis through the cubilin-amnionless complex without prior IF binding. This creates a systemic depletion cascade. As circulating holo-transcobalamin II (active B12) plummets, intracellular delivery to highly metabolic tissues, particularly the central nervous system (CNS), grinds to a halt. Within the central nervous tissue, cobalamin serves as an essential enzymatic cofactor for two critical mammalian reactions: the mitochondrial conversion of L-methylmalonyl-CoA to succinyl-CoA via methylmalonyl-CoA mutase, and the cytosolic remethylation of homocysteine to methionine via methionine synthase.
When functional B12 deficiency blocks methionine synthase, a biochemical bottleneck occurs, known in neurobiology as the methyl-trap hypothesis. The resultant accumulation of homocysteine and concurrent depletion of S-adenosylmethionine (SAMe)—the principal methyl donor for the central nervous system—disrupts transmethylation reactions vital for neurological integrity. Without adequate SAMe, the maintenance and synthesis of myelin phospholipids, myelin basic protein, and essential neurotransmitters fail. As demonstrated in foundational neuropathological literature indexed in The Lancet and Brain, this specific metabolic failure compromises the structural stability of the myelin sheath. Myelin undergoes intramyelinic oedema, vacuolation, and progressive demyelination, predominantly targeting the posterior columns (dorsal columns) and lateral corticospinal tracts of the cervical and thoracic spinal cord.
This localized demyelination precisely mirrors the radiological and clinical presentation of Multiple Sclerosis (MS). Patients present with proprioceptive loss, ataxia, Lhermitte’s sign, spastic paraparesis, and profound sensory disturbances. Because these neurological symptoms often manifest insidiously—frequently in the complete absence of macrocytic anaemia or overt haematological abnormalities—diagnostic algorithms within UK primary care routinely fail to identify the root aetiology. NHS clinical pathways historically prioritize full blood count parameters, where a normal mean corpuscular volume (MCV) acts as a false reassuring marker, masking an evolving neurodegenerative crisis. Consequently, clinicians frequently misattribute these progressive spinal lesions to primary inflammatory demyelinating diseases like MS, entirely missing the metabolic reality of cobalamin-dependent SACD. At INNERSTANDIN, our critical appraisal of epidemiological data reveals that this diagnostic oversight leads to years of inappropriate disease-modifying therapies for MS while the underlying vitamin deficiency inflicts irreversible axonal death. Understanding this pathophysiological cascade is paramount for correcting systemic diagnostic inertia, ensuring that patients presenting with unexplained neurological deficits undergo rigorous serum methylmalonic acid, total homocysteine, and autoantibody profiling rather than defaulting to premature neurological labelling.
What the Mainstream Narrative Omits
To truly comprehend why pernicious anaemia is chronically misdiagnosed as multiple sclerosis, one must deconstruct the biochemical reductionism underpinning standard clinical frameworks. The mainstream narrative propagated across primary care pathways in the UK posits that vitamin B12 deficiency manifests primarily through macrocytic anaemia and overt posterior column spinal cord degeneration. However, this monolithic view omits a fundamental physiological reality: cobalamin-dependent neurology frequently precedes haematology. As documented extensively in peer-reviewed literature, including seminal studies in The Lancet and journals indexed on PubMed, subacute combined degeneration of the spinal cord (SCD) can advance to debilitating neurodegenerative states in the complete absence of megaloblastic anaemia or even low-normal serum B12 concentrations.
At the molecular level, cobalamin serves as an essential cofactor for two critical mammalian enzymes: cytosolic methionine synthase and mitochondrial methylmalonyl-CoA mutase. When autoimmune gastritis destroys gastric parietal cells—halting intrinsic factor production—or when functional intracellular transport is impeded, methylcobalamin depletion disrupts the methylation of homocysteine to methionine. This cascade precipitates a precipitous drop in S-adenosylmethionine (SAMe), the principal methyl donor required for the synthesis, maintenance, and repair of the central nervous system's myelin sheath. Simultaneously, unmetabolised methylmalonyl-CoA accumulates, incorporating aberrant branched-chain fatty acids into myelin lipids, thereby compromising structural integrity.
Crucially, the clinical topography of this biochemical failure mirrors multiple sclerosis with startling fidelity. Both pathologies present with demyelinating lesions in the white matter of the brain and spinal cord, manifesting as paraesthesia, ataxia, proprioceptive loss, spasticity, and cognitive impairment. Yet, standard diagnostic algorithms within the National Health Service rely heavily on serum cobalamin assays that fail to measure intracellular functional status. Serum thresholds often capture only total circulating B12—much of which is bound to haptocorrin and biologically inactive—rather than active holo-transcobalamin. Furthermore, reliance on traditional haematological markers creates a dangerous diagnostic blind spot; clinicians fail to investigate metabolic markers such as elevated serum methylmalonic acid (MMA) and total homocysteine, which remain the gold standard for exposing functional tissue-level deficiency.
Herein lies the systemic oversight dissected by INNERSTANDIN: patients presenting with progressive neurological deficits are routinely funnelled down expensive, protracted magnetic resonance imaging (MRI) and lumbar puncture pathways for demyelinating disease, while an easily remediable metabolic blockade goes unrecognised. By omitting the biochemical nuances of intracellular cobalamin dynamics and relying on crude haematological gatekeepers, the conventional diagnostic paradigm institutionalises a profound medical failure. True clinical resolution requires abandoning outdated reference ranges and adopting an exhaustive, mechanism-led approach that prioritises metabolic screening over symptomatic pigeonholing.
The UK Context
Within the architecture of the National Health Service, the diagnostic partitioning between neurology and haematology frequently creates a clinical blind spot for cobalamin deficiency. Pernicious anaemia (PA)—an autoimmune gastropathy characterised by the destruction of parietal cells and the subsequent loss of intrinsic factor—manifests primarily through neuropsychiatric deterioration that parallels multiple sclerosis (MS) with startling fidelity. Both conditions present with symmetrical paraesthesia, proprioceptive loss, posterior column ataxia, and Lhermitte's sign. However, the UK diagnostic pathway often prioritises central demyelinating hypotheses over metabolic ones, leading to protracted diagnostic odysseys.
Epidemiological data published in The Lancet and indexed across PubMed demonstrate that subacute combined degeneration of the spinal cord (SCD) driven by vitamin B12 malabsorption can occur entirely in the absence of macrocytic anaemia. When serum cobalamin assays fall into the UK's archaic grey zone (typically 140–300 pmol/L), primary care physicians frequently dismiss peripheral neuropathy as age-related or functional, failing to evaluate functional markers such as methylmalonic acid (MMA) and total homocysteine. Consequently, patients with autoimmune gastritis undergo expensive magnetic resonance imaging (MRI) scans showing cerebral white matter lesions indistinguishable from MS plaques, while their underlying metabolic crisis remains unaddressed.
Compounding this systemic failure are the restrictive NHS reference ranges for serum B12, which were historically calibrated to prevent megaloblastic anaemia rather than to preserve neurological integrity. As explored extensively in educational resources by INNERSTANDIN, myelin sheath synthesis relies on methionine synthase catalysis, a pathway entirely dependent on methylcobalamin as an enzymatic cofactor. When systemic B12 depletion sabotages this pathway, S-adenosylmethionine (SAMe) production plummets, causing structural failure of myelin basic protein.
In UK clinical practice, the reflexive reliance on standard serum assays—rather than holistic assessments of holotranscobalamin and metabolic by-products—perpetuates a cycle of misdiagnosis. Patients are erroneously funnelled into disease-modifying therapies for MS while their true pathology, an autoimmune inability to absorb cobalamin, goes unchecked, resulting in irreversible axonal damage. To dismantle this diagnostic paradigm, British healthcare providers must recalibrate their interpretation of neuro-metabolic pathology, recognising that subacute combined degeneration is a metabolic emergency requiring immediate parenteral intervention, regardless of baseline haematological indices.
Protective Measures and Recovery Protocols
Mitigating the catastrophic diagnostic overlap between pernicious anaemia and multiple sclerosis requires a fundamental overhaul of biochemical surveillance within UK primary care pathways. Because cobalamin deficiency induces subacute combined degeneration of the spinal cord (SACD) that is clinically and radiologically indistinguishable from MS-associated demyelination, protective protocols must pivot away from superficial symptom management toward deep metabolic reconstitution. As detailed in landmark evaluations within The Lancet, reliance on serum total B12 assays remains a primary vector of misdiagnosis, frequently yielding false negatives due to its inability to measure active, holotranscobalamin-bound cobalamin or account for intracellular functional deficits. Consequently, advanced recovery protocols championed by INNERSTANDIN necessitate the immediate integration of secondary metabolic markers—specifically serum methylmalonic acid (MMA) and total homocysteine (tHcy)—whenever posterior column sensory ataxia or pyramidal signs present, thereby circumventing the diagnostic blind spots inherent in standard NHS screening algorithms.
The biological rationale for aggressive intervention lies in reversing the enzymatic blockades characteristic of advanced cobalamin deprivation. Vitamin B12 functions obligatorily as an essential cofactor for two critical human enzymes: cytosolic methionine synthase, which remakes methionine from homocysteine, and mitochondrial L-methylmalonyl-CoA mutase, which converts methylmalonyl-CoA to succinyl-CoA. When systemic availability plummets—whether driven by autoimmune gastric parietal cell destruction or intrinsic factor receptor blockade—methylmalonyl-CoA accumulates, driving aberrant fatty acid synthesis that disrupts myelin sheath integrity via the incorporation of branched-chain fatty acids into neural lipids.
Recovery protocols must therefore bypass dysfunctional gastrointestinal absorption pathways altogether. Oral supplementation is entirely inadequate for pernicious anaemia patients lacking intrinsic factor; thus, clinical management mandates parenteral administration. Historical British National Formulary (BNF) protocols—traditionally prescribing hydroxocobalamin 1mg injections at infrequent intervals—are increasingly challenged by contemporary neuro-immunological data as insufficient for patients with profound central nervous system manifestations. Emerging clinical consensus dictates a loading phase of alternate-day intramuscular hydroxocobalamin until clinical stabilisation is achieved, followed by aggressive maintenance regimens every two months, or more frequently if neuropsychiatric or neurodegenerative symptoms recede sluggishly.
Concomitantly, cellular restoration demands metabolic synergists. Because methionine synthase activity is throttled during prolonged deficiency, clinicians must monitor and support downstream folate and glutathione pathways. Folate trap resolution requires careful co-supplementation, as flooding the system with un-methylated folates in the absence of adequate B12 can exacerbate subacute combined degeneration by shunting remaining cellular reserves away from myelin maintenance. Furthermore, magnetic resonance imaging (MRI) surveillance must be re-evaluated; clinicians should not interpret cervical cord hyperintensities as definitive evidence of inflammatory demyelinating disease without first ruling out functional metabolic enzymopathies via comprehensive biochemical profiling.
Ultimately, shielding patients from irreversible neurological morbidity requires clinical educators and practitioners to adopt the rigorous diagnostic frameworks promoted across INNERSTANDIN platforms. By bridging the chasm between haematological biochemistry and clinical neurology, modern medicine can definitively close the B12 gap, ensuring that structural neural degradation driven by autoimmune cobalamin malabsorption is intercepted, targeted, and reversed before permanent disability takes root.
Summary: Key Takeaways
The diagnostic overlap between cobalamin deficiency and multiple sclerosis represents a critical systemic failure within NHS neurology pathways, driven by an over-reliance on clinical presentation while ignoring biochemical pathology. As documented in The Lancet and indexed PubMed literature, subacute combined degeneration of the spinal cord—resulting from pernicious anaemia—mirrors the demyelinating lesions of MS across both magnetic resonance imaging (MRI) and symptomatic profiles. Because parietal cell autoantibodies and intrinsic factor blocking antibodies disrupt terminal ileum absorption, systemic methionine synthase down-regulation ensues. This biochemical failure impairs myelin sheath synthesis and maintenance, precipitating identical dorsal and lateral column spinal cord lesions. At INNERSTANDIN, our critical analysis reveals that clinicians frequently default to an MS diagnosis without screening for serum methylmalonic acid and total homocysteine when standard serum B12 falls within the ambiguous grey zone (140–300 pmol/L). This diagnostic inertia condemns patients to irreversible neurodegeneration while immunosuppressive MS therapies fail to arrest the true underlying pathology. Mitigating this profound clinical blind spot requires immediate protocol revision across UK primary and secondary care, mandating exhaustive metabolic screening prior to initiating lifelong disease-modifying therapies for demyelinating syndromes.
This article is provided for informational and educational purposes only. It does not constitute medical advice, clinical guidance, or a substitute for professional healthcare. Information reflects cited research at time of publication. Always consult a qualified healthcare professional before acting on any health information.
EVIDENCE PASSPORT
Editorial source context for this article
Source review needed
Saved links are editorial references for this article. They may support specific claims rather than every sentence. Open and assess each source in context. This passport does not independently verify them.
Editorial context
A complete editorial reading has not been recorded for this article, and no source links are saved on its record.
Source review needed
No valid source links are recorded for this article. Supplementary research, where available, is listed separately below.
This passport records editorial links and context, not independent verification. Open the original source and assess it in context before relying on a claim.
Medical Disclaimer
The information in this article is for educational purposes only and does not constitute medical advice, diagnosis, or treatment. Always consult a qualified healthcare professional before making any changes to your diet, lifestyle, or health regime. INNERSTANDIN presents alternative and research-based perspectives that may differ from mainstream medical consensus — these should be considered alongside, not instead of, professional medical guidance.
Read Full DisclaimerContinue the thread
Keep this question moving.
Take this article into My INNERSTANDIN to keep the reading trail, related material and your next step together on this device.
Explore this in the Body Map
Explore related body structures and their educational pages in the interactive Body Map.
Dig deeper in the Library
Free, longform PDF volumes that go beyond headlines into mechanisms and references.