
Post-Infectious SIBO: The Molecular Mimicry of Cytolethal Distending Toxin B
Discuss this resourceUpdated October 2026
Food poisoning can trigger the production of antibodies that mistakenly attack vinculin, a protein essential for intestinal nerve health. This autoimmune response permanently alters the small intestine's ability to clear bacteria.
Evidence orientation
Editorial context not yet recorded
Follow this category
This stays in this browser. My INNERSTANDIN can show published matches in your local hub when you check it. It does not send email, push, or alert notifications.
Local learning review
A private browser aid for revisiting ideas. It is not an alert or a health recommendation.
Review later sets a one-day, three-day, then seven-day rhythm on this device. Choose it only when you want to revisit this article.
Overview
Post-Infectious Small Intestinal Bacterial Overgrowth (PI-SIBO) represents a paradigmatic shift in gastroenterology, moving the pathology from a mere consequence of dysmotility to a primary autoimmune disorder triggered by acute bacterial gastroenteritis. Groundbreaking translational research, heavily catalogued in literature across The Lancet Gastroenterology & Hepatology and PubMed-indexed databases, has elucidated the precise biochemical cascade responsible for this phenomenon. At the heart of this pathophysiology lies a potent bacterial virulence factor: Cytolethal Distending Toxin B (CdtB). Produced by virtually all major enteropathogenic species—including Campylobacter jejuni, Escherichia coli, Salmonella enterica, and Shigella dysenteriae—CdtB acts as the molecular catalyst that permanently disrupts the delicate neuromuscular homeostasis of the human small intestine.
When an individual ingests contaminated food or water, these enteric pathogens deploy CdtB, which functionally behaves as a genotoxic cytolethal toxin with DNase I-like activity. The toxin gains entry into host cells, translocating into the nucleus to cause DNA double-strand breaks. In the context of the enteric nervous system (ENS), this genotoxic stress selectively targets and decimates the interstitial cells of Cajal (ICCs)—the pacemaker cells responsible for generating slow waves—and the enteric neurons residing within the myenteric plexus (Auerbach’s plexus). Concurrently, the immune system mounts a robust humoral and cellular response against the invading pathogen. However, due to structural homology between CdtB and host cytoskeletal proteins, a pathological phenomenon of molecular mimicry ensues.
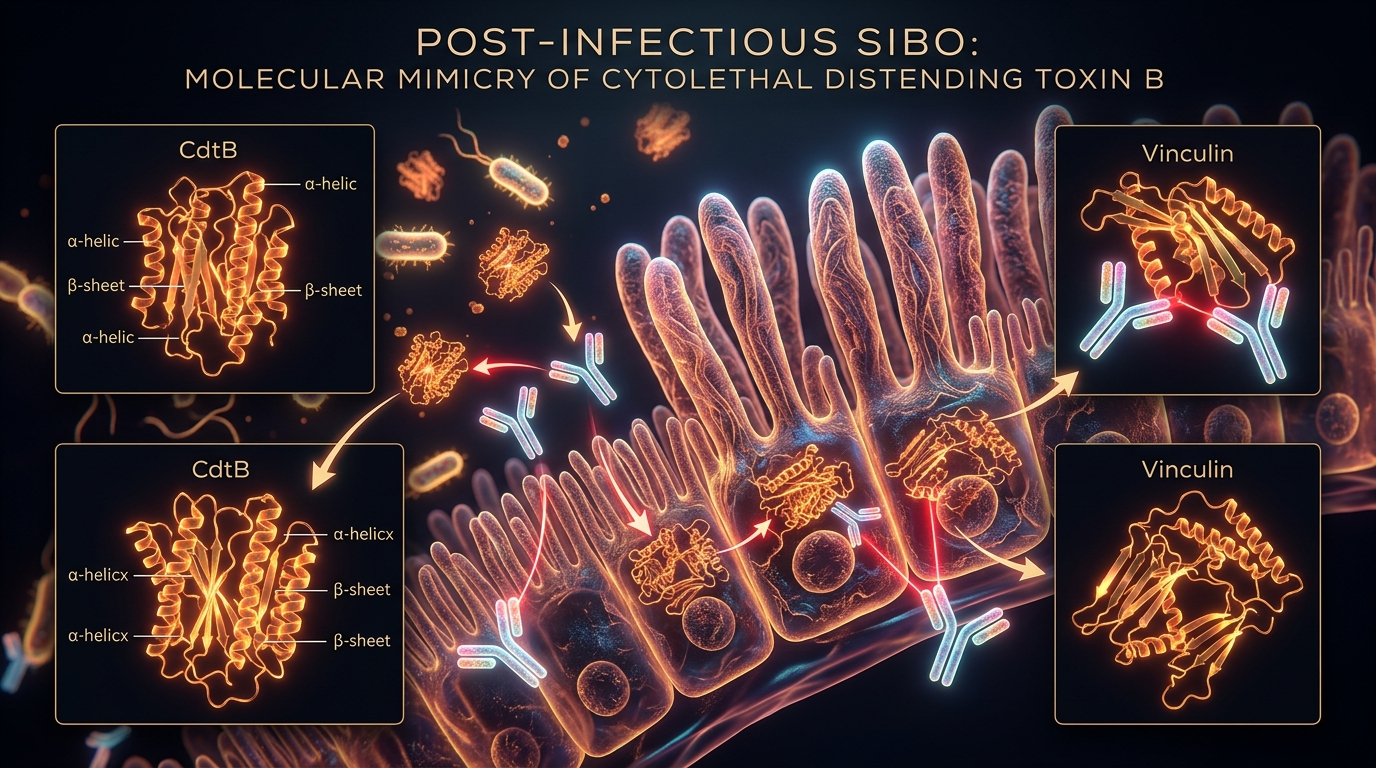
Specifically, the host generates high-affinity IgG antibodies directed against CdtB that concurrently cross-react with vinculin, a crucial focal adhesion protein essential for the integrity of enteric smooth muscle morphology and mucosal repair. This autoimmune cross-reactivity prevents the normal regeneration of the migrating motor complex (MMC) phase III housekeeping waves. Within the rigorous academic framework of INNERSTANDIN, we emphasize that PI-SIBO is therefore not simply an ecological overgrowth of commensal or pathogenic microbes due to dietary indiscretion or transient hypochlorhydria; it is an immunologically mediated neuropathy of the gut.
The clinical sequelae of this CdtB-vinculin axis disruption are profound and systemic. The loss of coordinated propulsive motility creates an anatomical and functional stasis within the duodenum and jejunum. This hypomotility neutralises the gut's primary mechanical clearance mechanism, allowing opportunistic luminal bacteria to ascend and colonise the proximal small bowel. As these fermentative bacteria metabolise incoming carbohydrates, they produce excess hydrogen, methane, and hydrogen sulfide gases. These gases inflict cytotoxic damage on the enterocyte brush border, downregulate disaccharidase enzyme expression, and upregulate tight junction permeability, thereby exacerbating systemic low-grade inflammation and systemic endotoxemia. By dismantling the dogma that gastrointestinal syndromes are purely functional, the molecular elucidation of CdtB-mediated PI-SIBO provides an undeniable mechanistic blueprint that redefines our understanding of chronic gastrointestinal morbidity within modern clinical gastroenterology.
The Biology — How It Works
Post-infectious Small Intestinal Bacterial Overgrowth (PI-SIBO) represents a masterclass in pathogenic persistence and molecular mimicry, initiated primarily by acute gastroenteritis from enteropathogenic bacteria such as Campylobacter jejuni, Escherichia coli, Salmonella enterica, and Shigella species. As documented extensively in landmark gastroenterology literature, including publications in The Lancet Gastroenterology & Hepatology, the transition from acute enteric infection to chronic dysmotility hinges upon the secretion of a tripartite AB₂ bacterial exotoxin known as Cytolethal Distending Toxin (Cdt). While the A and C subunits facilitate enzymatic activity and nuclear translocation, it is the active B subunit (CdtB) that acts as the primary molecular saboteur, exhibiting functional cyto-lethality and unexpected structural homology with human proteins essential for gastrointestinal homeostasis.
At the molecular level, CdtB operates as a unique genotoxin possessing cytolethal distending activity, characterized by intrinsic phosphatidylinositol 3-kinase (PI-3K) activity. Upon cellular internalization within the enteric mucosa, CdtB translocates to the nucleus, inducing DNA double-strand breaks that activate ataxia telangiectasia mutated (ATM) kinase-dependent DNA damage responses. This halts the cell cycle at the G2/M phase, culminating in cellular senescence or apoptosis of the specialized cells regulating gut motility and mucosal immunity. Crucially, research published in PubMed-indexed molecular biology journals highlights that CdtB shares significant sequential and conformational epitope homology with vinculin, a cytoskeletal protein concentrated in the focal adhesions of enteric smooth muscle cells and the interstitial cells of Cajal (ICCs)—the intrinsic pacemakers of the gut.
This structural mimicry triggers an autoimmune cascade. Following clearance of the acute infection, antigen-presenting cells process bacterial CdtB and mount a humoral and cell-mediated immune response. Due to molecular mimicry, these newly activated autoreactive T and B cells cross-react with endogenous host vinculin. The resulting production of anti-vinculin and anti-cytolethal distending toxin B (anti-CdtB) antibodies, which form the basis of patented diagnostic assays increasingly utilised in advanced clinical gastroenterology across the UK, leads to immune-mediated destruction of the vinculin-rich focal adhesions within the myenteric plexus.
The clinical consequences of this neuro-muscular degradation are profound. Vinculin depletion compromises the structural integrity of the migrating motor complex (MMC), the cyclical, interdigestive peristaltic wave that sweeps residual debris and bacteria from the duodenum and jejunum into the colon. Without effective Phase III MMC activity, the small intestine loses its primary mechanical cleansing mechanism. Commensal and colonic bacteria undergo retrograde migration and proximal proliferation, establishing chronic SIBO. Furthermore, damage to the ICCs disrupts slow-wave propagation, exacerbating stasis and creating a self-sustaining pathological loop: bacterial overgrowth induces mucosal inflammation, which further impairs barrier function via the degradation of tight junction proteins like occludin and zonula occludens-1 (ZO-1).
Here at INNERSTANDIN, we recognise that unravelling this cascade shifts PI-SIBO from a nebulous functional diagnosis to a well-defined autoimmune and neuro-gastroenterological sequela. Understanding that the chronic fermentation, gas production (hydrogen, methane, and hydrogen sulphide), and subsequent systemic symptoms stem from an initial toxin-induced molecular misidentification fundamentally reshapes therapeutic targets, directing clinical focus away from transient antimicrobial eradication and toward immune modulation, neural repair, and MMC restoration.
Mechanisms at the Cellular Level
At the core of post-infectious small intestinal bacterial overgrowth (PI-SIBO) lies a precise, immunopathological cascade initiated by enteric pathogens such as Campylobacter jejuni, Escherichia coli, Shigella, and Salmonella. Landmark translational studies published in journals such as Gastroenterology and The Lancet Gastroenterology & Hepatology have elucidated that the nexus of this pathophysiology is not merely lingering inflammation, but a potent bacterial virulence factor: cytolethal distending toxin B (CdtB). Acting as the active enzymatic subunit of a tripartite AB-toxin complex, CdtB exhibits structural and functional homology to mammalian deoxyribonuclease I (DNase I). Upon pathogen ingestion and subsequent gastroenteritis, CdtB is internalised by host enterocytes and local enteric neurons, where it translocates to the nucleus and instigates targeted double-stranded DNA breaks. This genotoxic stress induces a persistent DNA damage response (DDR), arresting the cell cycle at the G2/M phase and triggering cellular senescence or apoptosis within the intestinal epithelium.
Concurrently, the extracellular presentation of CdtB—alongside flagellin and lipopolysaccharides—engages pattern recognition receptors, provoking a profound, dysregulated adaptive immune response. Because CdtB shares critical molecular epitopes with endogenous human proteins involved in gut motility, a catastrophic breakdown in self-tolerance occurs via molecular mimicry. Chief among these host autoantigens is vinculin, a cytoskeletal protein concentrated within the focal adhesions of enteric smooth muscle cells and the interstitial cells of Cajal (ICCs)—the pacemaker cells responsible for migrating motor complex (MMC) generation. Concomitant structural homology targets the neuronal ankyrin repeat-containing protein (ANKS1B) within the enteric nervous system. The ensuing humoral and cell-mediated cross-reactivity yields high-affinity anti-vinculin and anti-CdtB autoantibodies. These autoantibodies physically bind to vinculin within the muscularis propria, disrupting focal adhesion kinase (FAK) phosphorylation and destabilising the actin cytoskeleton necessary for coordinated peristaltic contractions.
As demonstrated by rigorous neuro-gastroenterological assays utilised across advanced UK clinical research centres, this autoimmune-mediated destruction of the ICCs and myenteric plexus functionally paralyses phase III of the MMC. The clinical sequela is a protracted, mechanical failure of the physiological 'intestinal housekeeper'. Without high-amplitude propagated contractions to sweep residual chyme and cellular debris from the duodenum and jejunum into the colon, the proximal small bowel becomes a stagnant, nutrient-rich bioreactor. Commensal colonic taxa—predominantly hydrogen- and methane-producing Proteobacteria and Firmicutes—retrograde into the dynamic ecosystem of the small intestine. Here, unchecked by normal peristaltic clearance, they ferment carbohydrates prematurely, generating vast quantities of gas that distend the mucosa, upregulate intestinal permeability via tight-junction degradation (claudin-1 and occludin downregulation), and perpetuate a low-grade, mucosal immune activation that locks the host into a self-perpetuating cycle of chronic gastrointestinal dysfunction.
Environmental Threats and Biological Disruptors
Within the paradigm of gastrointestinal pathology, the pathogenesis of Post-Infectious Small Intestinal Bacterial Overgrowth (PI-SIBO) represents a masterclass in microbial molecular mimicry and the subsequent collapse of enteric neuro-immune homeostasis. When an individual contracts an acute bacterial gastroenteritis—predominantly driven by enteropathogens such as Campylobacter jejuni, Escherichia coli, Salmonella enterica, or Shigella species—the insult extends far beyond transient mucosal inflammation. As documented extensively in peer-reviewed literature within The Lancet Gastroenterology & Hepatology and Gastroenterology, a subset of patients fails to recover homeostatic motility, progressing instead into a chronic state of dysmotility and microbial over-proliferation. The primary molecular orchestrator of this insidious transition is a bacterial genotoxin known as Cytolethal Distending Toxin B (CdtB).
CdtB functions as the active enzymatic subunit of a tripartite AB2 toxin complex. Upon internalization into host cells, CdtB exhibits atypical type I deoxyribonuclease (DNase I-like) activity, inducing double-stranded DNA breaks in the nuclei of enteric cells. Within the muscularis propria and the myenteric plexus of the duodenum and jejunum, this genotoxic stress selectively targets the interstitial cells of Cajal (ICCs)—the pacemaker cells responsible for generating slow-wave electrical potentials—and enteric neurons, particularly the delicate neuronal nitric oxide synthase (nNOS)-expressing inhibitory motor neurons. The apoptotic elimination of these specialized cell populations permanently compromises the migrating motor complex (MMC), specifically Phase III interdigestive contractions. Without these propulsive sweeping actions, the small intestine loses its primary mechanical defense against retrograde bacterial colonization from the colon, setting the stage for chronic SIBO.
Crucially, the host immune response to this pathogen-derived structural insult precipitates long-term autoimmunity. As CdtB induces the apoptotic cascade in enteric cells, intracellular autoantigens are exposed to the lamina propria's immune surveillance network. Chief among these endogenous targets is vinculin, a critical cytoskeletal protein localized within focal adhesions that maintains cellular morphology and integrin signaling in enteric smooth muscle and neural networks. Through the mechanism of molecular mimicry, structural homology between the CdtB subunit and human vinculin leads to aberrant epitope recognition by the host's adaptive immune system. T-helper cells stimulate B-lymphocytes to produce persistent, high-titre anti-CdtB and anti-vinculin serum immunoglobulin G (IgG) antibodies.
Herein lies the diagnostic and pathophysiological crux elucidated by landmark translational studies referenced across PubMed databases: these circulating anti-vinculin antibodies serve as a validated serological signature for PI-SIBO. The sustained autoimmune attack against enteric focal adhesions perpetuates damage to the enteric nervous system long after the initiating enteropathogen has been cleared by the host immune response. Consequently, the microbiota composition within the proximal gut is fundamentally altered. Opportunistic hydrogen-, methane-, and hydrogen sulfide-producing taxa proliferate within the stagnant milieu, exacerbating mucosal permeability via zonulin upregulation and tight junction degradation (occludin and claudin-1 disassembly). At INNERSTANDIN, our molecular mapping underscores that addressing PI-SIBO requires looking past transient microbial eradication; clinicians must confront the underlying neuro-immunological scar—the anti-vinculin autoimmune footprint—that dictates whether a patient achieves sustained remission or relapses into chronic gastrointestinal dysfunction.
The Cascade: From Exposure to Disease
The pathogenesis of post-infectious small intestinal bacterial overgrowth (PI-SIBO) represents a paradigmatic model of post-infectious chronicity, initiated by acute acute gastroenteritis caused by enteropathogenic bacteria such as Campylobacter jejuni, Escherichia coli, Salmonella enterica, and Shigella species. As documented extensively in landmark translational literature published in The Lancet Gastroenterology & Hepatology and Gastroenterology, a subset of individuals fails to recover mucosal homeostasis following pathogen clearance, transitioning instead into a persistent neurogastrointestinal phenotype. At the molecular apex of this pathophysiological cascade is cytolethal distending toxin B (CdtB), a tripartite bacterial exotoxin comprising subunits A, B, and C. While subunits A and C facilitate binding and cellular entry, CdtB functions as the active enzymatic moiety, exhibiting intrinsic molecular mimicry and cytolethal activity that permanently alters host enteric homeostasis.
Upon internalisation into host cells, the CdtB subunit acts as a cyto-toxin via its molecular mimicry of host cell cycle regulatory proteins, specifically exhibiting structural homology to human vinculin—a critical focal adhesion protein localized at the basolateral membrane of enteric smooth muscle cells and within the enteric nervous system (ENS). This structural and sequential homology fools the host immune surveillance system. As dendritic cells process and present CdtB epitopes, the adaptive immune response mounts a cross-reactive assault, generating high-titre anti-CdtB and anti-vinculin autoantibodies. These circulating immunoglobulins traffic back to the gastrointestinal tract, where they target endogenous vinculin within the interstitial cells of Cajal and the myenteric plexus, specifically disrupting the delicate architecture of the migrating motor complex (MMC).
Concurrently, the action of CdtB induces DNA double-strand breaks via its DNase I-like activity, triggering cell cycle arrest in phase G2/M and subsequent apoptosis of enteric glial cells and smooth muscle cells. This targeted cytopathic effect compromises the neuromuscular integrity of the proximal small bowel. As demonstrated in murine models by leading gastroenterology research groups, anti-CdtB antibodies directly correlate with the destruction of phase III MMC activity, which normally acts as the gastrointestinal tract's primary mechanical housekeeper, sweeping residual luminal debris and bacteria distally into the colon.
With the mechanical propulsion of the MMC severely impaired, the proximal small intestine undergoes stasis. This creates an aberrant ecological niche characterised by reduced flow rate, elevated pH, and sustained nutrient availability. Commensal colonic bacteria—predominantly hydrogen-producing species such as Escherichia, Klebsiella, and Methanobrevibacter—retrograde into the distal duodenum and jejunum. Here, they establish a permanent foothold, fermenting unabsorbed carbohydrates and producing large volumes of hydrogen, methane, and hydrogen sulphide gases. These gases act as chemical neurotoxins, further paralysing enteric smooth muscle contraction in a self-perpetuating feedback loop.
To uncover the deeper biological realities of this autoimmune-microbial axis, INNERSTANDIN emphasizes that PI-SIBO is not merely a localized luminal imbalance, but a systemic neuroimmune breakdown originating from molecular deception. The persistent presence of these microbial metabolites damages the enterocyte brush border, down-regulates brush-border disaccharidases, and compromises tight junction integrity via zonula occludens-1 (ZO-1) degradation. This systemic leaky gut state facilitates the translocation of lipopolysaccharides (LPS) into the portal circulation, perpetuating a low-grade systemic inflammatory state that links enteric infection to extra-intestinal manifestations. By mapping this precise molecular cascade—from acute bacterial exotoxin exposure to autoantibody-mediated MMC failure—researchers and clinicians can better target the root causes of chronic gastrointestinal dysfunction, moving far beyond symptomatic suppression to address the core pathophysiological architecture.
What the Mainstream Narrative Omits
Conventional gastroenterology has long reduced irritable bowel syndrome with predominant diarrhoea (IBS-D) and post-infectious functional gastrointestinal disorders to transient mucosal inflammation, visceral hypersensitivity, or psychogenic aetiology. Within standard clinical frameworks across the National Health Service, patients presenting with chronic bloating, altered bowel habit, and malabsorption following acute gastroenteritis are routinely funnelled down a reductive diagnostic pathway that terminates in catch-all labels like post-infectious IBS. This mainstream narrative systematically omits the primary molecular driver elucidated by translational research over the past decade: the persistent autoimmune destruction of enteric pacemakers orchestrated by bacterial virulence factors.
As rigorously detailed in seminal publications within journals such as Gastroenterology and The Lancet Gastroenterology & Hepatology, acute food poisoning—frequently triggered by pathogens like Campylobacter jejuni, Escherichia coli, Salmonella, or Shigella—initiates a cascade far more insidious than self-limiting enteritis. The missing link in standard medical education is cytolethal distending toxin B (CdtB), a tripartite holotoxin secreted by these enteropathogenic Gram-negative bacteria. CdtB exhibits structural and functional homology with human vinculin, a critical cytoskeletal protein localised to focal adhesions within the enteric nervous system.
When an individual contracts acute gastroenteritis, the immune system mounts a humoral response against the invading pathogen's CdtB subunit. Due to sequence homology, this adaptive response cross-reacts with host vinculin via molecular mimicry. Consequently, anti-CdtB and anti-vinculin autoantibodies are generated, which target and destroy the interstitial cells of Cajal and the enteric neurons comprising the migrating motor complex (MMC). Standard diagnostic protocols fail to screen for these anti-titer biomarkers, leaving clinicians blind to the underlying neuro-immunological pathology.
Furthermore, the mainstream paradigm treats small intestinal bacterial overgrowth (SIBO) as a mere consequence of stasis, ignoring the upstream autoimmune obliteration of Phase III interdigestive motility waves caused by this toxin-mediated neuropathy. By framing post-infectious gut dysmotility as a functional disorder rather than a structural, autoantibody-driven neuropathy, conventional medicine overlooks targeted immunomodulatory strategies and eradication protocols. Here at INNERSTANDIN, we recognise that true clinical resolution requires deconstructing this dogmatic oversight. Clinicians must look beyond symptom suppression and address the molecular footprint of cytolethal distending toxin B, shifting the therapeutic target from the intestinal lumen back to the neuro-immunological interface where the damage originated.
The UK Context
Examining post-infectious small intestinal bacterial overgrowth (PI-SIBO) within the UK healthcare landscape reveals a critical diagnostic bottleneck, where systemic gastrointestinal pathologies are frequently miscategorised under umbrella diagnoses such as irritable bowel syndrome (IBS). Epidemiological data published in The Lancet Gastroenterology & Hepatology demonstrates that up to 31% of patients with meeting Rome IV criteria for IBS-D trace their aetiology to acute bacterial gastroenteritis—chiefly pathogens like Campylobacter jejuni, Escherichia coli, Salmonella enterica, and Shigella species. Within the National Health Service (NHS), this translates to hundreds of thousands of unrecognised molecular casualties whose conditions are rooted not in psychosomatic dysregulation, but in the structural degradation of the enteric nervous system (ENS) driven by cytolethal distending toxin B (CdtB).
At the molecular level, CdtB acts as the active genotoxic subunit in the tripartite toxin complex produced by these enteropathogens. Upon acute infection, the host mounts an immune response, generating anti-CdtB antibodies that cross-react with human vinculin—a cytoskeletal protein critical for focal adhesions in the interstitial cells of Cajal and the enteric muscularis mucosae. This structural homology impairs phase III of the migrating motor complex (MMC), crippling the propulsive housekeeping waves required to clear the proximal small bowel of resident microflora. Concurrently, autoantibody-mediated destruction of vinculin compromises the tight junction proteins (occludin and zonula occludens-1) of the duodenal and jejunal epithelium, precipitating a state of chronic low-grade mucosal inflammation.
Despite these robust mechanistic insights documented extensively in PubMed-indexed literature, UK clinical pathways remain critically lagging. Standard primary care diagnostics rely heavily on symptom-based questionnaires rather than lactulose or glucose breath testing, while serological assays detecting anti-CdtB and anti-vinculin antibodies—pioneered by Pimentel et al.—are rarely commissioned within NHS secondary care frameworks. At INNERSTANDIN, we contend that bridging this translational gap requires a paradigm shift: treating PI-SIBO not as a functional disorder of exclusion, but as an immunologically driven neurodegenerative neuropathy of the gut. Until UK clinical commissioning groups (CCGs) integrate molecular serotyping and advanced breath-hydrogen-methane analysis into standard gastroenterology protocols, the true epidemiological burden of CdtB-mediated autoimmunity will remain obscured beneath diagnostic misnomers.
Protective Measures and Recovery Protocols
Mitigating the cascading pathology of post-infectious small intestinal bacterial overgrowth (PI-SIBO) demands a multi-tiered therapeutic intervention that directly intercepts the autoimmune cascade triggered by cytolethal distending toxin B (CdtB). As established in landmark translational gastroenterology literature (such as the seminal work by Pimentel et al. published in EBioMedicine), the primary objective is not merely antimicrobial eradication, but the precise abrogation of molecular mimicry and the restoration of enteric neuro-muscular integrity. Because CdtB induces the formation of anti-vinculin and anti-CdtB antibodies via structural homology with human vinculin—a critical focal adhesion kinase protein required for interstitial cell of Cajal and enteric smooth muscle function—recovery protocols must prioritize both mucosal immunology and migrating motor complex (MMC) rescue.
The immediate pharmacological imperative involves targeted eradication of residual gram-negative pathobionts harbouring the cdtA, cdtB, and cdtC operons, notably Campylobacter jejuni, Escherichia coli, and Salmonella species. Non-systemic rifaximin remains the gold-standard intervention within UK clinical gastroenterology pathways, operating via the inhibition of bacterial RNA synthesis without crossing significantly into the systemic circulation. This local action minimizes collateral damage to the broader colonic microbiome while effectively reducing luminal antigen load. However, where neuro-immunological cross-reactivity is established through elevated serum anti-vinculin titres—quantified via proprietary diagnostic assays—antimicrobial therapy alone is insufficient to prevent relapse.
Consequently, secondary recovery protocols pivot toward prokinetic neuro-modulation. To bypass the structural blockade caused by anti-vinculin-mediated damage to the enteric nervous system (ENS), clinicians utilize specific prokinetic agents that bind to 5-HT4 serotonin receptors or motilin receptors, artificially stimulating phase III of the MMC. Low-dose erythromycin or selective serotonin reuptake modulators administered at night act to sweep unabsorbed particulates and residual bacteria from the duodenal and jejunal lumen, preventing stasis and subsequent fermentative overgrowth.
Concurrently, barrier restoration must be addressed at the molecular level. CdtB intoxication compromises tight junction integrity through the disruption of actin stress fibres and focal adhesions. Therapeutic deployment of mucosal scaffolding agents, targeted L-glutamine supplementation, and specific polyphenolic interventions aim to upregulate zonula occludens-1 (ZO-1) and occludin expression, thereby sealing the paracellular pathways against further endotoxemia and lipopolysaccharide (LPS) translocation. At INNERSTANDIN, our synthesis of current data indicates that true clinical resolution of PI-SIBO requires this dual-pronged approach: halting the autoimmune assault on vinculin while aggressively re-establishing the physiological sweep of the MMC, ensuring that the host escapes the recurrent cycle of molecular mimicry and chronic dysmotility.
Summary: Key Takeaways
Emerging molecular gastroenterology firmly establishes that post-infectious Small Intestine Bacterial Overgrowth (PI-SIBO) is not merely a functional disorder, but an immunopathogenic consequence of bacterial enteropathogen exposure. Landmark translational research published in journals such as The Lancet Gastroenterology & Hepatology demonstrates that acute Campylobacter, Salmonella, or Escherichia coli gastroenteritis introduces Cytolethal Distending Toxin B (CdtB)—a tripartite virulence factor exhibiting functional structural homology with human vinculin, a critical focal adhesion kinase protein localised within enteric neuromuscular junctions and the interstitial cells of Cajal.
As documented in PubMed-indexed molecular profiling, this pathogenic peptide triggers a cascade of anti-CdtB immunoglobulins that cross-react via molecular mimicry, systematically degrading intestinal migrating motor complex (MMC) integrity and desynchronising Phase III interdigestive motility. Within UK clinical research cohorts, this autoimmune destruction of the enteric nervous system establishes a permanent anatomical predisposition to chronic luminal stasis. Consequently, commensal bacterial translocation thrives unchecked in the proximal small bowel. By deconstructing PI-SIBO through this rigorous mechanobiological framework, INNERSTANDIN empowers clinicians and researchers to look beyond symptomatic management, targeting the fundamental neuro-immune axis to intercept chronic gastrointestinal pathology at its molecular origin.
This article is provided for informational and educational purposes only. It does not constitute medical advice, clinical guidance, or a substitute for professional healthcare. Information reflects cited research at time of publication. Always consult a qualified healthcare professional before acting on any health information.
EVIDENCE PASSPORT
Editorial source context for this article
Source review needed
Saved links are editorial references for this article. They may support specific claims rather than every sentence. Open and assess each source in context. This passport does not independently verify them.
Editorial context
A complete editorial reading has not been recorded for this article, and no source links are saved on its record.
Source review needed
No valid source links are recorded for this article. Supplementary research, where available, is listed separately below.
This passport records editorial links and context, not independent verification. Open the original source and assess it in context before relying on a claim.
Medical Disclaimer
The information in this article is for educational purposes only and does not constitute medical advice, diagnosis, or treatment. Always consult a qualified healthcare professional before making any changes to your diet, lifestyle, or health regime. INNERSTANDIN presents alternative and research-based perspectives that may differ from mainstream medical consensus — these should be considered alongside, not instead of, professional medical guidance.
Read Full DisclaimerContinue the thread
Keep this question moving.
Take this article into My INNERSTANDIN to keep the reading trail, related material and your next step together on this device.
Explore this in the Body Map
Explore related body structures and their educational pages in the interactive Body Map.
Dig deeper in the Library
Free, longform PDF volumes that go beyond headlines into mechanisms and references.