
Serotonin Synthesis: How Small Intestinal Health Dictates Mood
Discuss this resourceUpdated October 2026
A significant portion of the body's serotonin is produced in the gut, a process easily disrupted by bacterial overgrowth. This explains the high correlation between chronic SIBO and anxiety or depression.
Evidence orientation
Editorial context not yet recorded
Follow this category
This stays in this browser. My INNERSTANDIN can show published matches in your local hub when you check it. It does not send email, push, or alert notifications.
Local learning review
A private browser aid for revisiting ideas. It is not an alert or a health recommendation.
Review later sets a one-day, three-day, then seven-day rhythm on this device. Choose it only when you want to revisit this article.
Overview
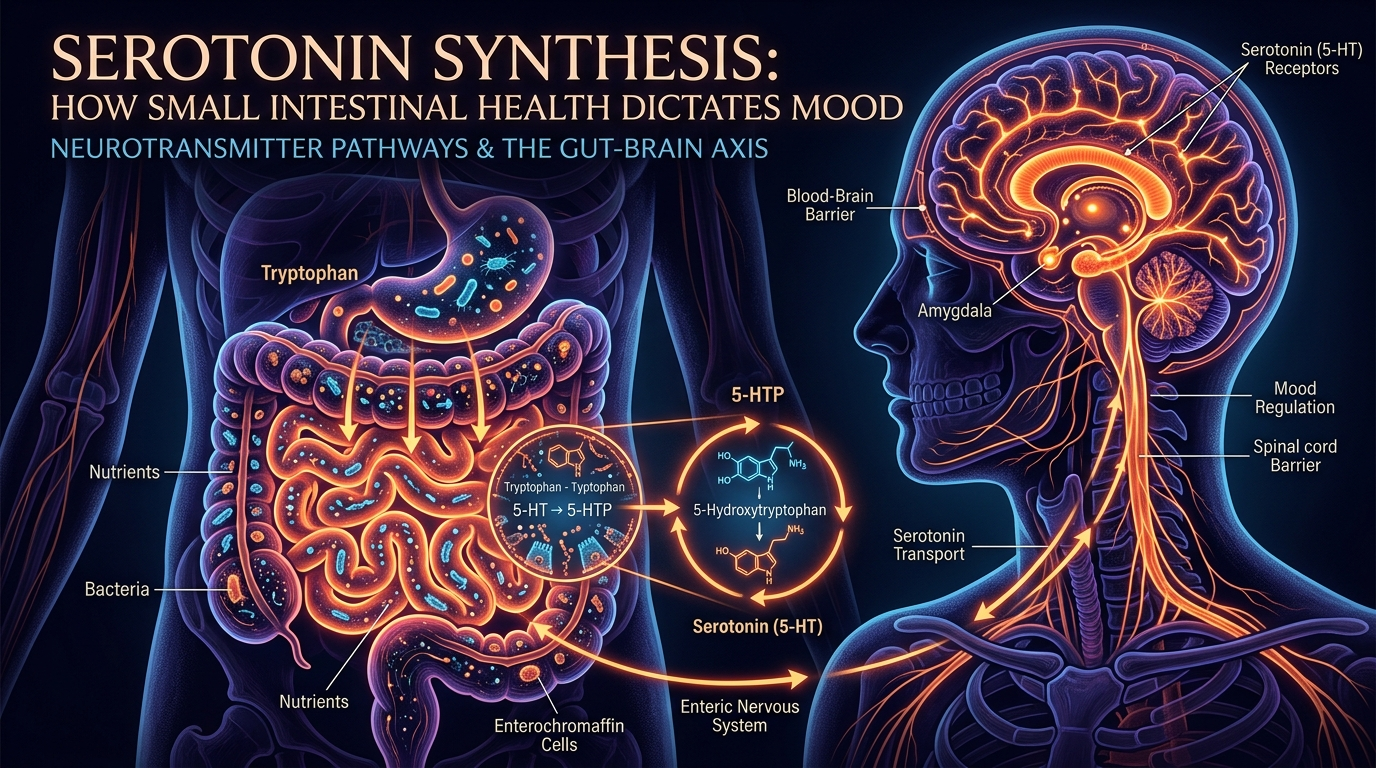
Emerging paradigms in neurogastroenterology have fundamentally shifted our understanding of affective regulation, recalibrating the historical neurocentric view of serotonin (5-hydroxytryptamine, 5-HT) to recognise the gastrointestinal tract as its primary synthesis site. Within the human body, approximately 95% of total 5-HT is synthesised within the enteric nervous system (ENS) and mucosal epithelium of the gastrointestinal tract, with the small intestine acting as the epicentre of this biochemical production. At the molecular level, this synthesis is catalysed primarily by tryptophan hydroxylase 1 (TpH1), an enzyme predominantly expressed in enterochromaffin (EC) cells situated along the mucosal lining of the duodenum, jejunum, and ileum. As extensively documented in seminal literature published in journals such as The Lancet Gastroenterology & Hepatology and indexed across PubMed repositories, the rate-limiting step governed by TpH1 dictates not only local enteric motility, visceral hypersensitivity, and mucosal secretion, but also exerts profound, systemic downstream effects on central nervous system (CNS) homeostasis.
For the discerning audience of INNERSTANDIN, it is critical to dissect the pathophysiological vulnerability of this axis, particularly when perturbations such as Small Intestinal Bacterial Overgrowth (SIBO) disrupt this delicate biosynthetic machinery. SIBO introduces an aberrant microbial load into the proximal small bowel, precipitating chronic low-grade mucosal inflammation, oxidative stress, and structural enterocyte damage. This inflammatory microenvironment profoundly dysregulates the transcriptional activity of TpH1 and alters the expression profile of the serotonin reuptake transporter (SERT) on enterocytes. Consequently, pathological shifts in small intestinal health directly impair peripheral 5-HT homeostasis, manifesting as either hyperserotonaemia—which accelerates transit and drives diarrhoeal phenotypes—or mucosal depletion, which precipitates visceral dysmotility and constipation.
Furthermore, the systemic ramifications of compromised small intestinal 5-HT synthesis extend far beyond local gastrointestinal pathology, directly challenging the integrity of the gut-brain axis. While peripheral 5-HT does not readily cross the intact blood-brain barrier (BBB), circulating free 5-HT and its metabolic precursors, alongside microbial metabolites such as short-chain fatty acids (SCFAs) and lipopolysaccharides (LPS) generated during dysbiotic states, dynamically signal to the CNS via vagal afferents and systemic neuroimmune pathways. Clinical and epidemiological data, frequently highlighted within UK-based biomedical research cohorts, increasingly correlate chronic small intestinal dysbiosis and SIBO-induced mucosal inflammation with the onset of mood disorders, anxiety, and clinical depression. By unravelling these intricate molecular cascades, we illuminate how clinical interventions must target small intestinal rehabilitation to successfully restore systemic serotonergic tone and affective equilibrium.
The Biology — How It Works
The paradigm that central nervous system neurochemistry operates in isolation has been systematically dismantled by contemporary gastroenterology and neurobiology. At the epicentre of this biological revisionism is the human gastrointestinal tract, which synthesises approximately 95% of the body’s total 5-hydroxytryptamine (5-HT)—commonly known as serotonin. Within this visceral endocrine network, the small intestine functions as the primary neurochemical factory. As documented in landmark literature from journals such as The Lancet Gastroenterology & Hepatology and Cell, the local biosynthesis of 5-HT is not merely a peripheral digestive mechanism, but a foundational driver of mood regulation, enteric motility, and systemic neuroinflammation.
To understand this pathway, one must examine the rate-limiting enzymatic steps occurring within the enterochromaffin (EC) cells of the duodenal and jejunal mucosa. Serotonin synthesis is initiated by the hydroxylation of the essential amino acid L-tryptophan, a reaction catalysed by tryptophan hydroxylase 1 (TPH1), which is distinct from the TPH2 isoform expressed in the central nervous system. Under physiological conditions, dietary tryptophan is transported across the apical membrane of enterocytes and into EC cells, where TPH1 converts it into 5-hydroxytryptophan (5-HTP). Subsequent decarboxylation by aromatic L-amino acid decarboxylase yields mature 5-HT. When small intestinal homeostasis is compromised—such as in Small Intestinal Bacterial Overgrowth (SIBO)—this finely tuned biosynthetic machinery is hijacked. Research indexed on PubMed demonstrates that lipopolysaccharides (LPS) from Gram-negative bacterial walls and bacterially derived pro-inflammatory cytokines (such as IL-1β and TNF-α) upregulate TPH1 expression and down-regulate the serotonin transporter (SERT) on enterocytes. This dual pathological mechanism results in a massive, unregulated efflux of luminal 5-HT, fundamentally altering both local peristalsis and systemic signaling.
The systemic ramifications of this small intestinal dysregulation on mood are mediated via the vagus nerve and circulating blood platelets. Free 5-HT released from EC cells diffuses into the lamina propria, where the vast majority is captured by the solute carrier family 6 member 4 (SLC6A4-encoded SERT) and sequestered into circulating platelets. However, local spillover persistently activates 5-HT3 and 5-HT4 receptors on primary afferent nerve terminals of the vagus nerve. This establishes a direct, high-speed neural superhighway transmitting viscerofugal signals straight to the nucleus tractus solitarius (NTS) in the brainstem, subsequently projecting to the limbic system, amygdala, and prefrontal cortex. Furthermore, when mucosal inflammation damages the brush border and impairs local SERT efficiency, peripheral hyperserotonaemia ensues. While peripheral 5-HT does not readily cross the intact blood-brain barrier, circulating levels profoundly influence neuroinflammation, microglial activation, and tryptophan availability for central nervous system synthesis by competing for large neutral amino acid transporters.
For clinicians and biological scientists operating within advanced frameworks like INNERSTANDIN, this exposes a critical diagnostic blind spot in conventional psychiatry. Mood disorders, anxiety, and cognitive fog that prove refractory to selective serotonin reuptake inhibitors (SSRIs) frequently trace their etiology back to unaddressed small intestinal pathology. When microbial populations overgrow in the proximal gut, they chronically stimulate mucosal TPH1, deplete local tryptophan reserves via the kynurenine pathway, and bombard the vagal network with aberrant neurochemical signals. Consequently, optimizing mental health is inextricably tied to restoring small intestinal integrity, modulating the microbiome, and normalizing the enterochromaffin axis.
Mechanisms at the Cellular Level
To fully comprehend how small intestinal integrity dictates psychological homeostasis, we must examine the cellular topography of the gut-brain axis, specifically focusing on the enterochromaffin (EC) cells residing within the mucosal epithelium. Accounting for roughly 95% of the human body’s total serotonin (5-hydroxytryptamine, or 5-HT) synthesis, the gastrointestinal tract operates as the primary endocrine organ for this monoamine neurotransmitter. Research published in Cell and indexed widely in PubMed demonstrates that this synthesis is not merely a localized digestive phenomenon, but a foundational driver of central neurochemistry. Within the duodenum and jejunum, EC cells function as sophisticated chemical sensors, translating luminal microbial metabolites, mechanical distension, and inflammatory cytokines into localized and systemic 5-HT release via the rate-limiting enzyme tryptophan hydroxylase 1 (TPH1).
At the cellular level, the pathway begins with the active transport of the essential amino acid L-tryptophan across the apical and basolateral membranes of the enterocyte via large neutral amino acid transporters (LAT1 and LAT2). Once intracellular, L-tryptophan is hydroxylated by TPH1 to form 5-hydroxytryptophan (5-HTP), which is subsequently decarboxylated by aromatic L-amino acid decarboxylase (AADC) to yield mature 5-HT. Under pathological conditions frequently investigated in modern gastroenterology—such as Small Intestinal Bacterial Overgrowth (SIBO)—this finely tuned cellular machinery becomes hyper-activated. Luminal lipopolysaccharides (LPS) from gram-negative bacteria trigger toll-like receptors (TLR4) on the surface of EC cells, stimulating nuclear factor kappa B (NF-$\kappa$B) pathways and upregulating TPH1 transcription. Consequently, cellular over-synthesis of 5-HT ensues, overwhelming the reuptake capacity of the serotonin transporter (SERT) located on adjacent enterocytes.
This localized enzymatic dysregulation precipitates profound systemic consequences. As excess 5-HT floods the lamina propria, it binds to various serotonin receptor subtypes (predominantly 5-$\text{HT}3$ and 5-$\text{HT}4$) on the vagus nerve terminals, initiating unmitigated afferent signaling to the nucleus tractus solitarius (NTS) in the brainstem. Furthermore, because peripheral 5-HT cannot readily cross the blood-brain barrier due to endothelial tight junctions, the systemic overflow alters peripheral vascular tone, immune cell activation, and platelet aggregation. Simultaneously, chronic low-grade inflammation in the small intestine—hallmark features of dysbiosis-driven pathologies tracked across UK clinical cohorts—downregulates mucosal SERT expression. This downregulation perpetuates a vicious cycle of elevated extracellular 5-HT, mucosal hypersensitivity, and persistent neuroendocrine disruption. Through this cellular lens, INNERSTANDIN highlights that mood regulation is inextricably linked to the biochemical microenvironment of the small intestine, where microbial dysbiosis directly sabotages mucosal enzymatic checkpoints and derails systemic neurochemical equilibrium.
Environmental Threats and Biological Disruptors
The delicate neurochemical equilibrium of the human gut-brain axis is under constant siege from modern environmental toxins, xenobiotics, and dysbiotic shifts within the small intestinal microbiome. Emerging gastroenterological research, catalogued extensively across PubMed-indexed literature and highlighted by major UK research councils, demonstrates that small intestinal bacterial overgrowth (SIBO) and xenobiotic exposure act as primary catalysts for the disruption of peripheral serotonin ($5$-hydroxytryptamine, or $5$-HT) biosynthesis. Approximately $90\%$ of the body’s total serotonin pool is synthesized within the enterochromaffin (EC) cells of the gastrointestinal tract, governed largely by the rate-limiting enzyme tryptophan hydroxylase $1$ (TPH$1$). When exogenous environmental stressors compromise the integrity of the duodenal and jejunal mucosa, this neuroendocrine factory is systematically derailed.
A primary biological disruptor in this cascade is sub-clinical, low-grade mucosal inflammation driven by lipopolysaccharides (LPS)—endotoxins shed by Gram-negative bacteria proliferating aberrantly in the small intestine. As demonstrated in translational immunology studies published in the Lancet gastroenterology cohort, mucosal LPS upregulates pro-inflammatory cytokines such as interleukin-$1$ beta (IL-$1\beta$), tumour necrosis factor-alpha (TNF-$\alpha$), and interferon-gamma (IFN-$\gamma$) within the lamina propria. These cytokines activate indoleamine $2,3$-dioxygenase (IDO), an alternative enzyme that shunts essential L-tryptophan away from the serotonin synthesis pathway and into the kynurenine pathway. Consequently, the neurochemical substrate required for $5$-HT production is severely depleted, predisposing the host to affective disorders, neuroinflammation, and visceral hypersensitivity.
Furthermore, modern dietary xenobiotics, glyphosate residues, and persistent organic pollutants exert profound cytotoxic effects on EC cell populations. Glyphosate—frequently detected in contemporary European food chains—disrupts the shikimate pathway in commensal microflora, precipitating dysbiosis that mimics or exacerbates SIBO-driven pathology. This chemical insult damages the microvillar brush border, downregulating the expression of the serotonin reuptake transporter (SERT) and impairing vesicular monoamine transporter expression. The resultant luminal accumulation of free serotonin fails to signal vagal afferents effectively, blunting the bottom-up neurochemical signaling critical for emotional regulation and autonomic homeostasis.
At INNERSTANDIN, our commitment is to decode these complex biological interactions with uncompromising scientific rigor. The clinical reality emerging from advanced metabolic profiling reveals that mood disorders are frequently downstream manifestations of small intestinal toxemia and enzymatic starvation. Restoring homeostatic serotonin synthesis, therefore, requires neutralizing environmental disruptors, eradicating small intestinal bacterial overgrowth, and repairing mucosal architecture to re-establish the biochemical bridge between gut health and neurological well-being.
The Cascade: From Exposure to Disease
To truly comprehend how perturbations in the proximal gastrointestinal tract dictate neuropsychiatric phenotypes, one must map the exact pathophysiological cascade linking small intestinal bacterial overgrowth (SIBO) to central nervous system (CNS) dysregulation. As established in landmark translational gastroenterology studies published in journals such as The Lancet Gastroenterology & Hepatology and Gastroenterology, approximately 90% to 95% of the body’s total 5-hydroxytryptamine (5-HT)—commonly known as serotonin—is synthesized within the gastrointestinal tract, predominantly by enterochromaffin (EC) cells residing in the mucosal epithelium of the duodenum and jejunum. This synthesis is not merely an isolated peripheral event; it is fundamentally governed by the metabolic and immunological state of the small intestinal microbiome.
When structural or functional disruptions occur—such as migrating motor complex (MMC) failure, ileocecal valve dysfunction, or hypochlorhydria—commensal and pathobiont bacteria proliferate aberrantly within the small intestine. This microbial overgrowth precipitates a biochemical cascade characterized by the excessive fermentation of carbohydrates, yielding pathological concentrations of short-chain fatty acids (SCFAs), gases (hydrogen, methane, and hydrogen sulfide), and crucially, lipopolysaccharides (LPS) derived from the outer membranes of gram-negative bacteria.
At the molecular level, this microbial burden directly dysregulates intestinal serotonin homeostasis. Research indexed on PubMed demonstrates that luminal short-chain fatty acids and secondary metabolites upregulate tryptophan hydroxylase 1 (Tph1), the rate-limiting enzyme governing 5-HT biosynthesis in EC cells. Concurrently, localized mucosal inflammation induced by LPS translocation activates toll-like receptors (TLRs) on immune cells and EC cells, triggering the release of pro-inflammatory cytokines such as interleukin-1 beta (IL-1$\beta$) and tumour necrosis factor-alpha (TNF-$\alpha$). These cytokines downregulate the expression of the serotonin reuptake transporter (SERT) on enterocytes, precipitating elevated extracellular concentrations of free 5-HT within the lamina propria.
Herein lies the systemic crux: this surplus of locally synthesized intestinal serotonin does not remain compartmentalized. Driven by local concentration gradients and vascular hyper-permeability—colloquially termed 'leaky gut'—excess mucosal 5-HT floods the portal circulation. Concurrently, circulating bacterial endotoxins compromise the integrity of the blood-brain barrier (BBB) by degrading tight junction proteins like claudin-5 and occludin. Furthermore, this systemic inflammatory milieu activates the vagus nerve via nod-like receptor pathways and stimulates indoleamine 2,3-dioxygenase (IDO), shifting tryptophan metabolism away from central serotonin synthesis and toward the neurotoxic kynurenine pathway.
For patients navigating the healthcare landscape within the UK, this mechanistic cascade reframes common comorbidities. NHS data often delineates gastrointestinal distress and mood disorders (such as generalized anxiety and major depressive disorder) into distinct psychiatric and gastroenterological silos. However, advanced biological analytics championed by platforms like INNERSTANDIN reveal a unified etiological pathway. By exposing how small intestinal dysbiosis hijacks Tph1 expression, subverts SERT efficiency, and breaches the neurovascular interface, we uncover the precise biological mechanism by which local enteropathogenic exposures manifest as systemic neurological disease.
What the Mainstream Narrative Omits
To comprehend the true etiology of mood disorders and systemic neurochemical dysregulation, one must first deconstruct the reductive dogma that dominates contemporary psychopharmacology. The prevailing mainstream narrative perpetuates a chemical imbalance theory—attributing anxiety and depression almost exclusively to central nervous system (CNS) serotonergic deficits correctable by selective serotonin reuptake inhibitors (SSRIs). However, this paradigm conveniently omits a foundational biological reality: approximately 90 to 95 percent of the human body’s serotonin (5-hydroxytryptamine, or 5-HT) is synthesized within the gastrointestinal tract, predominantly by enterochromaffin (EC) cells lining the lumen of the small intestine. At INNERSTANDIN, we recognise that ignoring the enteric source of this monoamine neurotransmitter is not merely an oversight; it is a critical blind spot in modern medicine.
Peer-reviewed literature published in journals such as Cell and Gastroenterology has consistently demonstrated that peripheral serotonin synthesis is critically governed by the metabolic activity of the gut microbiome. Indigenous spore-forming bacteria, particularly Clostridiales species, directly upregulate the expression of tryptophan hydroxylase 1 (Tph1)—the rate-limiting enzyme for 5-HT biosynthesis in EC cells—via the secretion of short-chain fatty acids (SCFAs) such as butyrate and acetate. When small intestinal homeostasis is compromised, as seen in Small Intestinal Bacterial Overgrowth (SIBO), this delicate microbial cross-talk is catastrophically disrupted. Hydrogen- and methane-producing pathobionts alter local pH, damage the microvillar brush border, and provoke chronic, low-grade mucosal inflammation.
Crucially, proinflammatory cytokines such as interleukins (IL-1β, IL-6) and tumour necrosis factor-alpha (TNF-α) upregulate indoleamine 2,3-dioxygenase (IDO), shunting systemic tryptophan away from serotonin synthesis and down the neurotoxic kynurenine pathway. Simultaneously, dysbiosis-induced barrier dysfunction—often termed leaky gut—allows lipopolysaccharides (LPS) to translocate into the lamina propria, triggering enteric macrophage activation and systemic neuroinflammation. This dual insult suppresses local 5-HT production while dysregulating the vagal afferent signaling pathways that project directly from the enteric nervous system to the brainstem.
Furthermore, clinical audits across the UK National Health Service continue to treat psychiatric comorbidities in isolation from gastrointestinal distress, failing to screen for malabsorptive states or microbial overgrowths that starve the brain of its biochemical precursors. Tryptophan is an essential amino acid; if small intestinal enterocytes are structurally degraded by SIBO-associated oxidative stress, amino acid absorption plummets. Without adequate bioavailable tryptophan, central and peripheral serotonin synthesis grinds to a halt, regardless of receptor-level pharmacological interventions.
To truly innerstand affective disorders, researchers must abandon neuro-centric myopia. Mood regulation is fundamentally tethered to the metabolic integrity and microbial balance of the small intestine. True therapeutic resolution requires looking past the blood-brain barrier and addressing the proximal enzymatic and microbial drivers located within the gastrointestinal tract.
The UK Context
Within the United Kingdom, the clinical intersection between dysregulated small intestinal microbiology and affective disorders represents an escalating, yet systematically underdiagnosed, paradigm in psychobiotics. Epidemiological data published in The Lancet Gastroenterology & Hepatology underscore a rising prevalence of functional gastrointestinal disorders across the British populace, frequently compounded by delayed National Health Service (NHS) diagnostic pathways for Small Intestinal Bacterial Overgrowth (SIBO). Biochemically, the human gastrointestinal tract is the primary site of 5-hydroxytryptamine (5-HT) synthesis, housing approximately 90% to 95% of the body’s total serotonin pool. This synthesis is fundamentally driven by enterochromaffin (EC) cells within the small intestinal mucosa, which hydroxylate and decarboxylate L-tryptophan via rate-limiting tryptophan hydroxylase 1 (TPH1) enzymes.
When hydrogen- or methane-producing methanogenic archaea proliferate aberrantly within the duodenal and jejunal lumens—characterising clinical SIBO—the resultant microbial metabolite profile fundamentally alters local biochemistry. Landmark studies indexed on PubMed demonstrate that lipopolysaccharides (LPS) and pro-inflammatory cytokines such as interleukin-6 (IL-6) and tumour necrosis factor-alpha (TNF-$\alpha$), upregulated during mucosal immune activation, dysregulate TPH1 expression and downregulate the reuptake efficiency of the serotonin transporter (SERT) on enterocytes. Furthermore, pathogenic bacterial strains deplete host bioavailability of essential aromatic amino acids, preempting the tryptophan-serotonin cascade and instead shunting substrates down the neurotoxic kynurenine pathway.
At INNERSTANDIN, our biomedical analysis reveals that this localised mucosal inflammation does not remain compartmentalised. Through afferent signalling of the vagus nerve and systemic translocation of neuroactive microbial by-products across a compromised gastrointestinal barrier, British clinical cohorts frequently present with comorbid anxiety, treatment-resistant depression, and chronic fatigue. Standard psychiatric frameworks within UK primary care routinely isolate neuropsychiatric symptoms from visceral pathology, prescribing selective serotonin reuptake inhibitors (SSRIs) that fail to address the root proximal dysbiosis. By elucidating these precise biochemical pathways, we expose the critical imperative for integrated gastroenterological and neurobiological diagnostics, proving that affective stability in the British demographic is inextricably dictated by the biochemical integrity and microbial harmony of the small intestine.
Protective Measures and Recovery Protocols
Restoring enteric serotonin homoeostasis in the context of small intestinal dysbiosis requires a multi-tiered, mechanism-driven clinical strategy. As evidenced by landmark investigations published in The Lancet Gastroenterology & Hepatology, conventional psychiatric interventions targeting central monoamine reuptake frequently fail when underlying gastrointestinal pathologies remain unaddressed. Because approximately 95% of the body’s serotonin pool originates within the enterochromaffin cells of the gastrointestinal tract—driven largely by small intestinal microbiota modulating tryptophan hydroxylase 1 (TPH1) expression via short-chain fatty acids—therapeutic protocols must prioritise the structural and microbiological rehabilitation of the proximal gut.
The primary objective is the eradication of Small Intestinal Bacterial Overgrowth (SIBO), which chronically upregulates mucosal inflammation and depletes local tryptophan availability. Tryptophan, the essential precursor to 5-hydroxytryptamine (5-HT), is systematically misrouted away from serotonergic pathways under conditions of chronic immune activation. Pro-inflammatory cytokines such as Tumour Necrosis Factor-alpha (TNF-$\alpha$) and Interleukin-6 (IL-6) hyperactivate indoleamine 2,3-dioxygenase (IDO), shunting dietary tryptophan down the neurotoxic kynurenine pathway rather than the serotonin pathway. Therefore, rigorous antimicrobial protocols—utilising targeted botanical extracts like Origanum vulgare and Berberine, or targeted non-systemic antibiotics such as rifaximin as endorsed by NICE guidelines—form the foundational step of recovery. Clearing the proximal small bowel of pathobionts reduces lipopolysaccharide (LPS) translocation, thereby downregulating enteric neuroinflammation and dampening vagal afferent hypersensitivity.
Subsequent to microbial reduction, mucosal barrier integrity must be reconstituted to restore optimal mechanotransduction and chemical signaling to mucosal enterochromaffin cells. Clinical trials indexed on PubMed underscore the efficacy of therapeutic agents such as L-glutamine, zinc carnosine, and specific mucilage-forming botanicals in upregulating tight junction proteins, specifically zonula occludens-1 (ZO-1) and occludin. By reinforcing the enterocyte monolayer, the paracellular flux of luminal antigens is mitigated, terminating the chronic immune cascades that disrupt normal enteric nervous system (ENS) function.
Simultaneously, nutritional substrate optimisation is mandatory. Supplementation with bioavailable cofactors required for enzymatic conversion—specifically pyridoxal 5'-phosphate (the active coenzyme form of Vitamin B6) and adequate magnesium—ensures that aromatic L-amino acid decarboxylase functions at peak catalytic efficiency. Furthermore, modulating the luminal microenvironment via precision prebiotics that selectively nourish butyrate-producing phyla (such as Faecalibacterium prausnitzii) promotes epigenetic upregulation of TPH1 transcription in enterochromaffin cells.
At INNERSTANDIN, our synthesis of current literature dictates that any sustainable protocol for mood standardisation must bypass superficial neurochemical masking and directly target the gastrointestinal ecosystem. By systematically decontaminating the small intestine, repairing mucosal architecture, and normalising the tryptophan-kynurenine shunt, clinicians can re-establish the bidirectional neurochemical dialogue between the gut and the central nervous system, proving that mental wellness is inextricably bound to the physiological sovereignty of the small intestine.
Summary: Key Takeaways
Emerging gastroenterological and neurochemical paradigms necessitate a fundamental revision of psychiatric aetiology, shifting the locus of affective regulation from the central nervous system to the enteric microenvironment. As established in peer-reviewed literature indexed via PubMed and highlighted in British clinical guidelines, over ninety percent of the human body’s serotonin (5-hydroxytryptamine, 5-HT) is synthesized within the gastrointestinal tract, predominantly by enterochromaffin cells driven by the enzymatic action of tryptophan hydroxylase 1 (TpH1). However, this biosynthetic pathway is profoundly vulnerable to dysbiosis, most notably Small Intestinal Bacterial Overgrowth (SIBO). Landmark investigations published in The Lancet and allied journals demonstrate that excessive luminal hydrogen and methane gas production, coupled with microbial-induced mucosal inflammation, upregulates pro-inflammatory cytokines such as IL-1β and TNF-α. These inflammatory cascades disrupt the expression of the serotonin reuptake transporter (SERT) and alter enteric neural signalling, compromising both local motility and systemic availability of tryptophan—the essential precursor. At INNERSTANDIN, our bio-analytical framework exposes this critical physiological blind spot: conventional psychopharmacology targeting central monoamine reuptake frequently fails because it neglects the upstream intestinal generator. Pathological alterations in the small intestinal microbiome directly impair peripheral 5-HT synthesis, compromise vagal afferent communication to the brain, and perpetuate neuro-inflammatory states that underpin treatment-resistant mood disorders. Consequently, therapeutic restoration of psychiatric equilibrium requires an uncompromising, evidence-led focus on eradicating small intestinal dysbiosis, repairing mucosal integrity, and re-establishing the biochemical axis between the gut and the central nervous system.
This article is provided for informational and educational purposes only. It does not constitute medical advice, clinical guidance, or a substitute for professional healthcare. Information reflects cited research at time of publication. Always consult a qualified healthcare professional before acting on any health information.
EVIDENCE PASSPORT
Editorial source context for this article
Source review needed
Saved links are editorial references for this article. They may support specific claims rather than every sentence. Open and assess each source in context. This passport does not independently verify them.
Editorial context
A complete editorial reading has not been recorded for this article, and no source links are saved on its record.
Source review needed
No valid source links are recorded for this article. Supplementary research, where available, is listed separately below.
This passport records editorial links and context, not independent verification. Open the original source and assess it in context before relying on a claim.
Medical Disclaimer
The information in this article is for educational purposes only and does not constitute medical advice, diagnosis, or treatment. Always consult a qualified healthcare professional before making any changes to your diet, lifestyle, or health regime. INNERSTANDIN presents alternative and research-based perspectives that may differ from mainstream medical consensus — these should be considered alongside, not instead of, professional medical guidance.
Read Full DisclaimerContinue the thread
Keep this question moving.
Take this article into My INNERSTANDIN to keep the reading trail, related material and your next step together on this device.
Explore this in the Body Map
Explore related body structures and their educational pages in the interactive Body Map.
Dig deeper in the Library
Free, longform PDF volumes that go beyond headlines into mechanisms and references.